Related Experiment Video
Updated: Jan 13, 2026


A Large Animal Model for Acute Kidney Injury by Temporary Bilateral Renal Artery Occlusion
Published on: February 2, 2021
A prescription-based model for predicting post-hemodialysis urea and electrolytes: a real-world validation study in
Pablo Galindo1, Cesar R Barrientos2, Rosario G Hernández2,3
1Department of Nephrology, Hospital General de México "Dr Eduardo Liceaga", Mexico City, Mexico.

Background:
Urgent-start hemodialysis often involves severe biochemical abnormalities but is associated with a high risk of complications. Currently, no tool has been validated to predict post-hemodialysis urea and electrolytes in acute settings from prescription data alone.
Methods:
In this ambispective, two-phase study, we developed and validated a model to predict post-hemodialysis blood urea nitrogen and electrolytes using only prescription parameters in patients with urgent hemodialysis indications and those at risk for dialysis disequilibrium syndrome, severe hyponatremia, or hyperkalemia. The model was validated through statistical assessment of correlation and agreement. The model was integrated into a free, user-friendly web application (Adequator app®).
Results:
The development cohort included 303 treatments in 42 chronic hemodialysis patients. Dialyzer clearance, which was calculated via formal urea kinetic modeling, demonstrated excellent correlation and agreement with the proposed model (r = 0.99; 95% CI: 0.99 to 0.99) and a bias of 0.23 ± 1.2 ml/min (95% CI: -2.17 to 2.63). The validation cohort included 44 urgent hemodialysis sessions in 30 patients with chronic kidney disease or acute kidney injury and severe electrolyte abnormalities or at risk of dialysis disequilibrium syndrome. The predicted post-hemodialysis, blood urea nitrogen, sodium, and potassium levels strongly correlated with the measured values: r = 0.96 (95% CI: 0.93 to 0.98), r = 0.96 (95% CI: 0.94 to 0.98), and r = 0.84 (95% CI: 0.73 to 0.91), respectively. Agreement was also high, with biases of 0.4 ± 9.4 mg/dL (95% CI: -19.0 to 18.1) for blood urea nitrogen, -0.6 ± 1.6 mEq/L (95% CI: -3.8 to 2.5) for sodium, and 0.17 ± 0.4 mEq/L (95% CI: 0.6 to 0.9) for potassium. Among patients at risk of dialysis disequilibrium syndrome, 92% achieved the target blood urea nitrogen reduction ( < 40%) without severe neurological events. The sodium correction remained below 6 mEq/L, and potassium normalized in all the cases.
Conclusions:
A prescription-based model can reliably predict post-Hemodialysis urea and electrolyte values in urgent dialysis settings. The Adequator App HD-Predictor ( https://adequatorapp.com/hd-predictor ) offers a non-invasive, accessible tool to guide individualized prescriptions, enhancing safety and precision in high-risk clinical scenarios.

Related Concept Videos
 01:28
Drug Dosing in Renal Diseases: Estimation of Glomerular Filtration Rate Based on Serum Creatinine Concentration
 01:20
Acute Kidney Injury V: Interprofessional Care
 01:25
Hemodialysis III: Nursing Management
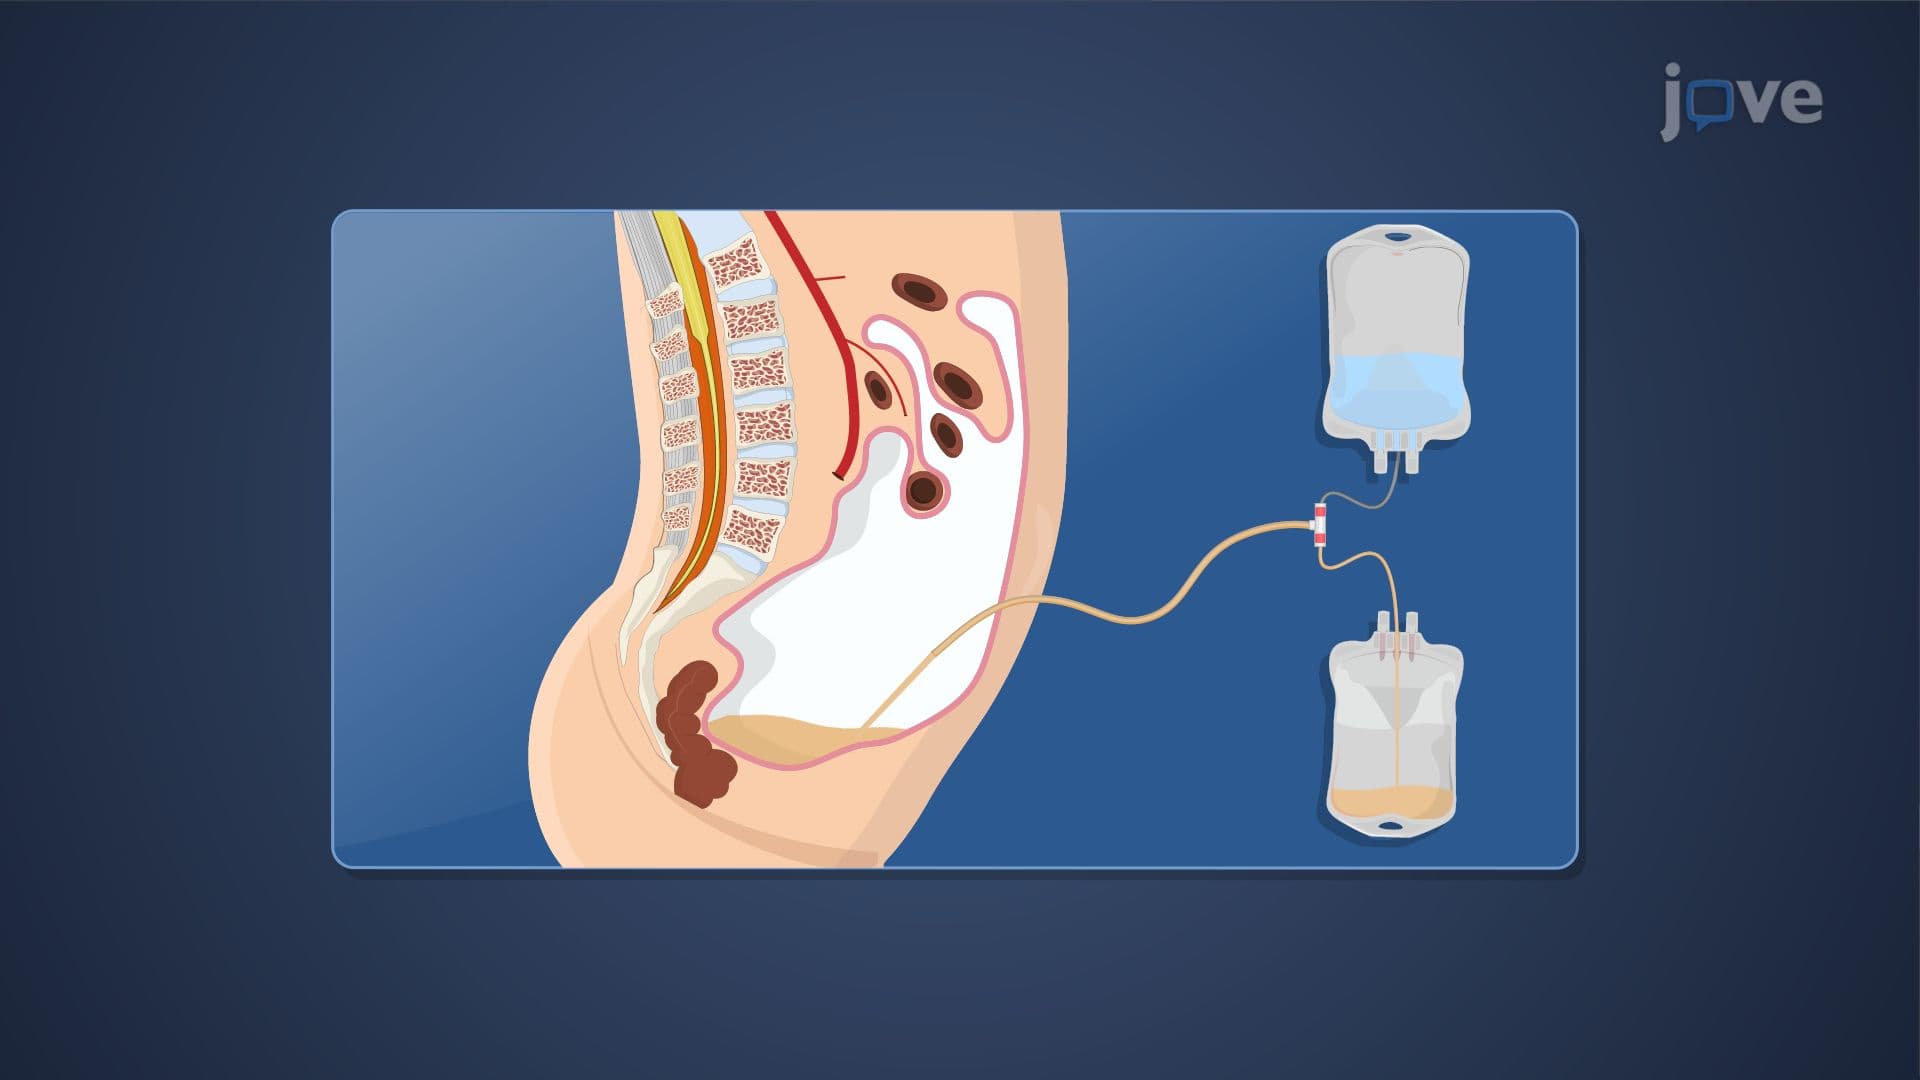 01:30
Extracorporeal Removal of Drugs: Peritoneal Dialysis and Hemodialysis
 01:25
Hemodialysis I: Introduction
 01:27
Dialysis
Acute kidney injury develops suddenly and can be caused by pre-renal causes (e.g., hypovolemia, shock), intrinsic renal causes (e.g., acute tubular necrosis), or post-renal causes (e.g., urinary obstruction). In contrast, chronic renal failure progresses gradually over time and is often...