Related Experiment Video
Updated: Jun 25, 2026
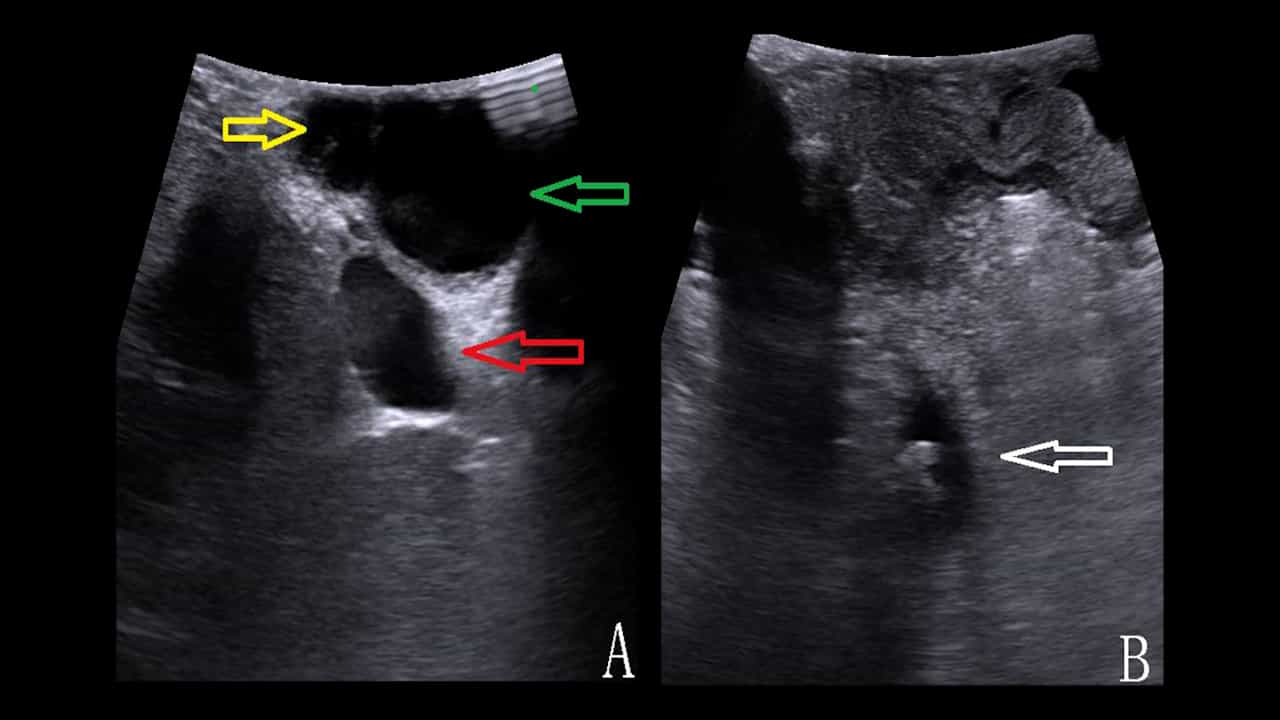
Application of Laparoscopic Ultrasonography in Primary Choledochal Suture during Combined Two-lens Surgery
Published on: March 28, 2025
Risk factors for anastomotic stenosis after congenital choledochal cyst surgery and efficacy analysis of laparoscopic
Chengyang Jiang1, Yifeng Shao1, Ruyue Gao2
1Capital Institute of Pediatrics, Chinese Academy of Medical Sciences & Peking Union Medical College, Beijing, China; Department of General Surgery, Capital Institute of Pediatrics, Beijing, China.

Insights
This study identifies risk factors for anastomotic stenosis after congenital choledochal cyst surgery and confirms laparoscopic reoperation is effective. Early identification and minimally invasive surgery improve patient outcomes.
Area of Science:
- Pediatric surgery
- Gastroenterology
- Biliary tract diseases
Background:
- Congenital choledochal cyst (CCC) is a common pediatric biliary dysplasia, particularly in Asia.
- Anastomotic stenosis is a frequent long-term complication following CCC surgery (complete cyst excision + Roux-en-Y hepaticojejunostomy).
- Previous research has not systematically analyzed factors influencing anastomotic stenosis or the efficacy of laparoscopic reoperation.
Purpose of the Study:
- To systematically analyze factors influencing anastomotic stenosis after CCC surgery.
- To evaluate the medium- and long-term efficacy of laparoscopic hepaticojejunostomy for treating this complication.
- To provide a clinical reference for managing pediatric CCC postoperative anastomotic stenosis.
Main Methods:
- Single-center retrospective cohort study of 139 patients with anastomotic stenosis (diameter <3 mm) after CCC surgery (Jan 2015-Jun 2024).
- Patients were divided into those initially operated at the center (Group A) and elsewhere (Group B).
- Laparoscopic bile duct plasty + hepaticojejunostomy was the preferred reoperation method; statistical analysis used R software.
Main Results:
- Stenosis incidence was 2.2% (139/1853 CCC excisions).
- Independent risk factors for stenosis included proximal cyst wall thickness and postoperative CRP; common hepatic duct outlet diameter was protective.
- Laparoscopic reoperation (82% of cases) expanded anastomotic diameter, improved liver function, with 66.2% achieving normal intrahepatic bile ducts at follow-up.
Conclusions:
- A novel prediction model for pediatric CCC postoperative anastomotic stenosis was developed to identify high-risk individuals.
- Laparoscopic bile duct plasty + hepaticojejunostomy demonstrates reliable medium- and long-term efficacy for anastomotic stenosis.
- Laparoscopic reoperation is recommended as the preferred surgical approach for this complication.
Background:
Congenital choledochal cyst (CCC) is a common congenital biliary dysplasia in children, with higher incidence in Asia, treated by complete cyst excision plus Roux-en-Y hepaticojejunostomy (laparoscopy as preferred). Anastomotic stenosis, a common long-term postoperative complication, increases patient burden and treatment difficulty. Previous studies lacked systematic analysis of its influencing factors, and laparoscopic reoperation for it was once contraindicated, with only small-scale studies showing its efficacy comparable to open surgery.
Objective:
To systematically analyze influencing factors of anastomotic stenosis after CCC surgery and explore medium- and long-term efficacy of laparoscopic hepaticojejunostomy for this complication, providing clinical reference.
Methods:
This single-center retrospective cohort study (approved by Ethics Committee of Capital Institute of Pediatrics, No.: SHELL20240103; informed consent waived) screened patients with anastomotic stenosis (diameter <3 mm) after CCC surgery (Jan 2015-Jun 2024), dividing them into Group A (41 cases, initial surgery in our hospital) and Group B (98 cases, initial surgery in other hospitals). Group A underwent 1:3 propensity score matching (surgical age, gender, period) to get 120 stenosis-free patients as Group C. Data on surgery, imaging, laboratory tests and pathology were collected. Laparoscopic bile duct plasty + hepaticojejunostomy was preferred for reoperation. Follow-up (1, 3, 6 months post-reoperation, then annual, 3-yearly after 5 years) and statistical analysis (R software) were conducted.
Results:
A total of 139 reoperation patients with anastomotic stenosis were admitted, with a stenosis incidence of 2.2 % (139/1853 CCC excisions). Multivariate analysis showed proximal cyst wall thickness (OR = 4.28, 95 % CI 2.15-8.53) and 3rd postoperative day CRP (OR = 1.55, 95 % CI 1.24-1.93) were independent risk factors, while common hepatic duct outlet diameter (OR = 0.17, 95 % CI 0.07-0.47) was a protective factor; the prediction model had an AUC of 0.863 with good calibration. Eighty-two percent of reoperations were laparoscopic (18 % converted to open), with anastomotic diameter expanded from a preoperative median of 0.1 cm-1.5 cm. Postoperatively, liver function improved significantly. The median postoperative follow-up duration was 831 days (372, 2501): by June 2025, 66.2 % of patients had normal intrahepatic bile ducts, 3.6 % had recurrent intrahepatic bile duct stones, and 4.3 % had mild liver function abnormalities (all improved with conservative treatment, no reoperation needed).
Conclusion:
A prediction model for pediatric CCC postoperative anastomotic stenosis was first constructed to identify high-risk patients. Laparoscopic bile duct plasty + hepaticojejunostomy has reliable medium- and long-term efficacy for this stenosis, serving as preferred surgery. The study has limitations like single-center design and missing initial surgery data of transferred patients.

Related Concept Videos
 01:28
Cardiomyopathy VII: Pre and Post Operative Nursing Management
 01:23
Peripheral Artery Disease V: Postoperative Nursing Management
 01:26
Varicose Veins II: Diagnostic Studies and Interprofessional Care