Related Experiment Video
Updated: Jul 24, 2026
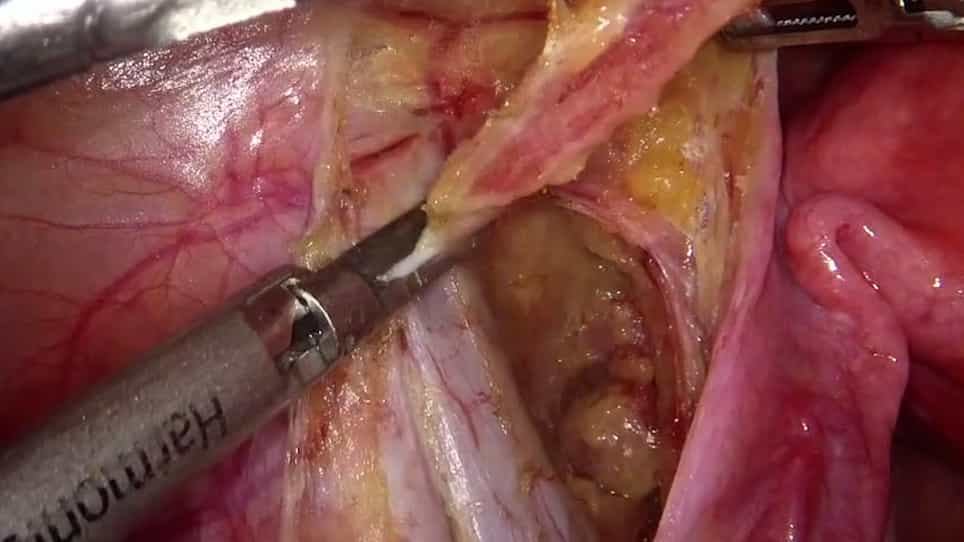
Sentinel Lymph Node Mapping and Biopsy for Endometrial Cancer at Early Stage with Laparoscopy
Published on: August 19, 2021
The Prognostic Role of Lymphadenectomy during Esophagectomy for Esophageal Cancer with Complete or Near-Complete
Wilhelm Leijonmarck1, Fredrik Mattsson2, Eivind Gottlieb-Vedi2
1Department of Molecular Medicine and Surgery, Karolinska Institutet, Karolinska University Hospital, Stockholm, Sweden. wilhelm.leijonmarck@ki.se.

Background:
The prognostic role of lymphadenectomy during esophagectomy for esophageal cancer in complete responders to neoadjuvant therapy is uncertain. This study aimed to help clarify this question.
Patients And Methods:
This was a bi-national population-based cohort study in Sweden (2006-2024) and Finland (2006-2019). The main cohort included 515 patients with esophageal cancer who underwent esophagectomy after complete or near-complete tumor response without lymph node metastasis following neoadjuvant therapy. A secondary cohort included 669 patients with similar tumor response, regardless of nodal status. Data came from medical records and national health data registers. Associations between lymphadenectomy (categorized in quartiles) and 5-year mortality were assessed using multivariable Cox regression, yielding hazard ratios (HR) with 95% confidence intervals (CI), adjusted for age, sex, country, comorbidity, type of neoadjuvant therapy, calendar year, tumor histology, hospital volume, tumor location, tumor response, and T stage.
Results:
In the main cohort, comparing the highest quartile of lymphadenectomy (≥ 27 nodes) with the lowest (0-11 nodes) indicated decreased 5-year all-cause mortality (HR 0.54, 95% CI 0.34-0.88). Stratified analyses suggested no significant association for complete responders (HR 0.68, 95% CI 0.39-1.16), but for near-complete responders (HR 0.32, 95% CI 0.14-0.72). The associations disappeared when assessing stage purification bias in the secondary cohort (n = 669), with the corresponding HRs of 0.91 (95% CI 0.63-1.32) for all responders, 1.01 (95% CI 0.61-1.66) for complete responders, and 0.79 (95% CI 0.47-1.33) for near-complete responders. Results were similar for 5-year disease-specific mortality.
Conclusions:
After considering stage purification bias, more extensive lymphadenectomy did not improve the long-term survival among patients with complete or near-complete tumor response after neoadjuvant therapy.
More Related Videos
 07:45
Author Spotlight: A Model to Study the Systemic and Local Dynamics of CD8+ T Cells During LN Metastasis
Published on: January 26, 2024
 07:13
Comparison of Predictive Performance of Three Lymph Node Staging Systems in Colorectal Signet Ring Cell Carcinoma Based on Machine Learning Model
Published on: April 18, 2025
Related Concept Videos
 01:29
Appendicitis-II: Diagnostic Studies and Management
Diagnosing Appendicitis
It requires a multifaceted approach, starting with a detailed physical examination to pinpoint the location and nature of the pain and identify any associated symptoms. Laboratory tests play a crucial role. A complete Blood Count (CBC) typically reveals leukocytosis (an increased number of...
 01:25
Peptic Ulcer Disease V: Surgical Management and Nursing Care
Surgical Interventions for Peptic Ulcer Disease
 01:26
Endoscopic Procedures IV: Sigmoidoscopy and Laproscopy
Sigmoidoscopy
Sigmoidoscopy is a diagnostic procedure that uses a flexible sigmoidoscope equipped with a light source and camera to examine the rectum and sigmoid colon. The procedure involves inserting the tube through the anus...