Related Experiment Video
Updated: Jan 12, 2026


Evaluation of Patients' Posture and Gait Profile After Lumbar Fusion Surgery by Video Rasterstereography and Treadmill Gait Analysis
Published on: March 23, 2019
Pelvic position significantly influences the segmental lumbar lordosis: a cross-sectional study in asymptomatic
SiYu Zhou1,2, YuDong Zhao1,2, Yi Zhao1,2
1Peking University Third Hospital, Beijing, China.

Purpose:
In the concept of lumbar surgical planning, it was often seen as a linear relationship between Pelvic Incidence (PI) and Lumbar Lordosis (LL) that a bigger PI referred to a larger LL. While the discovery and high prevalence of pelvic anteversion (AP) population indicated otherwise. The goal of this study was to investigate the influence of pelvic anteversion on lumbar sagittal parameters and elucidate the different PI-related lordosis patterns in asymptomatic population.
Methods:
A total of 405 asymptomatic subjects were divided by their pelvic property into 2 groups: the anteverted pelvis (AP) group (n = 151) and the non-AP group (n = 254). Spinopelvic parameters including PI, pelvic tilt (PT), LL, sacral slope (SS), sagittal vertical axis (SVA), T1 Pelvic angle (TPA), thoracolumbar kyphosis (TLK), lumbar tilt (LT), lumbar lordosis distribution (LDI) and segmental lordosis were measured in whole spine radiographs. Propensity score matching (PSM) was used to establish a PI-balanced cohort. Subsequently, the differences of spinopelvic parameters were assessed between AP and non-AP group. We also conducted a stratified analysis to explore the relationship between different pelvic incidence (PI) levels and segmental lordosis.
Results:
The AP group showed distinct sagittal parameters and PI-related lordosis patterns comparing to non-AP group. The AP group showed lower PI (41.5°±6.0°), PT (4.7°±2.7°), and higher SS (37.3°±5.4°) and LL (53.0°±8.6°) than non-AP group. After propensity score matching, the cohort of 268 subjects showed no significant differences in demographic data (P > 0.1) or PI (P = 0.364) between the AP and non-AP groups. However, significant differences in PT, SS, LL, TPA, L5-S1, L4-5, L3-4, L2-3, upper lumbar lordosis (L1-4) and lower lumbar lordosis (L4-S1) were observed between the two groups (P < 0.01). Only L1-2 segmental lordosis displayed no significant difference between the 2 groups (P = 0.39). In addition, in each PI level, the AP group showed consistently greater LL and segmental lordosis compared to the non-AP group, with the most notable differences in the lower lumbar segments.
Conclusion:
The AP group, characterized by lower PI and PT, and higher SS and LL, should be recognized as a distinct population from the non-AP group. This group also exhibits unique PI-related lordosis patterns, with consistently significant variations in segmental lordosis within each PI level compared to the non-AP group, particularly in the lower lumbar spine.
Related Concept Videos
 01:16
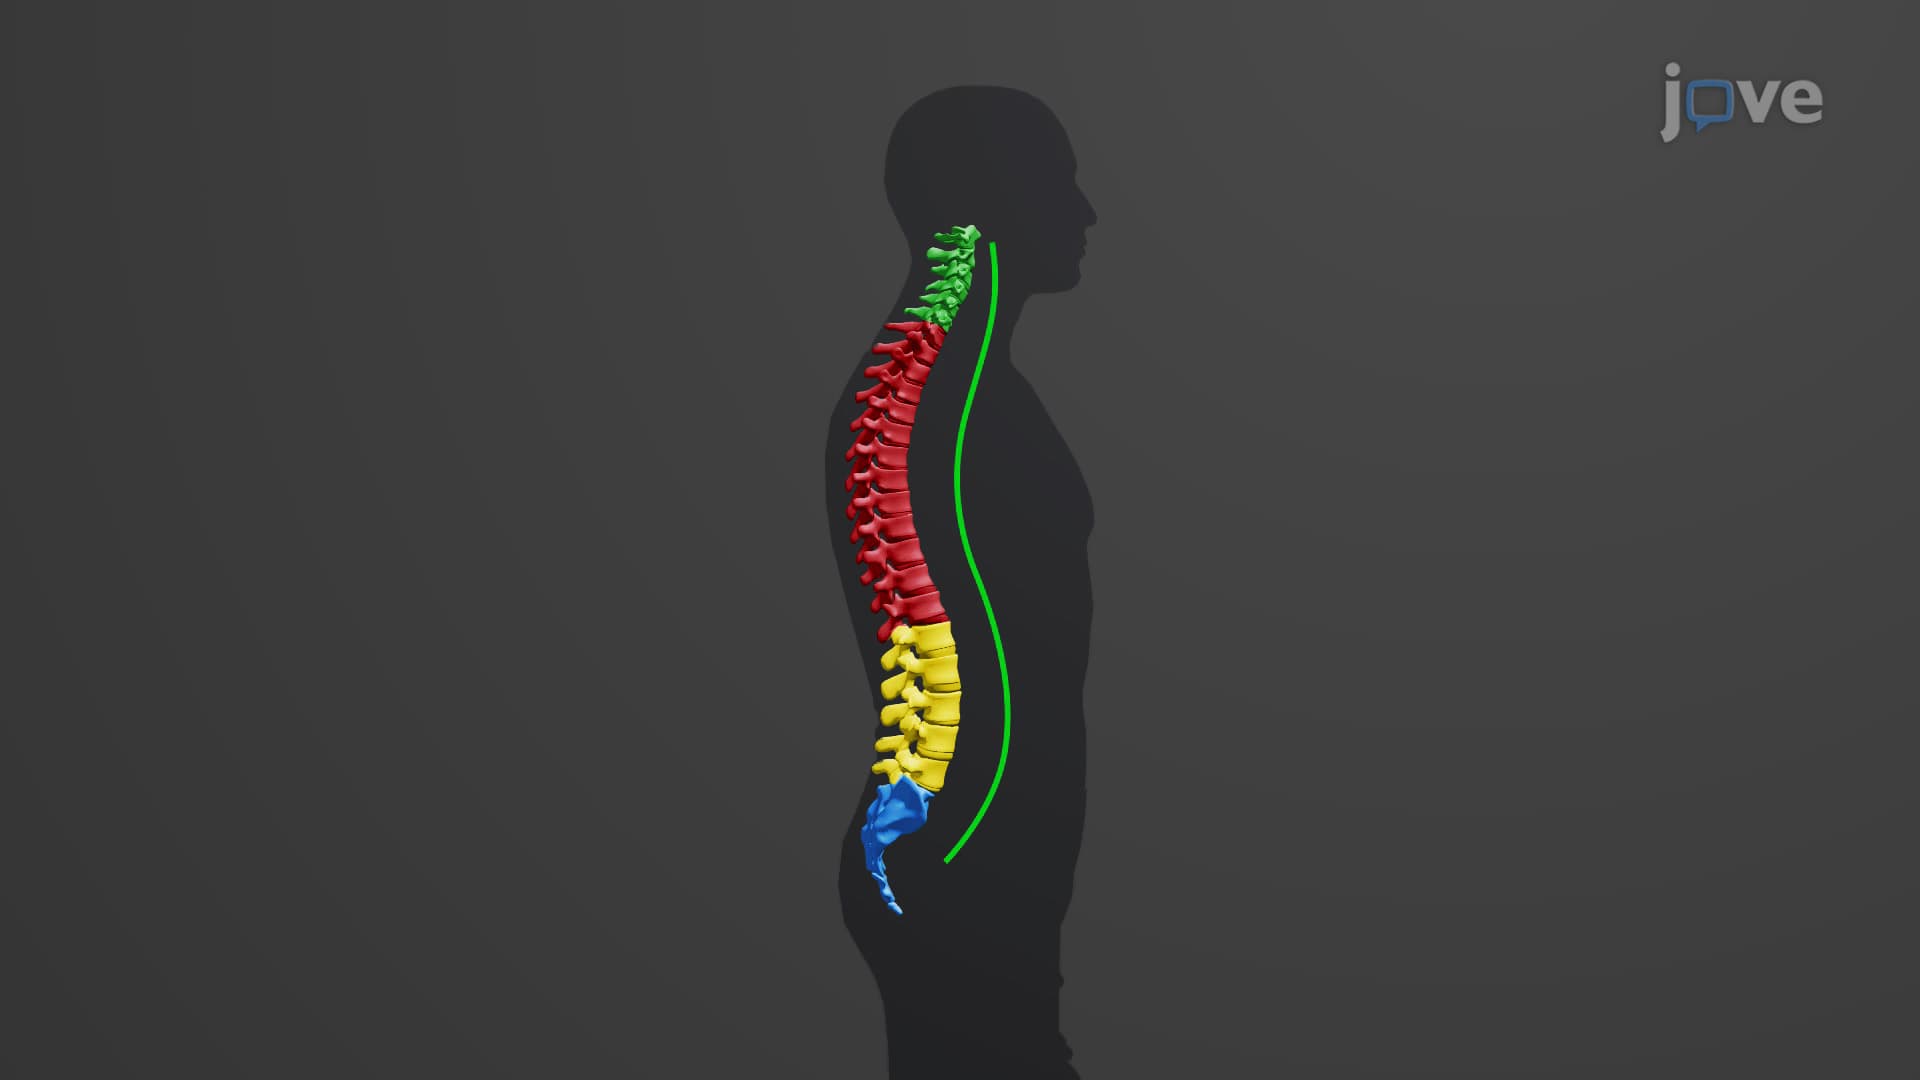
Vertebral Column: Regions and Curvature
Regions of the Vertebral Column
In an adult, the spine is subdivided into five regions: the cervical, the thoracic, the lumbar, the sacral, and the coccygeal region. The spine initially develops as a series of 33 vertebrae; after 20 years of age, the nine bones in the sacral region, five sacral, and four coccygeal bones fuse to form...
 01:19
Abdominal Regions and Quadrants
The simpler quadrants approach, which is more commonly used in medicine, subdivides the cavity with one horizontal and one vertical line that intersects at the patient's umbilicus (navel). The four...