Related Experiment Video
Updated: Jan 11, 2026
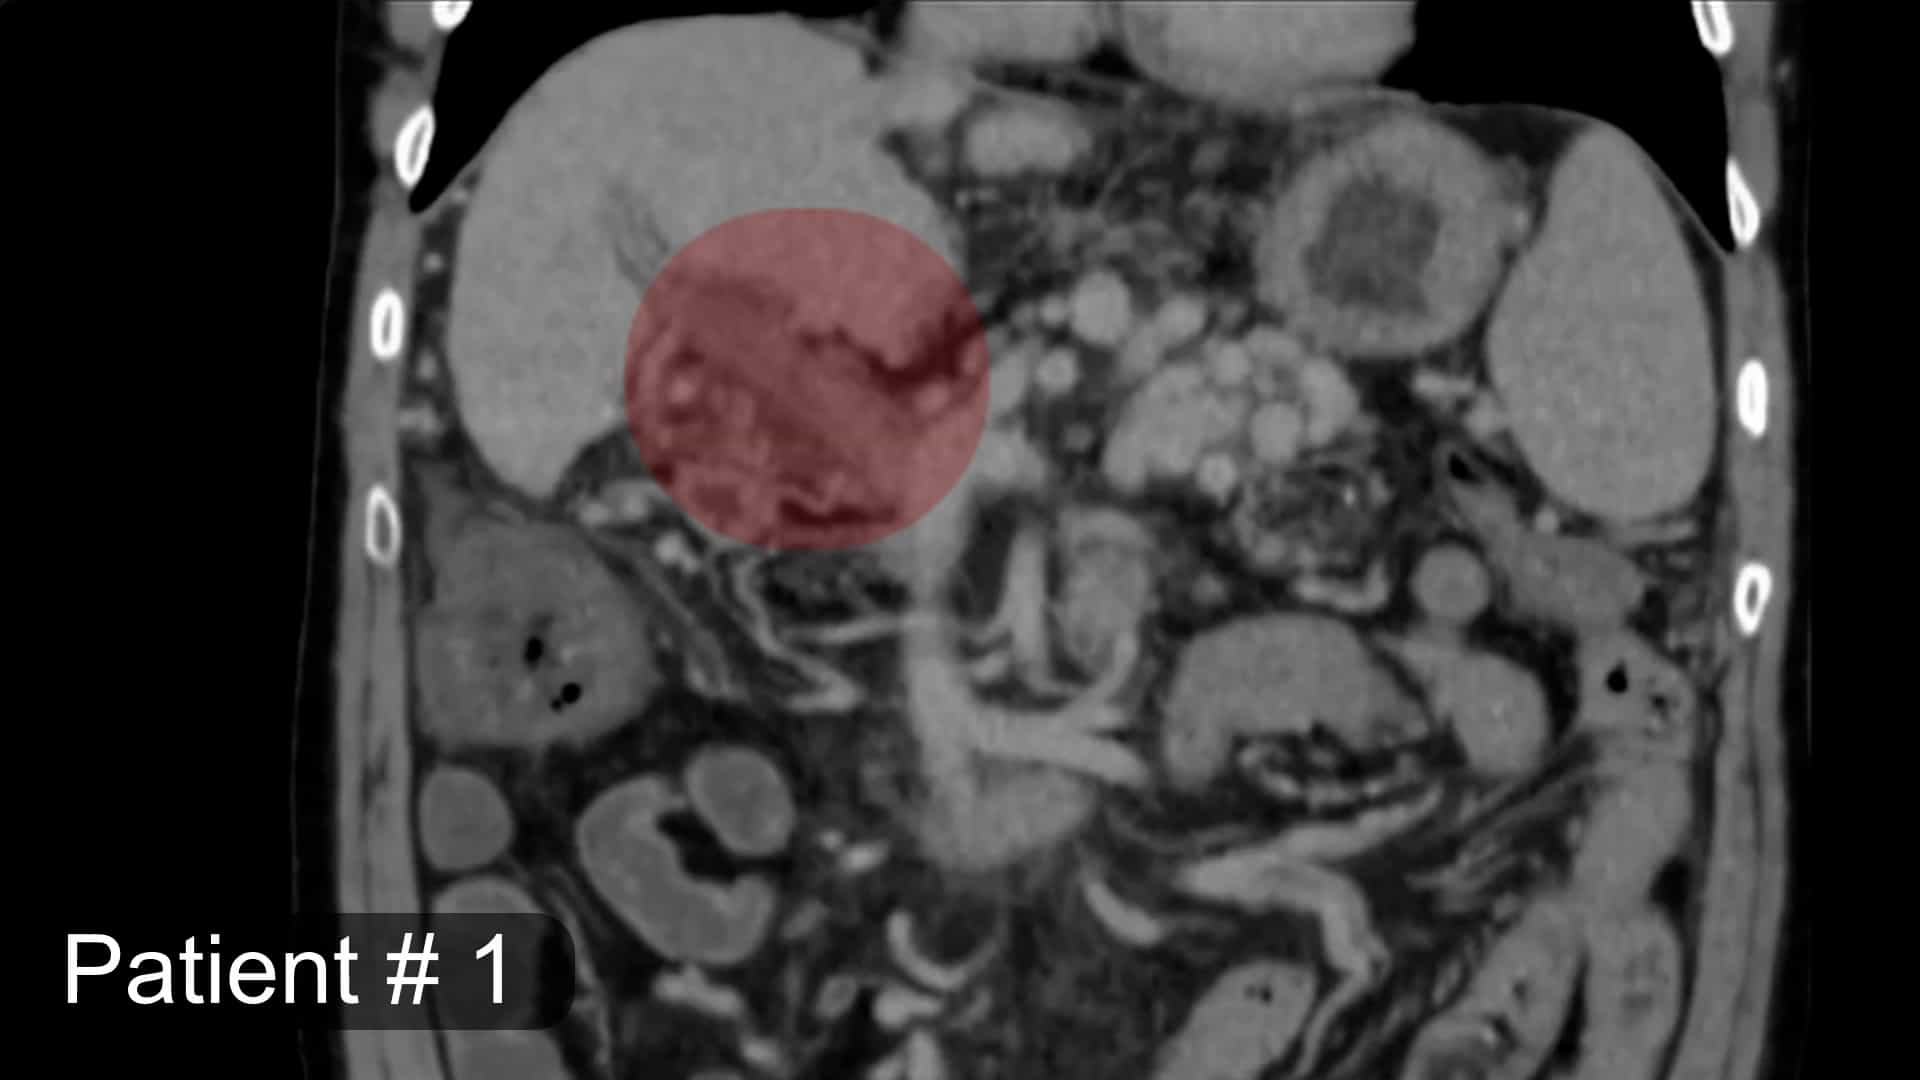
New Thrombectomy Technique for Total Portal Vein Thrombosis in Liver Transplantation
Published on: June 27, 2025
A Case of Right Hepatic Vein Thrombus with Spontaneous Peripheral Shunt Successfully Treated via Left
Takahiro Shoda1, Kenichiro Araki1, Norihiro Ishi1
1Division of Hepatobiliary and Pancreatic Surgery, Department of General Surgical Science, Gunma University Graduate School of Medicine, Maebashi, Gunma, Japan.

Introduction:
Left trisectionectomy with bile duct resection is a high-risk procedure that requires thorough preoperative evaluation to prevent postoperative liver failure. In addition, there are a few reports of highly invasive hepatectomy in cases where hepatic vein thrombosis is present preoperatively.
Case Presentation:
In a 58-year-old man, papillary epithelium was detected in the left hepatic duct during a bile duct biopsy, and the anterior segment of Glisson's capsule was compressed by the cystic components. Left trisectionectomy with bile duct resection was planned, based on a diagnosis of intraductal papillary neoplasm of the bile duct (IPNB). In our department, portal vein embolization (PVE) is essential when considering left trisectionectomy with bile duct resection, so surgery was scheduled after PVE. However, CT after PVE showed thrombus formation in the right hepatic vein (RHV), which persisted despite the initiation of anticoagulant therapy. Owing to the absence of a major drainage vein and the risk of postoperative liver failure, the patient was treated with gemcitabine + cisplatin + S-1 therapy. CT after chemotherapy still showed RHV thrombosis, along with newly developed peripheral venous shunt formation between the obliterated RHV branches. After 6 months, the same findings were observed, and as the tumor had shrunk, the case was deemed resectable. Left trisectionectomy with bile duct resection was performed. Pathological diagnosis confirmed IPNB (pTisN0M0, pStage 0 according to the Union for International Cancer Control, 8th edition). Following adjuvant chemotherapy, the patient developed pulmonary metastases, which were surgically resected. As of 38 months post-hepatectomy, the patient remains cancer-free.
Conclusions:
We encountered a case in which left trisectionectomy with bile duct resection was possible owing to the formation of an RHV shunt, enabling resection of both the primary and recurrent lesions. Continuous imaging is essential for the dynamic assessment of resectability.
More Related Videos
 06:00
Laparoscopic Anatomic S7+S8d Resection Preserving Inferior Right Hepatic Vein and S6 with Right Hepatic Vein Transection
Published on: December 30, 2025
 03:45
Right Hemihepatectomy by Suprahilar Intrahepatic Transection of the Right Hemipedicle using a Vascular Stapler
Published on: January 25, 2010
