Related Experiment Video
Updated: Jul 27, 2026


Three-Dimensional Reconstruction of Orbital Fractures
Published on: May 16, 2025
Endoscopic-assisted elevation of orbital blowout fracture in children: a case report
Mohd Faizal Abdullah1,2, Fattirah Auni Fauzi1,2, Sakinah Mohamad3
1Oral and Maxillofacial Surgery Unit, School of Dental Sciences, Universiti Sains Malaysia, Health Campus, Kota Bharu, Malaysia.

Insights
Pediatric orbital floor fractures require prompt surgical intervention to prevent permanent vision issues. Endoscopic-assisted repair offers a safe and effective treatment for these injuries, restoring ocular function.
Area of Science:
- Ophthalmology
- Pediatric Surgery
- Trauma Surgery
Background:
- Orbital fractures in children are rare but present unique challenges compared to adults.
- Orbital wall fractures with muscle entrapment are surgical emergencies due to risks of permanent diplopia.
- Pediatric orbital floor injuries have distinct features affecting presentation and management.
Background:
Orbital fractures in children are uncommon. The existing literature shows a wide range of estimates for incidence, etiology, management protocols, and outcomes. Nevertheless, it is widely accepted that orbital wall fractures with extraocular muscle entrapment is a surgical emergency due to the risk of permanent diplopia caused by ischemia and necrosis of the muscle. Pediatric orbital floor injuries have distinct mechanistic features and fracture patterns when compared to adults. As a result, the prevalence, typical presenting signs and symptoms, and management considerations for pediatric orbital floor fractures differ from those for adults.
Case Description:
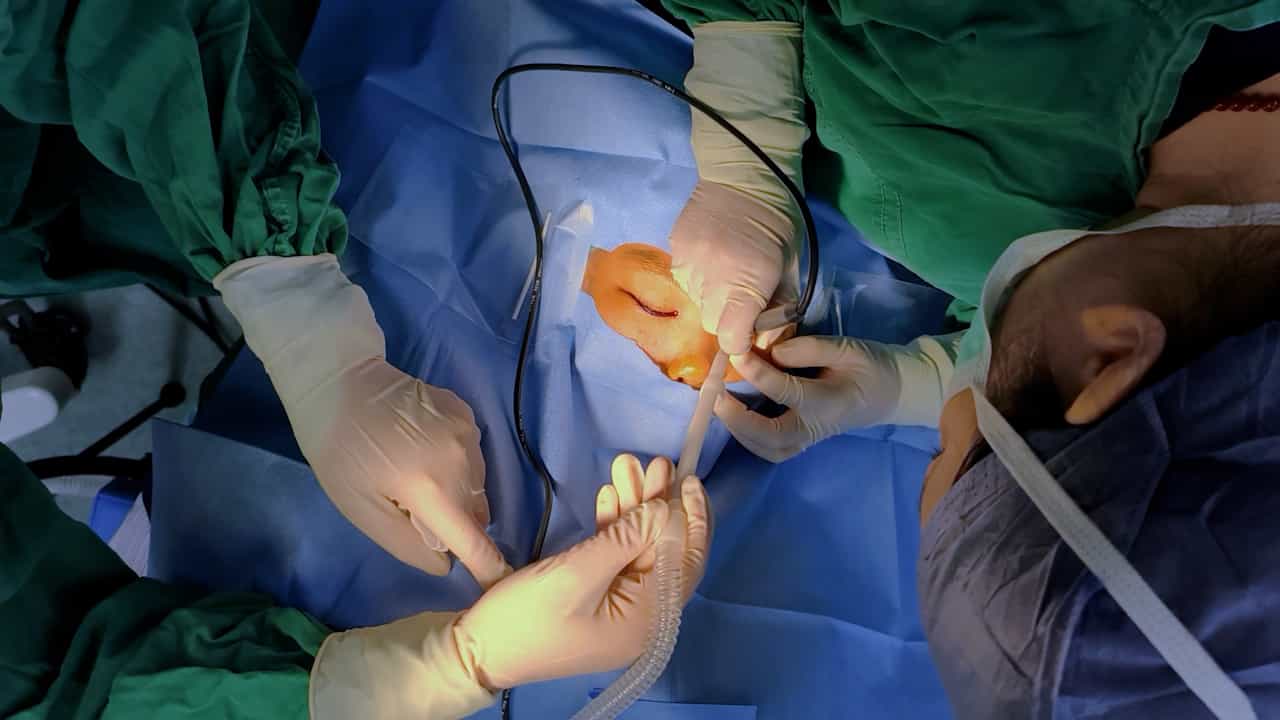
We report the case of a 7-year-old boy with a right orbital floor fracture presenting with restricted upward gaze and binocular diplopia. A computed tomography (CT) scan revealed a linear fracture with herniation of orbital contents into the maxillary sinus. Surgical management was performed via a transconjunctival approach assisted by endoscopic lighting, allowing accurate identification and repositioning of the fractured segment. Postoperative recovery was uneventful, with complete resolution of diplopia and restoration of ocular motility.
Conclusions:
Endoscopic-assisted repair of linear orbital floor blowout fractures through a transconjunctival approach seems to be a safe and effective method for treating orbital blowout fractures in children. If the bone is not comminuted, the pediatric orbital floor fracture can be repositioned with careful dissection and preservation of the periosteum.