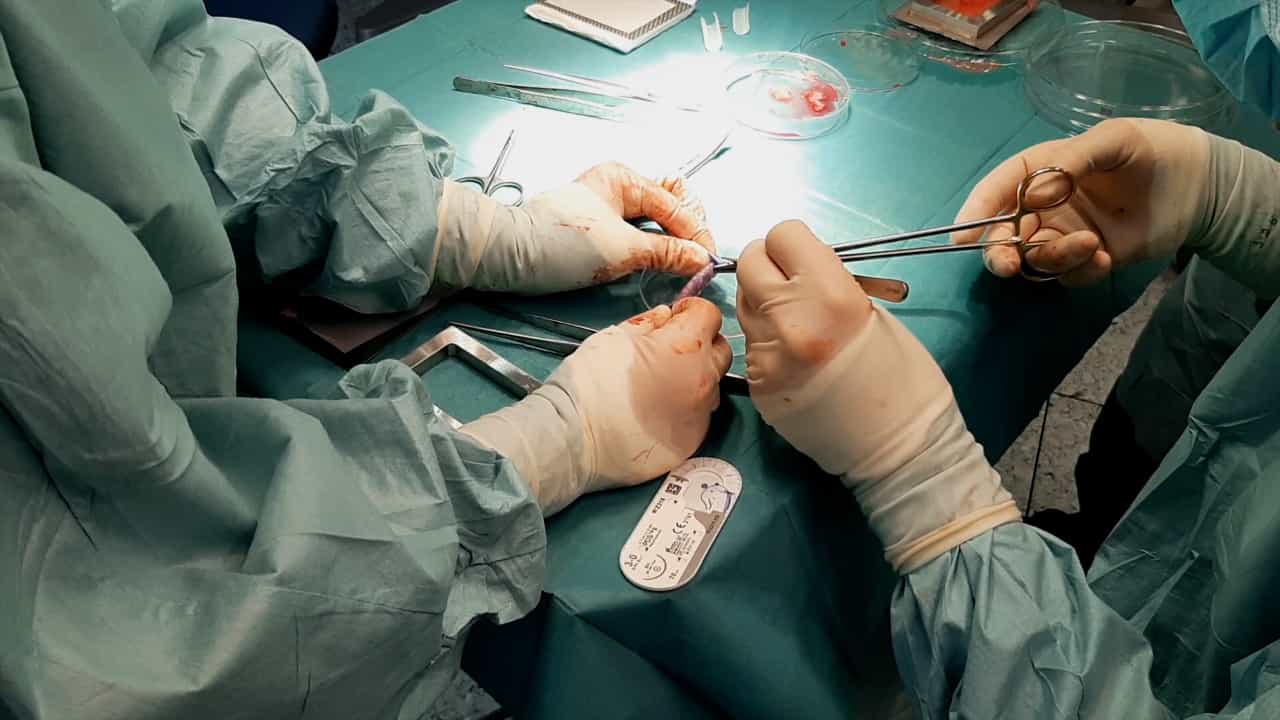
Related Experiment Video
Updated: Jan 11, 2026


Urethral Stricture Induction Followed by Buccal Mucosa Graft Urethroplasty in a Rat Model
Published on: April 28, 2023
Expanding the Armamentarium: Perspectives on Buccal Mucosal Grafts and Appendiceal Flaps in Ureteral Reconstructive
Dario Bello1, Monica Van Shufflin1, Matthias D Hofer2
1Department of Urology, University of Texas Health San Antonio, San Antonio, TX 78229, USA.

Abstract:
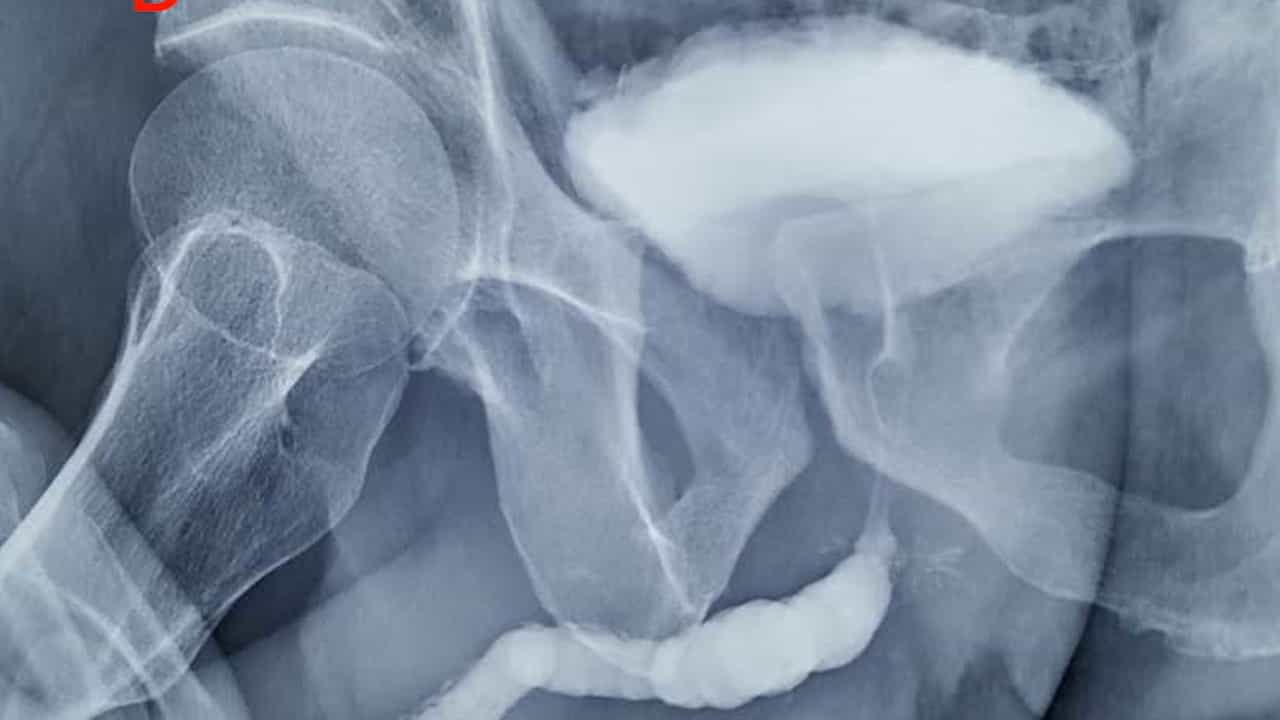
Management of complex and recurrent ureteral stricture disease remains one of the more challenging aspects of reconstructive urology. While standard techniques such as ureteroureterostomy, psoas hitch, Boari flap, and ileal ureter creation serve as the foundation of ureteral reconstruction, each technique has limitations, particularly when faced with recurrence, long strictures, and previously irradiated fields. Two alternative techniques-buccal mucosal graft (BMG) ureteroplasty and appendiceal onlay/interposition-have been previously described and are now being utilized more frequently in recent years. Furthermore, the advancement of robotic-assisted laparoscopic surgery has allowed for even more reconstructive capabilities. BMG ureteroplasty and appendiceal onlay/interposition can serve as valuable augmentations to the aforementioned surgical techniques. BMG has now long been established in urethral reconstruction and serves as a viable graft option for longer segment ureteral strictures, given its panvascular lamina propria and epithelium well-suited to a wet environment. Similarly, the appendix has other uses in urologic surgery, including the Mitrofanoff channel in pediatric surgery, and is chiefly used in right-sided ureteral stricture repair. Both of these techniques allow the surgeons to take on more complex ureteral stricture cases and avoid the morbidity of bowel harvest. In this perspective, we argue for a broader recognition and adoption of BMG and appendiceal onlay/interposition in ureteral reconstructive surgery. In this article, we highlight the rationale for use, technical considerations, outcomes, and clinical evidence suggesting their advantages over traditional approaches. By incorporating these techniques into practice, urologists can expand their ability to manage more complex ureteral stricture cases with improved outcomes.