Related Experiment Video
Updated: Jan 11, 2026


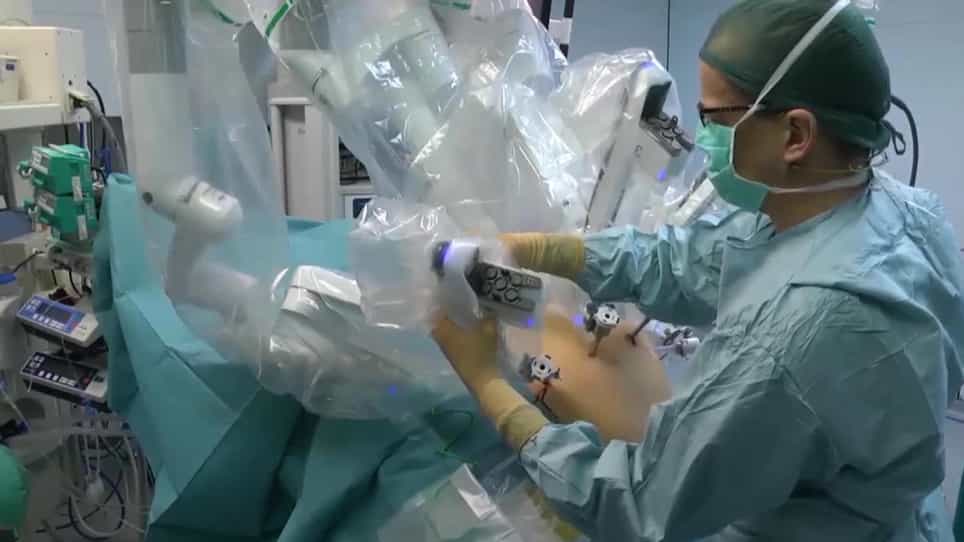
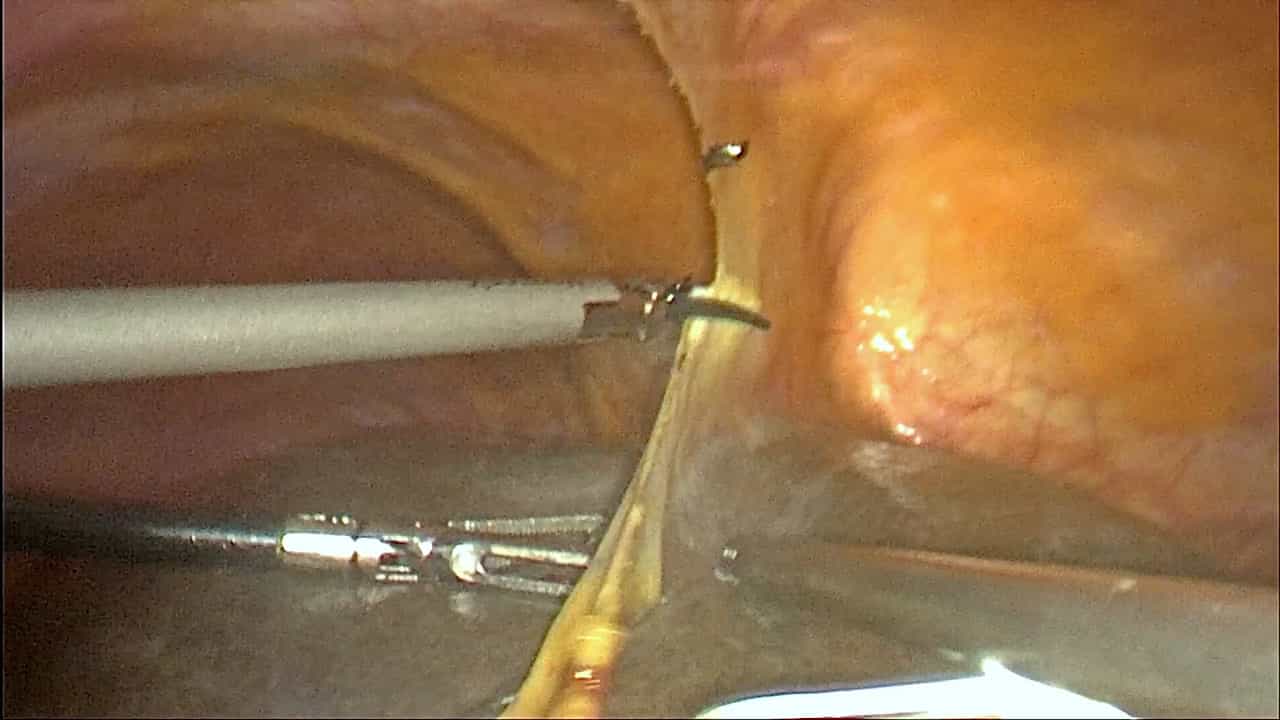
Retzius-Sparing Robot-Assisted Radical Prostatectomy
Published on: May 19, 2022
Partial vs. radical nephrectomy in pT3a renal cancer: Cancer-specific mortality according to fat invasion pattern
Michele Nicolazzini1, Calogero Catanzaro2, Federico Polverino3
1Cancer Prognostics and Health Outcomes Unit, Division of Urology, University of Montréal Health Center, Montréal, Québec, Canada; Division of Urology, Department of Translational Medicine, University of Eastern Piedmont, Maggiore della Carità Hospital, Novara, Italy; Division of Urology, Department of Oncology, University of Turin, Turin, Italy.

Introduction:
Within the SEER database (2010-2021), we tested for differences in cancer-specific mortality (CSM) between partial (PN) vs. radical (RN) nephrectomy in patients with pT3a renal cell carcinoma with either perinephric fat invasion (PFI) or sinus fat invasion (SFI).
Patients And Methods:
Separate propensity score matching (PSM), multivariable competing risk regression (mCRR) analyses and cumulative incidence plots addressed CSM in patients with PFI and subsequently in patients with SFI, according to PN vs. RN. Subgroup analyses focused on patients with additional adverse pathological features: tumor size >4 cm, high nuclear grade or sarcomatoid dedifferentiation.
Results:
Of 9,664 pT3aN0M0 RCC patients with fat invasion, 4379 (45.3%) had exclusive PFI vs. 4398 (45.5%) had exclusive SFI. In PFI patients, 1,321 (30.2%) patients underwent PN vs. 3,058 (69.8%) RN. After 1:1 PSM, 5-years CSM rates were 8.2 vs. 9.3% in PN vs. RN patients. In mCRR, PN vs. RN did not affect CSM (HR 0.99, P = 0.9), even in patients with additional adverse pathological features. In SFI patients, 395 (9.0%) patients underwent PN vs. 4003 (91.0%) RN. After 1:3 PSM, 5-years CSM rates were 7.5 vs. 10.3% in PN vs. RN patients. In mCRR, PN vs. RN did not affect CSM (HR 0.74, P = 0.2), even in patients with additional adverse pathological features.
Conclusion:
PN does not predispose patients to a survival disadvantage in presence of either PFI or SFI, even in those with additional adverse pathological features defined as tumor size >4 cm, high nuclear grade or sarcomatoid dedifferentiation.