Related Experiment Video
Updated: Jan 10, 2026
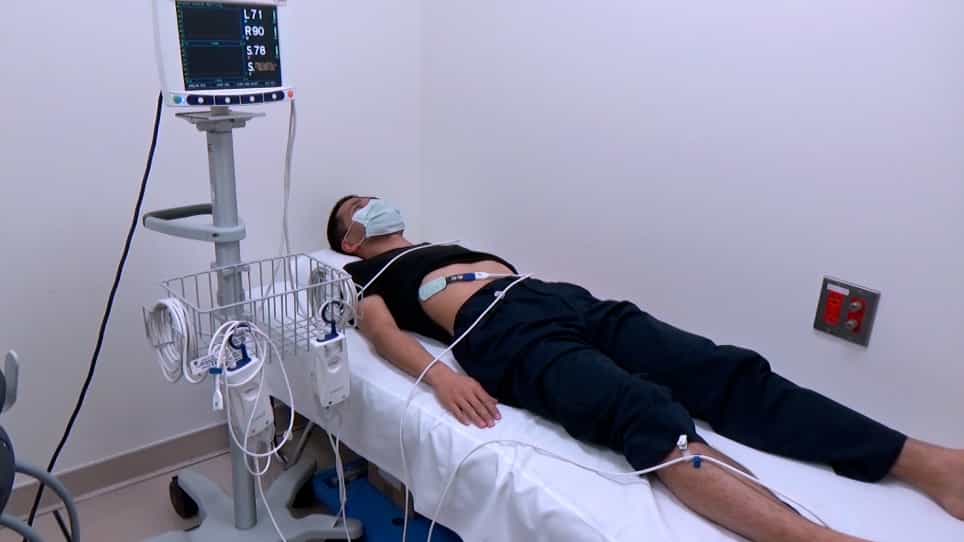

Measurement of Tissue Oxygenation Using Near-Infrared Spectroscopy in Patients Undergoing Hemodialysis
Published on: October 2, 2020
Total bilirubin as a mortality predictor in non-elderly hemodialysis patients: a multicenter retrospective cohort
Yuyang Chen1,2, Haowen Zhang3, Hongyan Liu1
1NHC Key Lab of Hormones and Development and Tianjin Key Lab of Metabolic Diseases, Tianjin Medical University Chu Hsien-I Memorial Hospital & Institute of Endocrinology, Tianjin, 300134, China.

Background:
The association between serum total bilirubin (TBIL) levels and mortality in maintenance hemodialysis (MHD) patients, especially when stratified by age, has not been clearly established.
Methods:
We performed a multicenter retrospective analysis of 409 MHD patients (40 deaths, 9.8%) over a median follow-up of 31.3 months (interquartile range (IQR), 28.9-31.8). Cox regression models evaluated TBIL's predictive role for mortality. Receiver operating characteristic (ROC) curve-derived cutoff (8.79 µmol/L) stratified patients into high (H, TBIL > 8.79 µmol/L, n = 236) and low (L, TBIL ≤ 8.79 µmol/L, n = 173) groups. Multivariable Cox models adjusted for demographics, comorbidities (Model 2), and laboratory markers (Model 3). Additionally, to mitigate overfitting and assess the linear relationship, a LASSO-penalized Cox model was employed, treating TBIL as a continuous variable. Kaplan-Meier analysis compared survival rates, with age subgroup comparisons.
Results:
Significant differences emerged between H and L groups in hypertension history, platelet count, total protein, blood urea nitrogen, triglycerides, and total cholesterol (all P < 0.05). Adjusted models revealed elevated mortality risk in high TBIL patients (HR = 6.92, 95%CI 3.10-15.43, P < 0.001). Consistently, in the continuous analysis, each 1 µmol/L increase in TBIL was associated with a 26% increased mortality risk (HR = 1.26, 95%CI 1.16-1.38, P < 0.001). Age-stratified analysis revealed substantially increased mortality risk in non-elderly high-TBIL patients (HR = 12.82, 95%CI 3.76-43.76, P < 0.001), but no significant association in elderly patients (HR = 2.00, 95%CI 0.83-4.81, P = 0.12).
Conclusion:
TBIL independently predicts all-cause mortality in MHD patients, with exploratory evidence suggesting potentially stronger association in non-elderly patients.
Related Concept Videos
 01:22
Effect of Hepatic Disease on Pharmacokinetics: Pathophysiologic Assessment and Liver Function Test
 01:28
Drug Dosing in Renal Diseases: Estimation of Glomerular Filtration Rate Based on Serum Creatinine Concentration
 01:24
Serum Studies: Renal Function Tests
 01:18
Pharmacokinetics in Geriatric Patients: Effect of Age on Drug Excretion
 01:30
Acute Kidney Injury IV: Diagnostic Studies and Prevention
 01:24
Hemodialysis II: Procedure and Complications