Related Experiment Video
Updated: Jan 10, 2026
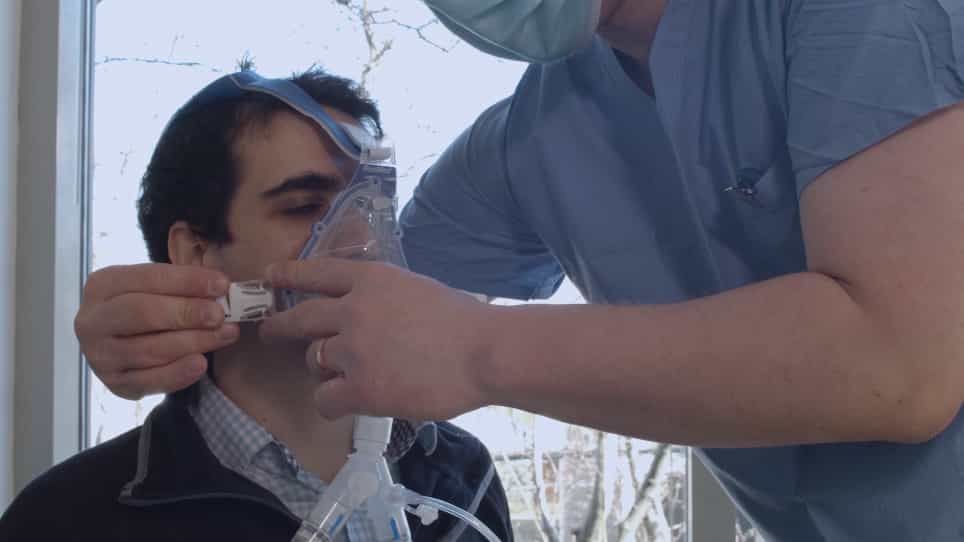

A Novel Inhalation Mask System to Deliver High Concentrations of Nitric Oxide Gas in Spontaneously Breathing Subjects
Published on: May 4, 2021
Adults with interstitial lung disease and acute respiratory failure without hypercapnia: when should high flow nasal
Laura White1,2, Maryam Ellam3, Rebecca Hickman3
1Lancaster Medical School, Lancaster University, Lancaster, England, UK laurajanewhite@doctors.org.uk.

Abstract:
Interstitial lung diseases (ILDs) represent a heterogenous group of disorders affecting the lung parenchyma. Patients with ILD are frequently admitted to hospital secondary to respiratory decompensation which can result in acute respiratory failure (ARF). High flow nasal oxygen (HFNO) has increasingly been used in other causes of ARF following the recommendations of the European Respiratory Society. A review was undertaken to evaluate the question: in adults with ILD and ARF without hypercapnia, is HFNO better than conventional oxygen therapy (COT) at reducing symptoms and all-cause mortality outcomes? Medline via PubMed, EMBASE via OVID and the Cochrane Library were searched between 1975 and 20 June 2025. 2362 papers were identified with 17 undergoing full-text review. Two systematic reviews met inclusion criteria and directly answered the three-part question. Study information, participant demographics, key results and study weaknesses were established for each paper. Neither systematic review found HFNO improved mortality outcomes, when compared with COT, to a statistically significant threshold for patients with ILD with ARF. Reported median survival with HFNO use was 21.0 days (95% CI 13.0 to 61.0) and COT use 133 days (95% CI 26.0 to 374.0, p=0.1323). Inpatient mortality with HFNO use ranged between 26.5% and 59.1%. Symptomatically, one review reported a numerical improvement in the Quality of Death and Dying Score for the HFNO group versus the COT group (4.58 ± 0.67 vs 4.09 ± 0.96). There is limited evidence to suggest that HFNO improves mortality outcomes for patients with ILD in ARF. However, it may be beneficial for symptom management. Mortality remains high despite HFNO use, thus careful discussions with patients and their relatives are required should a trial be used in the setting of ARF.
More Related Videos
 07:52
Expired CO2 Measurement in Intubated or Spontaneously Breathing Patients from the Emergency Department
Published on: January 29, 2011
 06:22
Surfactant Depletion Combined with Injurious Ventilation Results in a Reproducible Model of the Acute Respiratory Distress Syndrome ARDS
Published on: April 7, 2021
Related Concept Videos
 01:21
Acute Respiratory Failure-I
Definition: It is defined by specific criteria based on blood gas measurements. Hypoxemia happens when the partial pressure of oxygen (PaO2) falls below 60 mmHg. At the same time,...
 01:29
Acute Respiratory Failure-V
Ensure that patients are monitored continuously for their response to therapy, including changes in...
 01:21
Acute Respiratory Failure-II
The underlying physiological abnormalities that contribute to hypoxemic respiratory failure include:
 01:30
Acute Respiratory Failure-III
 01:16
Treatment for Pulmonary Arterial Hypertension: Oxygen Therapy for Respiratory Failure
Oxygen therapy is vital in increasing and maintaining blood oxygen levels in PAH patients. As a result, it aids in reducing fatigue,...
 01:26
Oxygen Delivering System I: Nasal Cannula and Face Mask
Nasal Cannula
A nasal cannula is a lightweight tube split at one end into two prongs and placed in the nostrils. It is typically used to deliver low to medium levels of oxygen.
Suggested flow rate: The suggested flow rate for a nasal cannula typically ranges between 1 and 6 L/min.
Oxygen percentage setting:...