Related Experiment Video
Updated: Jan 10, 2026


Author Spotlight: Integrating Alveolar-Capillary Reserve Measurements in Exercise Adaptation and Therapeutic Strategies
Published on: February 2, 2024
Limited Ventilatory Reserve During Exercise in Heart Failure with Preserved Ejection Fraction: Impact of Lung Size
Gizem Cifci1, Daniel J Brown1, Barry A Borlaug1
1Department of Cardiovascular Medicine, Mayo Clinic, Rochester, MN.

Background:
Patients with heart failure with preserved ejection fraction (HFpEF) exhibit a tachypneic breathing strategy during exercise. Patients with HFpEF have pulmonary system alterations that may contribute to the breathing strategy in HFpEF.
Research Question:
Do patients with HFpEF have limited ventilatory reserve compared with control patients during exercise? Furthermore, does greater upper body adiposity contribute to the lower ventilatory reserves in HFpEF?
Study Design And Methods:
Patients with HFpEF (n = 16; mean age ± SD, 70 ± 8 years) and control patients (n = 19; mean age ± SD, 69 ± 8 years) performed incremental cycling to volitional exhaustion. Trunk percent fat was quantified with dual-energy X-ray absorptiometry. Inspiratory capacity, inspiratory and expiratory reserve volumes, and ventilatory variables were compared between groups at rest and during exercise at 40 W and peak oxygen uptake.
Results:
Patients with HFpEF had lower total lung capacity (5.4 ± 1.1 vs 6.4 ± 1.2 L), FVC (3.1 ± 0.7 vs 3.8 ± 0.6 L), and FEV1 than control patients (all P < .04), respectively. During exercise at 40 W, patients with HFpEF had higher breathing frequency and smaller inspiratory reserve volume (1.2 ± 0.4 vs 1.5 ± 0.3 L) and expiratory reserve volume (0.9 ± 0.4 vs 1.1 ± 0.5 L) than control patients (both P < .05), respectively. At peak oxygen uptake, inspiratory and expiratory reserve volumes were not different between groups (both P > .21), but patients with HFpEF had lower end-inspiratory lung volume (P = .02). Patients with HFpEF had higher trunk percent fat than control patients (49% ± 7% vs 40% ± 8%, respectively; P < .01). Percent trunk fat was related to % predicted FVC (r = -0.57) and tidal volume to FVC ratio during exercise at 40 W (r = 0.53) for patients with HFpEF (both P < .04) but not control patients (both P > .72).
Interpretation:
These findings demonstrate that patients with HFpEF have limited ventilatory reserve during exercise, in part due to their smaller lung capacity. Furthermore, our findings suggest that the greater distribution of upper body adiposity in HFpEF is an important contributor to the smaller lung capacity for these patients.
More Related Videos
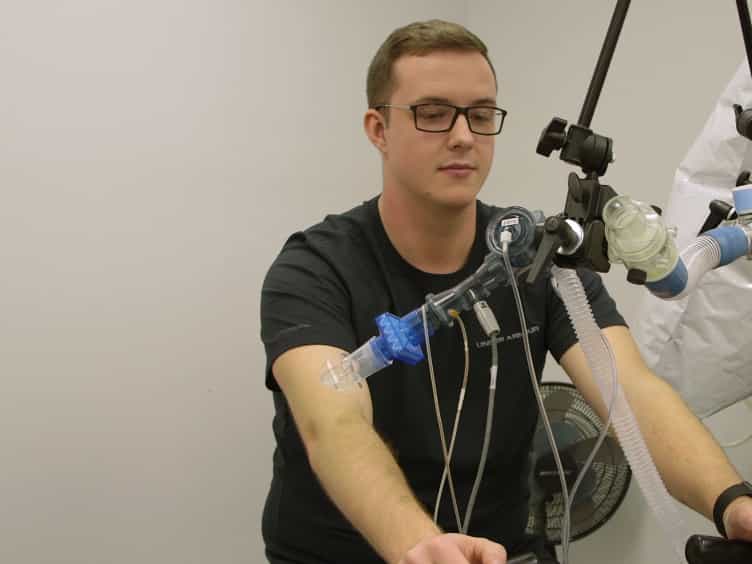 07:09
Assessment of Pulmonary Capillary Blood Volume, Membrane Diffusing Capacity, and Intrapulmonary Arteriovenous Anastomoses During Exercise
Published on: February 20, 2017
 05:56
Author Spotlight: Enhancing Diagnostic Strategies and Biomarker Development for Comprehensive Lung Function Analysis
Published on: August 9, 2024
Related Concept Videos
 01:47
Lung Capacity
 01:19
Factors Affecting Pulmonary Ventilation
Alveolar Surface Tension
The alveolar fluid lines the luminal surface of the alveoli and exerts a force called surface tension. This force is caused by the polar water molecules in the liquid being more strongly attracted to each...
 01:15
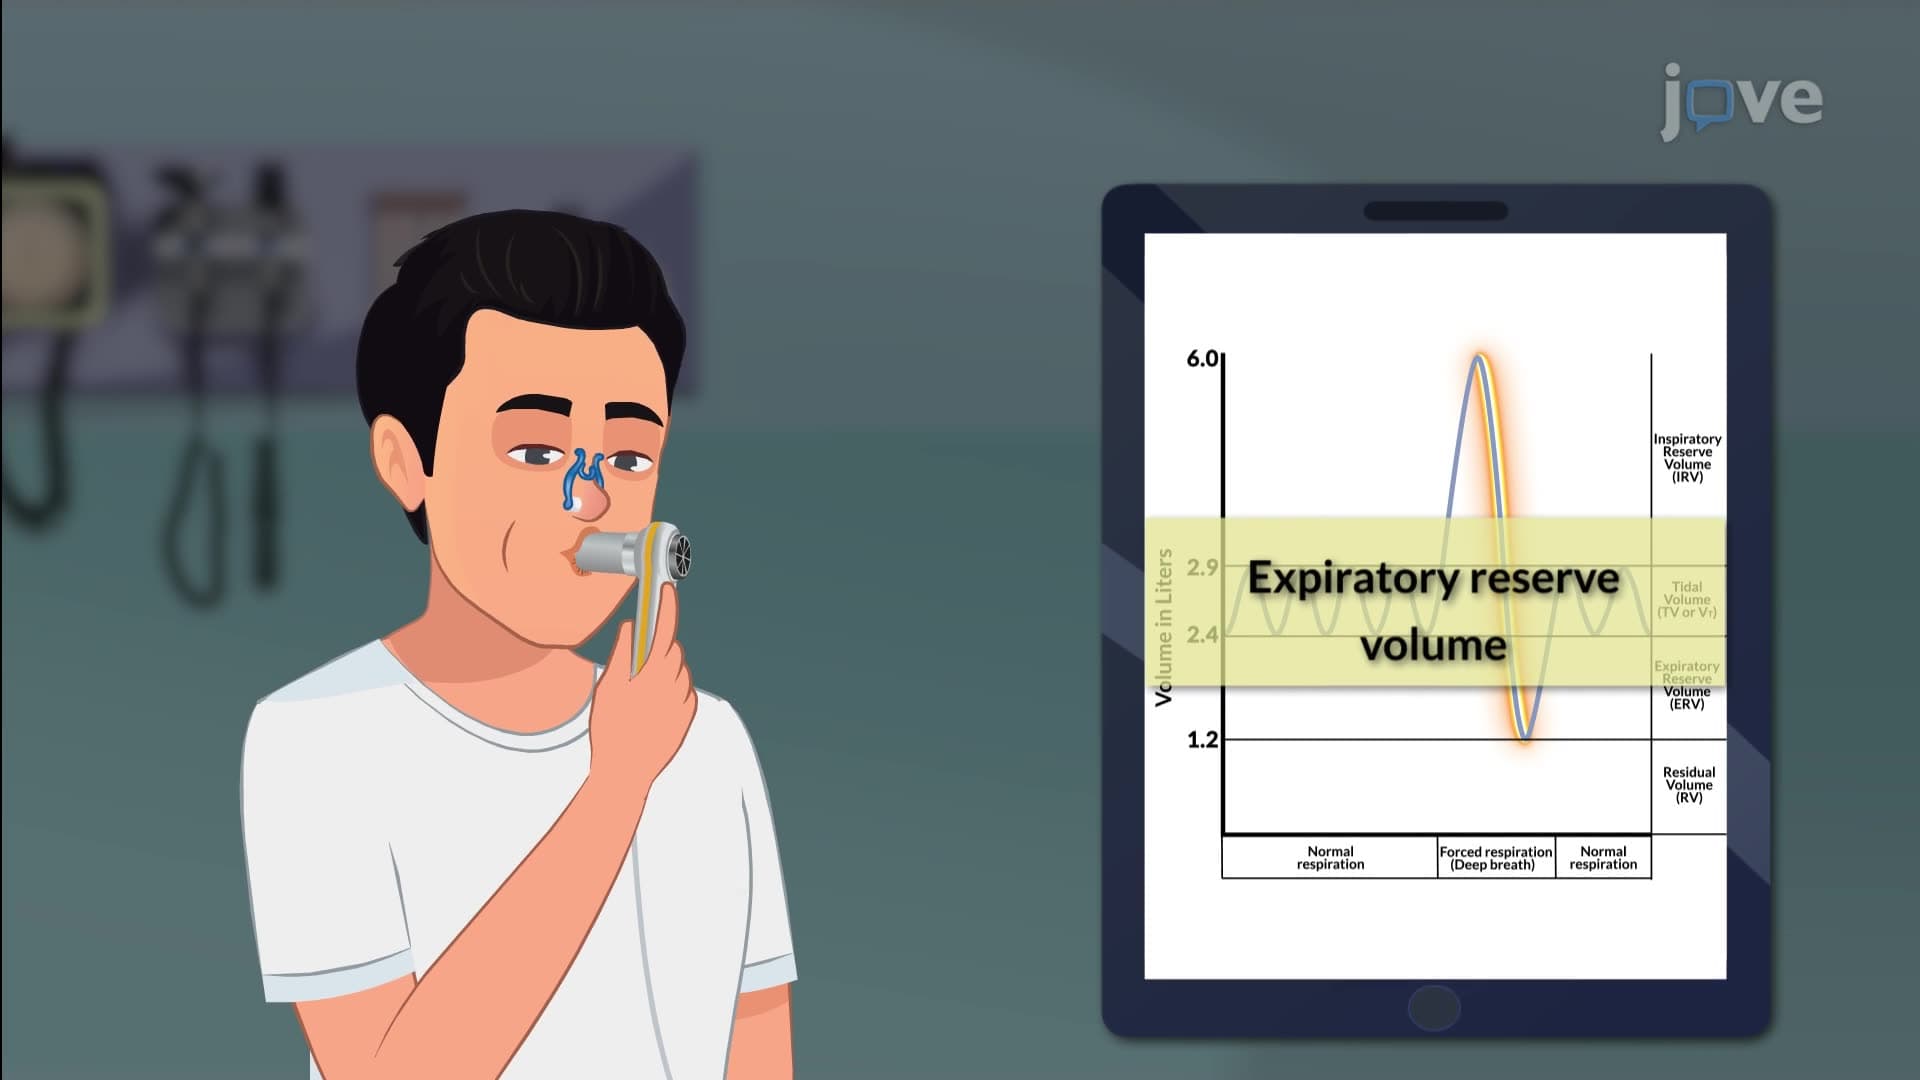
Respiratory Volumes
Tidal Volume (TV) Tidal volume (TV) is the air inhaled or exhaled in a...
 01:24
Respiratory Capacities
One key metric is the Inspiratory Capacity (IC), which represents the maximum amount of air that can be inhaled with full effort. IC is calculated by summing the tidal volume and inspiratory reserve volume, typically ranging from 2.4 to 3.6 liters.
The Functional Residual Capacity (FRC) represents the air in the...
 01:24
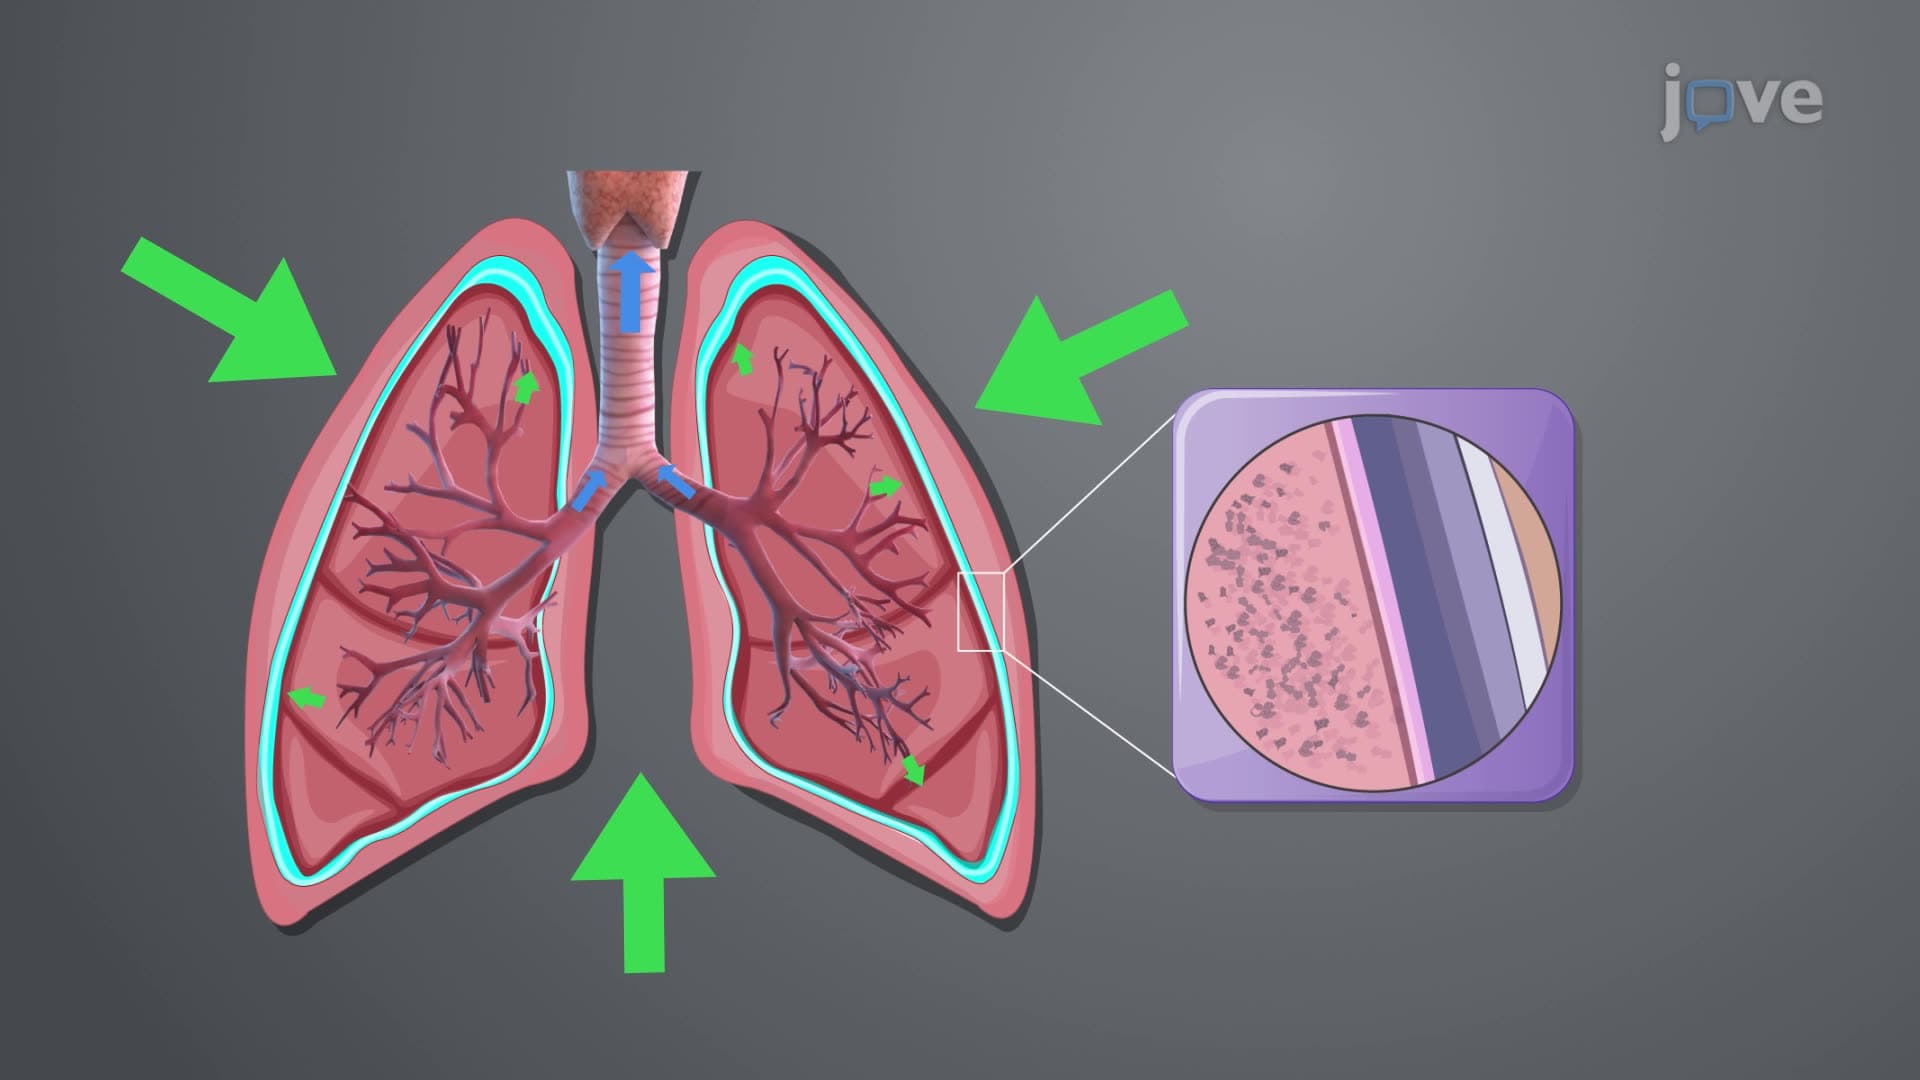
Pressure Relationships in Thoracic Cavity
Breathing Mechanisms
Both intra-alveolar and intrapleural pressures rely on specific lung properties. The ability to breathe—allowing air to enter the lungs...
 01:21
Acute Respiratory Failure-II
The underlying physiological abnormalities that contribute to hypoxemic respiratory failure include: