Related Experiment Video
Updated: May 1, 2026
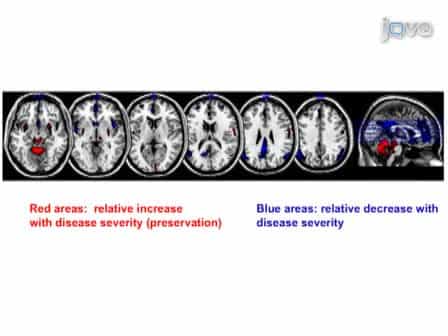

Basics of Multivariate Analysis in Neuroimaging Data
Published on: July 24, 2010
Multivariable model integrating PHI and mpMRI for detecting csPCa in biopsy-naïve men
Mario Dominguez Esteban1, Ester Fernandez Guzman1, Enrique Ramos Barselo1
1Department of Urology University Hospital Marques de Vadecilla-IDIVAL Santander Spain.

Background:
The integration of blood-based biomarkers and multiparametric magnetic resonance imaging (mpMRI) has been proposed to improve prostate cancer (PCa) diagnosis. However, few validated models combine both tools to support risk-adapted clinical decision-making.
Objective:
The study's aim is to evaluate and internally validate a multivariable model integrating clinical, analytical and imaging parameters-including the Prostate Health Index (PHI) and mpMRI-for predicting clinically significant prostate cancer (csPCa) in biopsy-naïve men.
Design Setting And Participants:
This prospective observational study included 183 biopsy-naïve men aged 50-75 years with PSA levels of 4-10 ng/mL and/or abnormal digital rectal examination. All patients underwent PHI testing, and 47.5% received prebiopsy mpMRI. All underwent systematic biopsy; targeted cognitive fusion biopsy was performed for PIRADS ≥ 3 lesions.
Outcome Measurements And Statistical Analysis:
A multivariable logistic regression model was constructed using PHI, PSA density, PSA free/total ratio, PIRADS score and age. The model was internally validated with bootstrap resampling and converted into a clinical nomogram. Diagnostic accuracy (AUC, sensitivity, specificity, NPV and PPV) was assessed and compared with simplified strategies using PHI or PIRADS alone, as well as a sequential approach (PHI → PIRADS).
Results And Limitations:
The model achieved an AUC of 0.841 (95% CI 0.76-0.91), with 100% sensitivity and 66.7% specificity for csPCa in the mpMRI cohort at the optimal 17% risk threshold (65.5 points). It safely avoided 49.4% of biopsies without missing any csPCa cases. Simpler strategies using PHI or PIRADS alone showed lower efficiency, particularly in balancing sensitivity and biopsy reduction. As an additional analysis, the PHI-mpMRI nomogram by Siddiqui et al. (2023) was externally validated in our cohort, confirming robust diagnostic accuracy (AUC 0.89, 95% CI 0.82-0.95). Limitations include the modest size of the mpMRI cohort and the historical nature of recruitment (2014-2018), although PHI and mpMRI remain standard in contemporary practice.
Conclusions:
This model accurately predicts csPCa and outperforms individual tools such as PHI or PIRADS alone. Its application may improve diagnostic efficiency and reduce unnecessary procedures.
Patient Summary:
A model combining a blood test (PHI) and MRI can help avoid unnecessary prostate biopsies while reliably detecting aggressive cancers.


