Related Experiment Video
Updated: May 1, 2026


Vessel-sparing Excision and Primary Anastomosis
Published on: January 7, 2019
Surgical and Functional Outcomes after Perineal Approach for Repair of Vesico-Urethral Anastomotic Stenosis Following
Sandra San Cayetano Talegón1,2, Felix Campos-Juanatey1,3,4, Paola Calleja Hermosa1,3
1Department of Urology, Marqués de Valdecilla University Hospital, 39008 Santander, Spain.

Background:
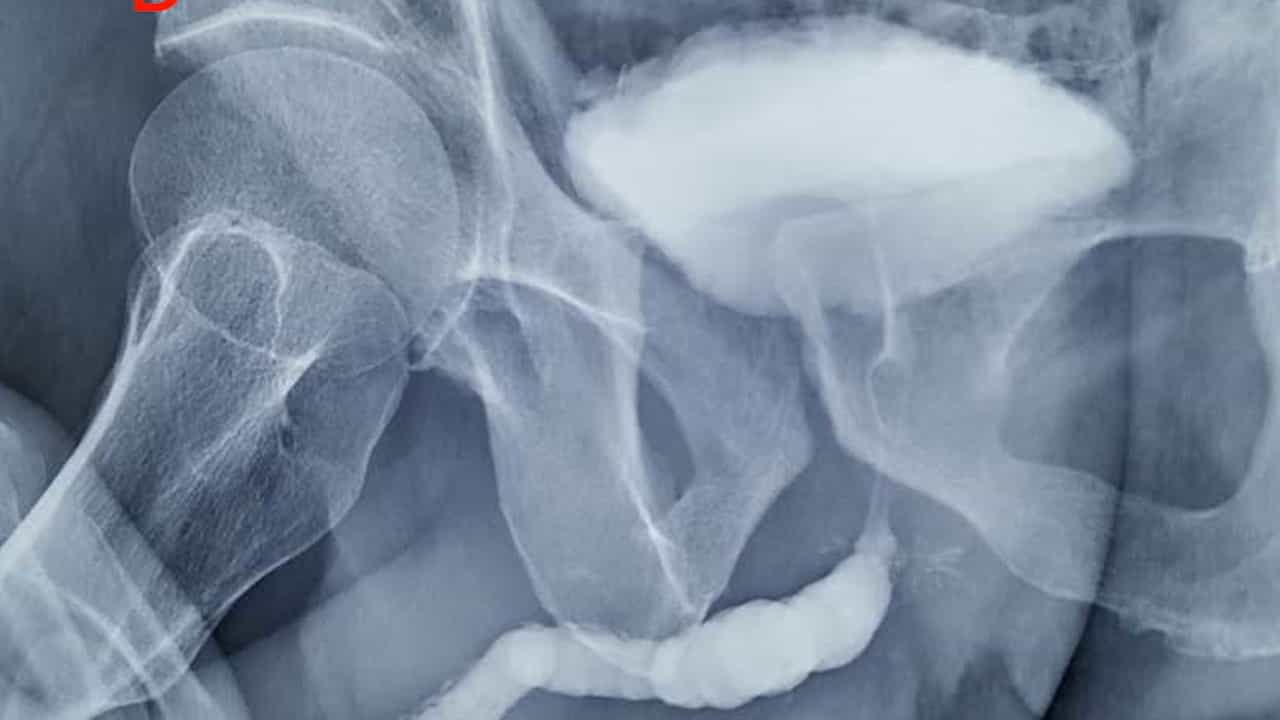
Vesicourethral anastomotic stenosis (VUAS) is a rare but complex complication following radical prostatectomy (RP), with an incidence ranging from 0.5% to 33% depending on surgical approach, surgeon experience and prior radiotherapy. Risk factors include intraoperative bleeding, urinary leakage, infection and adjuvant treatments. Despite advances in minimally invasive and robotic surgery, VUAS remains a significant cause of morbidity, often compromising urinary function and quality of life. Our objective is to evaluate the surgical and functional outcomes of perineal vesicourethral re-anastomosis in patients with recurrent VUAS after radical prostatectomy.
Methods:
We retrospectively reviewed 12 patients with recurrent VUAS treated between 2017 and 2024 by a single surgeon, with a minimum follow-up period of 6 months. All had at least one failed endoscopic treatment and preoperative incontinence. Anatomic success was assessed by urethrogram or urethroscopy. Descriptive analysis was conducted on demographic, surgical and outcome data.
Results:
The mean patient age was 71 years, with a median interval of 42-4 months (interquartile range (IQR) 9.5-86.1) from RP to stenosis diagnosis. Minor postoperative complications (Clavien I-II) occurred in three patients. Anatomical success, defined as the atraumatic passage of a 16 Fr cystoscope and/or absence of radiological stenosis, was achieved in 83.3% of cases with a mean follow-up of 39.5 months (standard deviation (SD) 24.7). At follow-up, urinary incontinence persisted in the majority of patients, and seven underwent artificial urinary sphincter implantation with satisfactory functional outcomes. One patient developed a urosymphyseal fistula complicated with pubic osteitis, ultimately requiring cystectomy and pubectomy.
Conclusions:
Perineal vesicourethral re-anastomosis represents an effective salvage strategy for recurrent VUAS after RP, providing high rates of urethral patency. However, it carries a substantial risk of postoperative incontinence, frequently necessitating subsequent continence surgery. Management should be centralised in reconstructive referral centres to optimise anatomical and functional outcomes.