Related Experiment Video
Updated: Jan 9, 2026


Author Spotlight: Integrating Alveolar-Capillary Reserve Measurements in Exercise Adaptation and Therapeutic Strategies
Published on: February 2, 2024
Resting lung volume phenotypes in COPD: implications for exertional dyspnoea and exercise tolerance
Danilo C Berton1, Abed A Hijleh2, Fernanda O Silva1
1Unidade de Fisiologia Pulmonar, Hospital de Clínicas de Porto Alegre, Universidade Federal do Rio Grande do Sul, Porto Alegre, RS, Brazil.

Background:
Lung volumes and dyspnoea vary markedly at a given forced expiratory volume in 1 s in COPD. We aim to investigate whether hyperinflation (high total lung capacity (TLC)) adds value to simpler inspiratory capacity (IC) in predicting mechanical-ventilatory impairment and exertional dyspnoea in these patients.
Methods:
345 patients with mild to very severe COPD (190 men) underwent incremental cycling with measurements of dyspnoea (0-10 Borg) and operating lung volumes. Resting volumes by body plethysmography were compared with the 2021 z-score-based Global Lung Initiative standards. A novel artificial intelligence (AI)-based algorithm quantified the burden of mechanical-ventilatory constraints and dyspnoea as ventilation increased.
Results:
Four lung volume phenotypes were identified: 168 patients with preserved IC and TLC, 51 with preserved IC and high TLC (hyperinflation), 52 with low IC but no hyperinflation, and 74 with low IC and hyperinflation. Patients with low IC and/or hyperinflation showed worse air trapping and lower transfer factor (p<0.05). Hyperinflated patients at a given IC presented with worse sensory and functional outcomes; similarly, patients showing low IC at a given TLC were more symptomatic and impaired (p<0.05). The highest and lowest odds ratios (95% confidence interval) for "very severe" mechanical-ventilatory constraints and dyspnoea according to the AI algorithm were found in hyperinflated patients with low IC (5.2 (4.7-7.5)) and non-hyperinflated patients with preserved IC (0.99 (0.71-1.16)), respectively.
Conclusion:
By combining IC and TLC expressed as z-scores, clinicians can identify physiological phenotypes relevant to dynamic lung mechanical abnormalities on exertion, activity-related dyspnoea and exercise tolerance across the spectrum of COPD severity.
More Related Videos
 07:09
Assessment of Pulmonary Capillary Blood Volume, Membrane Diffusing Capacity, and Intrapulmonary Arteriovenous Anastomoses During Exercise
Published on: February 20, 2017
 07:10
Home-Based Prescribed Pulmonary Exercise in Patients with Stable Chronic Obstructive Pulmonary Disease
Published on: August 24, 2019
Related Concept Videos
 01:20
Chronic Obstructive Pulmonary Disease-I: Introduction
 01:27
Chronic Obstructive Pulmonary Disease-IV: Assessement and Diagnostic Studies
Medical History
 01:22
Chronic Obstructive Pulmonary Disease
Smoking is a primary risk factor for COPD, with over 80% of patients having a history of it. Patients typically experience progressive dyspnea or labored breathing, frequent coughing, and recurrent pulmonary infections. Many eventually succumb to respiratory failure, characterized by...
 01:15
Respiratory Volumes
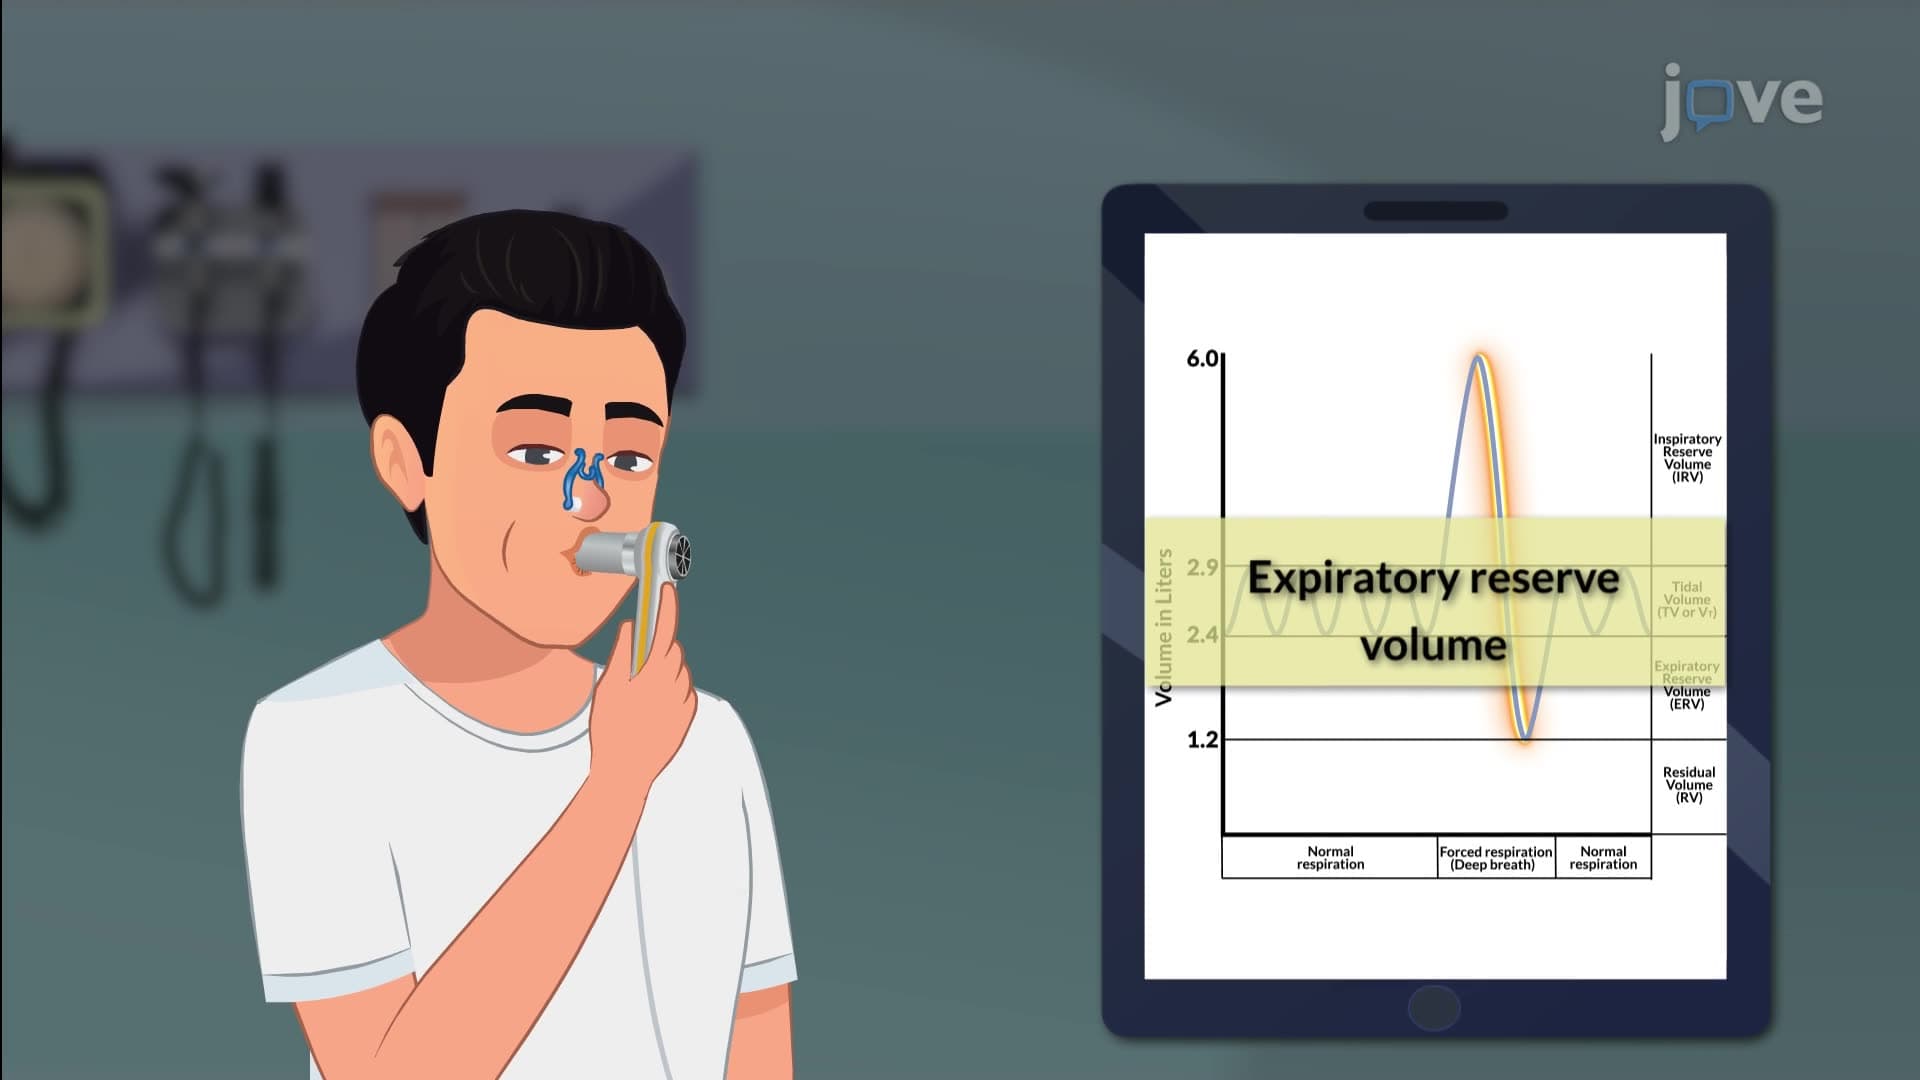
Tidal Volume (TV) Tidal volume (TV) is the air inhaled or exhaled in a...
 01:26
Respiratory Volumes and Capacities I
 01:47
Lung Capacity