Related Experiment Video
Updated: Jan 9, 2026
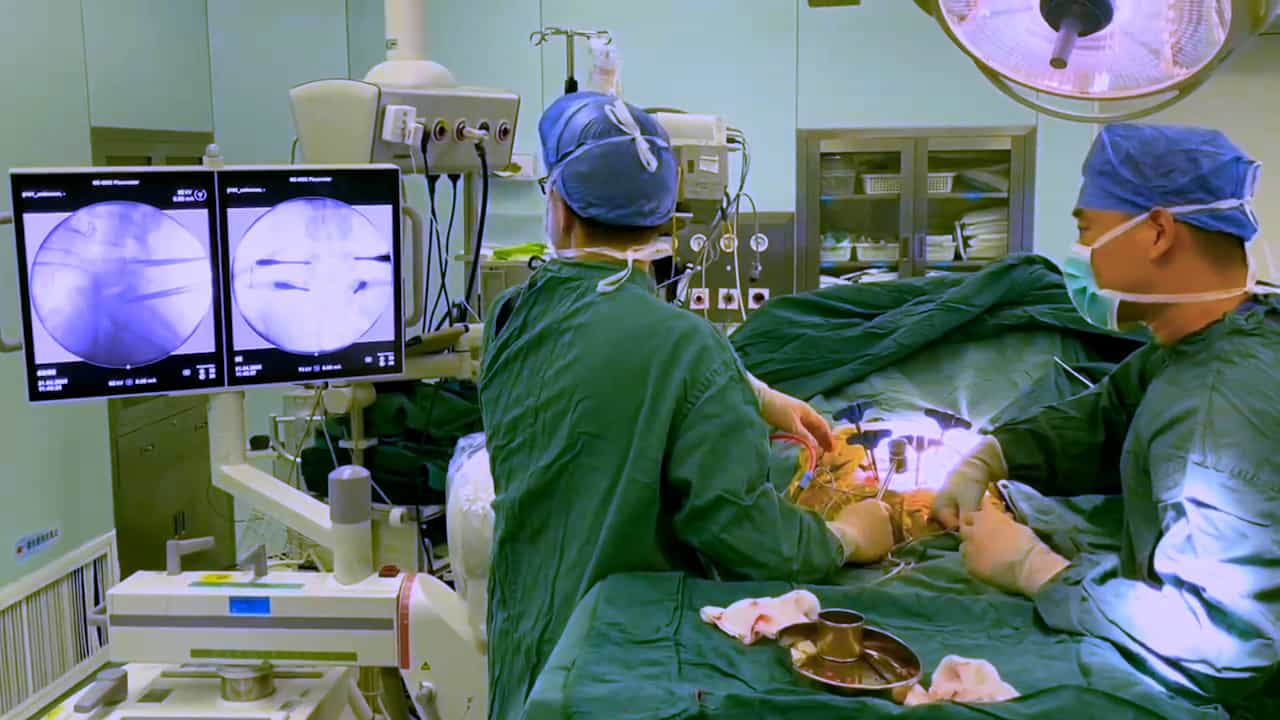

Novel Mini-open Transforaminal Lumbar Interbody Fusion
Published on: June 6, 2025
Volume and outcomes in posterior cervical fusion: Insights from a national inpatient analysis
Leonidas E Mastrokostas1,2, Paul G Mastrokostas1,2, Roee Ber3
1Department of Orthopaedic Surgery, SUNY Downstate Health Sciences University, Brooklyn, NY, USA.

Context:
Hospital procedural volume is often linked to outcomes and costs, but whether this relationship holds for posterior cervical fusion (PCF) remains unclear.
Aims:
The objective of this study was to evaluate whether hospital PCF volume is associated with complications, discharge disposition, and hospital costs.
Settings And Design:
Retrospective cross-sectional analysis of the National Inpatient Sample (NIS) from 2016 to 2022.
Subjects And Methods:
Elective PCF encounters were analyzed, with hospitals stratified by annual PCF volume (low, intermediate, high). Survey-weighted multivariable logistic regression estimated odds of cardiovascular complications, overall adverse events, and nonroutine discharge; linear regression assessed total costs and lengths of stay (LOS). Models adjusted for demographic, clinical, and hospital covariates.
Statistical Analysis Used:
Survey-weighted regression with odds ratios (ORs), coefficients, and 95% confidence intervals (CIs). Significance was set at P < 0.05.
Results:
We included 163,230 weighted elective PCF cases. Baseline characteristics differed across volume groups (P < 0.001) except for sex (P = 0.163). Compared with low-volume hospitals, high-volume hospitals had higher odds of cardiovascular complications (OR 1.87, 95% CI 1.70-2.06, P < 0.001), overall adverse events (OR 1.30, 95% CI 1.21-1.40, P < 0.001), and non-routine discharge (OR 1.09, 95% CI 1.02-1.16, P = 0.008). High-volume hospitals were also associated with higher total costs (coefficient: $4298; 95% CI $3468-$5128; P < 0.001), with no significant difference in LOS (P = 0.387).
Conclusions:
Hospital PCF volume is tied to complications, nonroutine discharges, and higher costs, challenging the volume-outcome paradigm and underscoring adjustment for patient complexity and case mix in benchmarking and allocation.