Related Experiment Video
Updated: Jul 1, 2026

Isolation of Human Lymphatic Endothelial Cells by Multi-parameter Fluorescence-activated Cell Sorting
Published on: May 1, 2015
Fluid overload-associated large B-cell lymphoma: two case report and review of literature
Liudi Chang1,2, Zhaobo Yang3, Cuicui Yang4
1School of Clinical Medicine, Shandong Second Medical University, Weifang, China.

Background:
Fluid overload-associated large B-cell lymphoma (FO-LBCL) is an exceptionally rare lymphoma characterized by predominant involvement of serous body cavities-such as the pleura, peritoneum, and pericardium-in the absence of a solid tumor mass. Its low incidence and nonspecific clinical presentation, which often includes symptoms like dyspnea due to effusion, contribute to diagnostic challenges in early stages. This study aims to address current gaps in the understanding of FO-LBCL by reporting two new cases and reviewing the clinical features, treatment regimens, and outcomes of 57 documented patients. Furthermore, through a detailed analysis of FO-LBCL characteristics, this work discusses relevant differential diagnoses and potential treatment strategies.
Methods:
A literature search of PubMed and Web of Science was performed using the following search queries: (1) "Fluid overload-associated large B-cell lymphoma" OR "FO-LBC"; (2) "Human herpesvirus 8-unrelated" AND "effusion lymphoma"; (3) "HHV8-unrelated" AND "effusion lymphoma".
Results:
This study included a total of 57 patients. Fluid accumulation most commonly affected the pleural cavity (84.2%), followed by the pericardial (31.6%) and peritoneal (21.1%) cavities. The predominant clinical manifestation was dyspnea (55.8%). Chemotherapy was the primary treatment modality (56.1%), with the R-CHOP regimen representing the most commonly administered protocol. CD20 expression was the most significant favorable prognostic factor (P = 6×10⁻⁷). Other factors associated with improved survival included the absence of CD138 expression (P = 0.0009), age ≥ 65 years (P = 0.0015), LDH ≤ 500 U/L (P = 0.0064), the presence of pleural effusion (P = 0.0099), and CD79a expression (P = 0.0411). Treatment with rituximabcontaining chemotherapy regimens was also a significant favorable factor (P = 0.0036).
Conclusions:
FO-LBCL often presents with dyspnea caused by fluid effusion. Routine laboratory tests typically show no significant abnormalities, making timely pathological examination essential for a definitive diagnosis. Clinicians should enhance their understanding of FO-LBCL characteristics to improve early diagnostic accuracy. It is crucial to select appropriate treatment strategies based on prognostic factors.

Related Concept Videos
 01:27
Disorders of Leukocytes
Leukopenia may result from bone marrow disorders, autoimmune diseases, and infectious diseases. For example, conditions such as multiple myeloma and aplastic anemia can impair the bone marrow's ability to produce adequate leukocytes. Similarly, autoimmune diseases like lupus and viral infections such as HIV can prompt the immune system...
 01:16
Lymphatic Vessels and Lymph Transport
This one-way system allows fluids, solutes, and even pathogens to enter but prevents their return to the intercellular spaces.
 01:18
Lymphoid Cells and Tissues
Lymphoid cells consist of various types of immune system cells. These include B and T lymphocytes, which are responsible for producing antibodies and killing infected cells, respectively. Dendritic cells act as messengers between the innate and adaptive...
 01:15
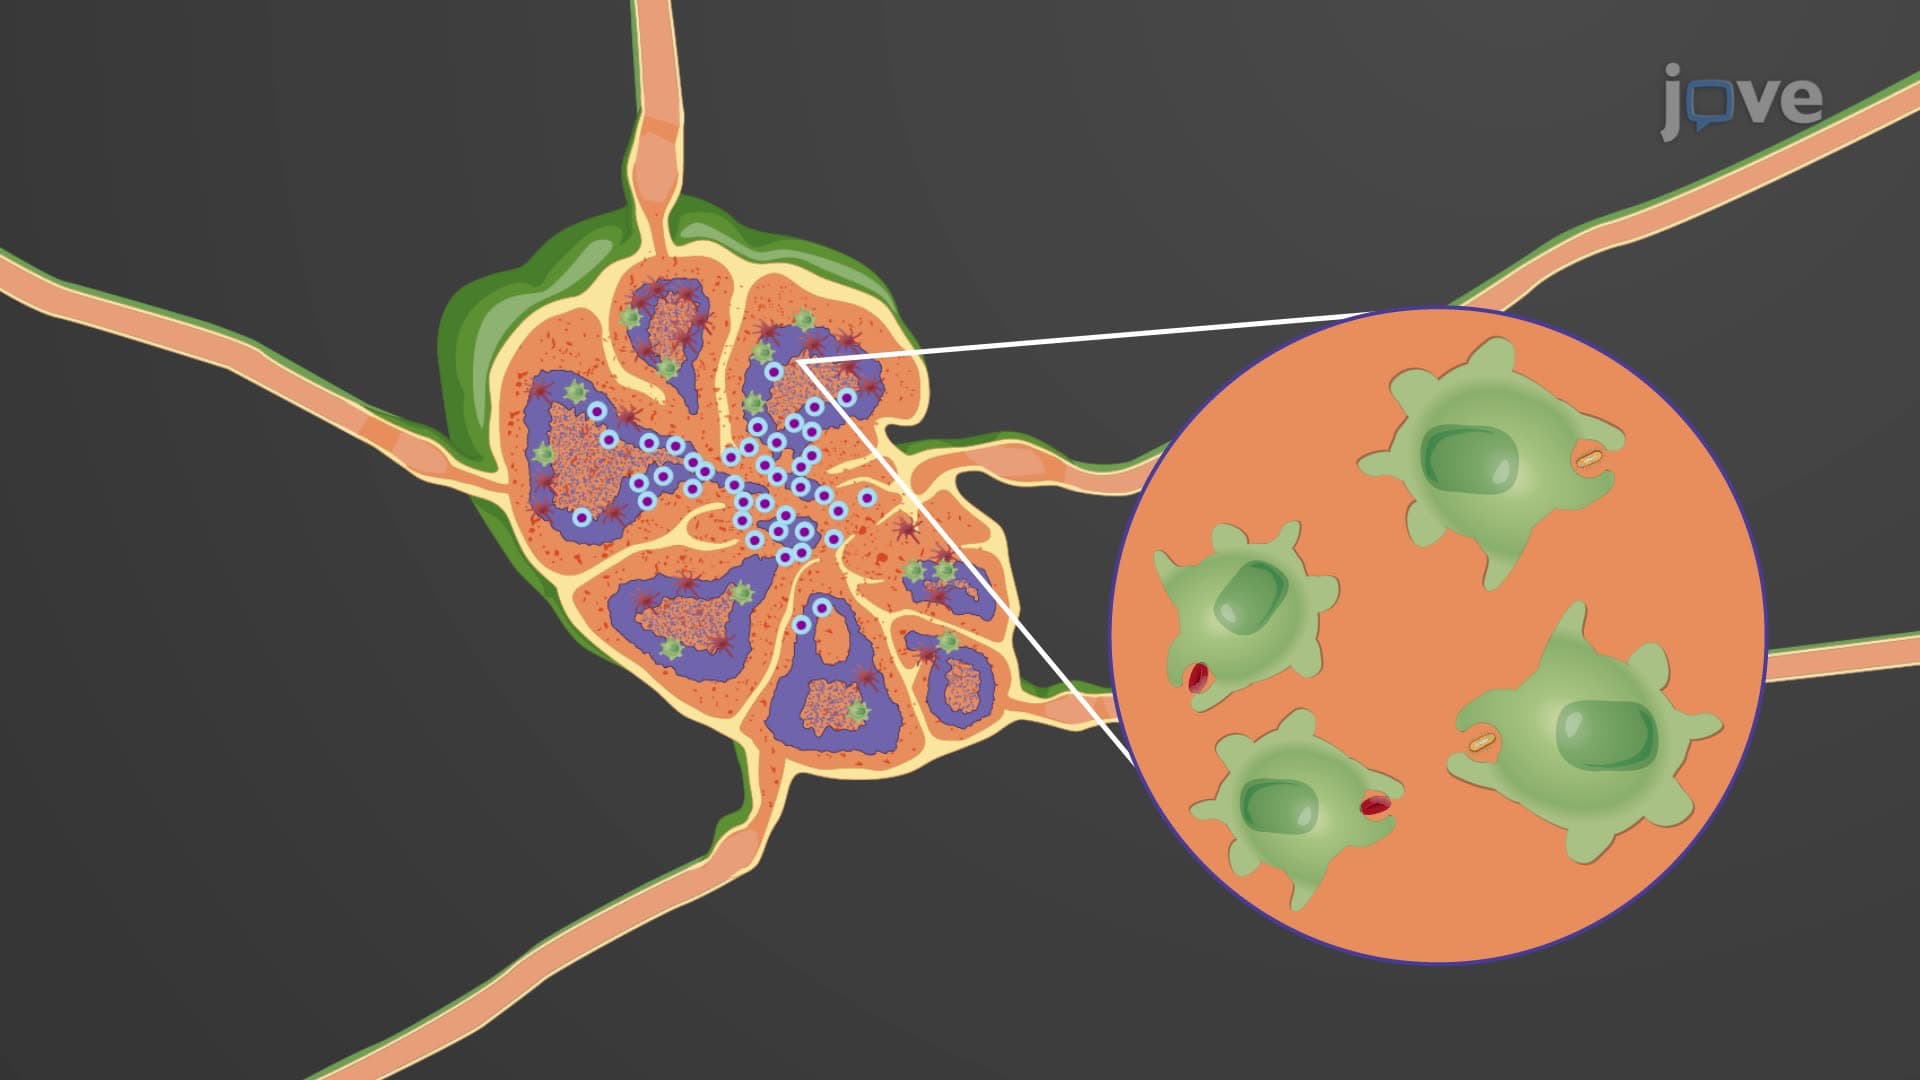
Secondary Lymphoid Organs
The spleen is a vital organ in the lymphatic system, nestled in the upper left side of the abdomen. It is composed of two primary regions: the red pulp and the white pulp, each having distinct functions. The red pulp performs a significant role in blood filtration. It efficiently purges the blood of old or damaged red blood cells and...