Related Experiment Video
Updated: Jan 8, 2026


Minimally Invasive Treatment for Thoracolumbar Burst Fracture Using Sagittal Alignment Screws and A Trauma Reduction Device
Published on: November 8, 2024
Saving Fusion Levels in Lenke 1/2 AR Curves: Can We Stop Short of the Last Substantially Touched Vertebra (LSTV)?
Michael W Brown1, Arun R Hariharan2, Tracey Bryan3
1Charles E. Schmidt College of Medicine, Florida Atlantic University, Boca Raton, FL.

Study Design:
Retrospective cohort from a multicenter registry.
Objective:
Characterize the variability of the last substantially touched vertebra (LSTV) in Lenke 1- and 2-AR curves and evaluate whether clinical or radiographic factors permit fusion short of the LSTV without increased adding-on risk.
Summary Of Background Data:
Lenke 1 and 2A curves with an R modifier based on L4 tilt in adolescent idiopathic scoliosis (AIS) are associated with a higher risk of adding-on after posterior spinal fusion (PSF). Fusion to the LSTV may reduce this risk but often requires extending into the distal lumbar spine, compromising motion. The safety of terminating fusion proximal to the LSTV in select patients, without increasing adding-on risk, remains uncertain.
Methods:
Patients with Lenke 1- or 2-AR curves undergoing PSF with minimum 2-year follow-up were identified. Radiographs were reviewed to determine LSTV level and assess for adding-on. Patients were stratified based on whether the lowest instrumented vertebra (LIV) was proximal to or at the level of/distal to the LSTV. Among those fused proximal, univariate and multivariate analyses were used to identify protective factors. Subgroup analyses were performed by LSTV level.
Results:
Of 324 patients, 144 (44.4%) were instrumented proximal to the LSTV. Adding-on occurred in 16.0% of all patients, more frequently in short fusions (21.5% vs. 11.7%, P=0.016). Multivariate analysis identified higher Risser (OR=1.62, P=0.006) and greater main thoracic correction (OR=1.09, P<0.001) as protective. Adding-on was rare (4.0%) when the LSTV was L4, even when fused short.
Conclusions:
In skeletally mature patients with adequate thoracic correction, fusion proximal to the LSTV in Lenke 1- and 2-AR curves may be performed safely. When the LSTV is L4, fusion to that level may be unnecessary, offering an opportunity for lumbar motion preservation without increased risk of adding-on.
Level Of Evidence:
IV.
Related Concept Videos
 01:20
Elevation of Intermediate Points on Vertical Curves
 01:16
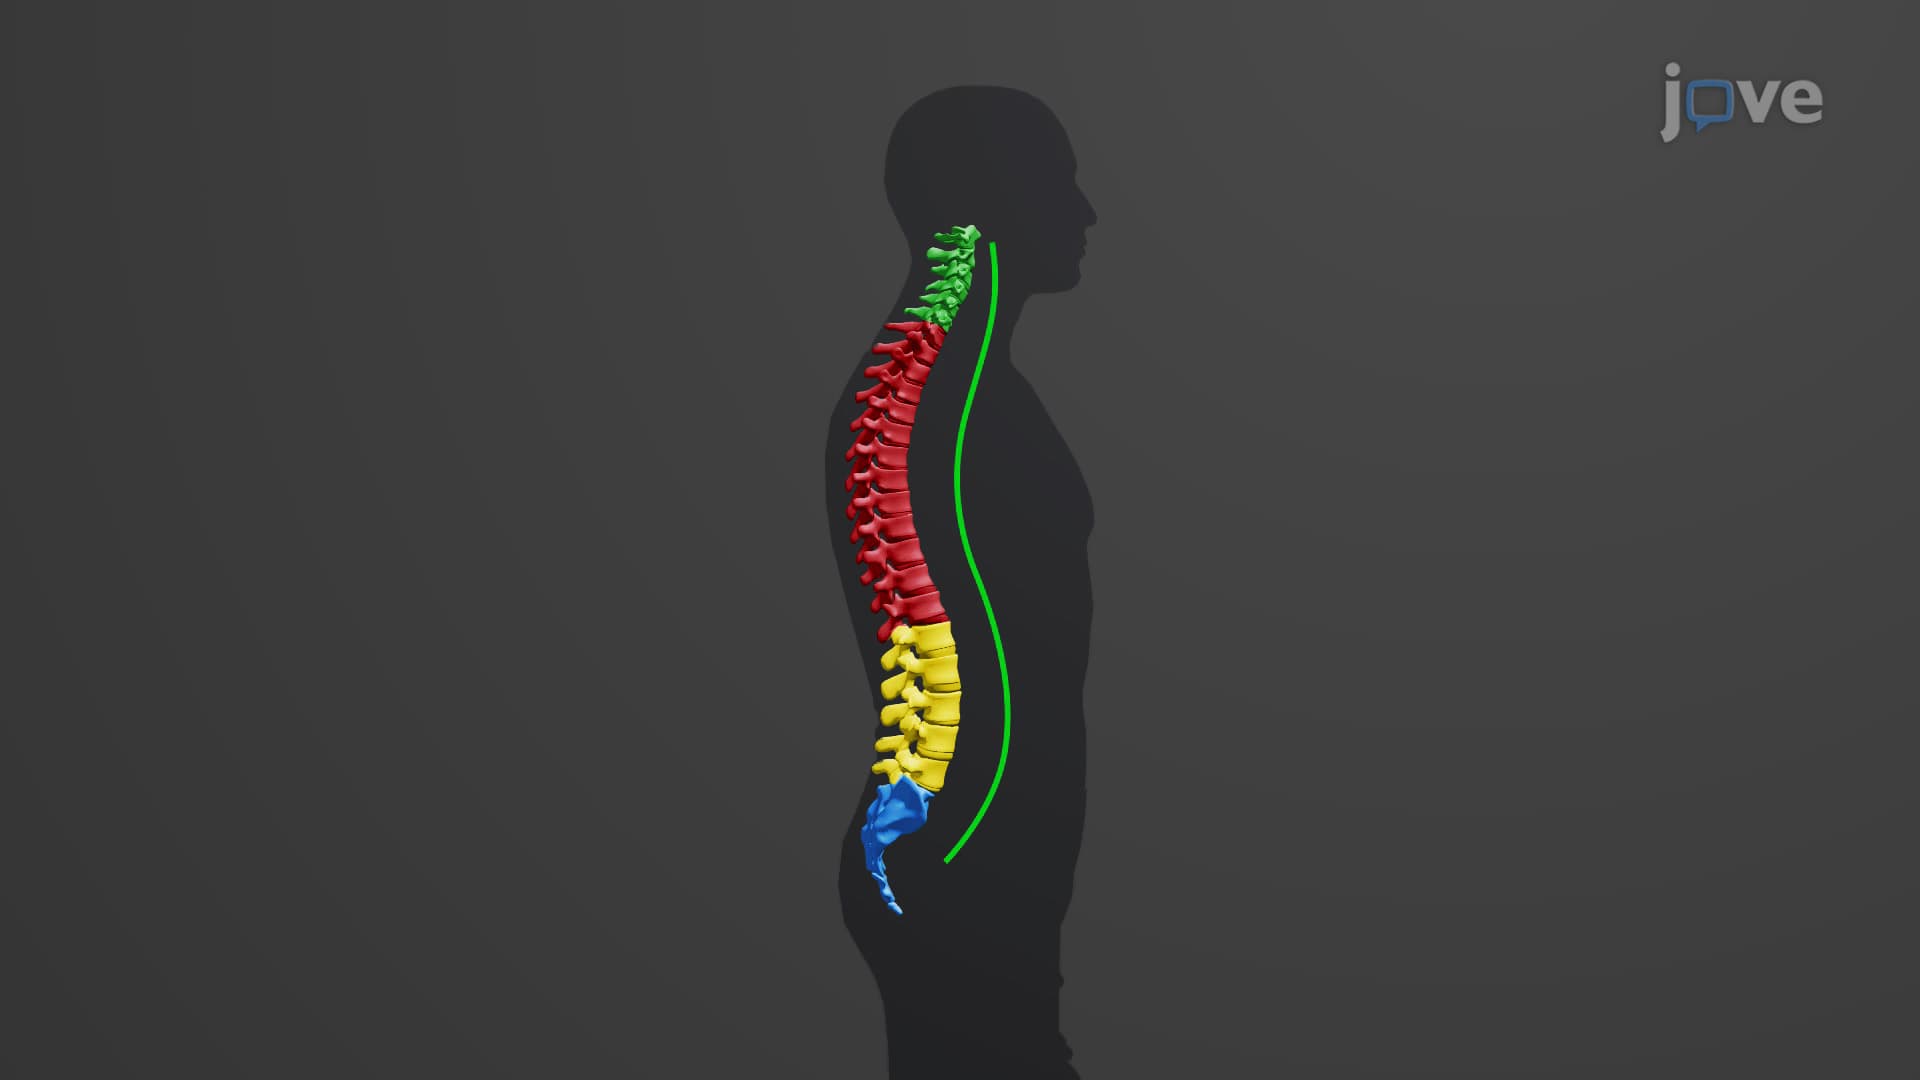
Vertebral Column: Regions and Curvature
Regions of the Vertebral Column
In an adult, the spine is subdivided into five regions: the cervical, the thoracic, the lumbar, the sacral, and the coccygeal region. The spine initially develops as a series of 33 vertebrae; after 20 years of age, the nine bones in the sacral region, five sacral, and four coccygeal bones fuse to form...
 01:30
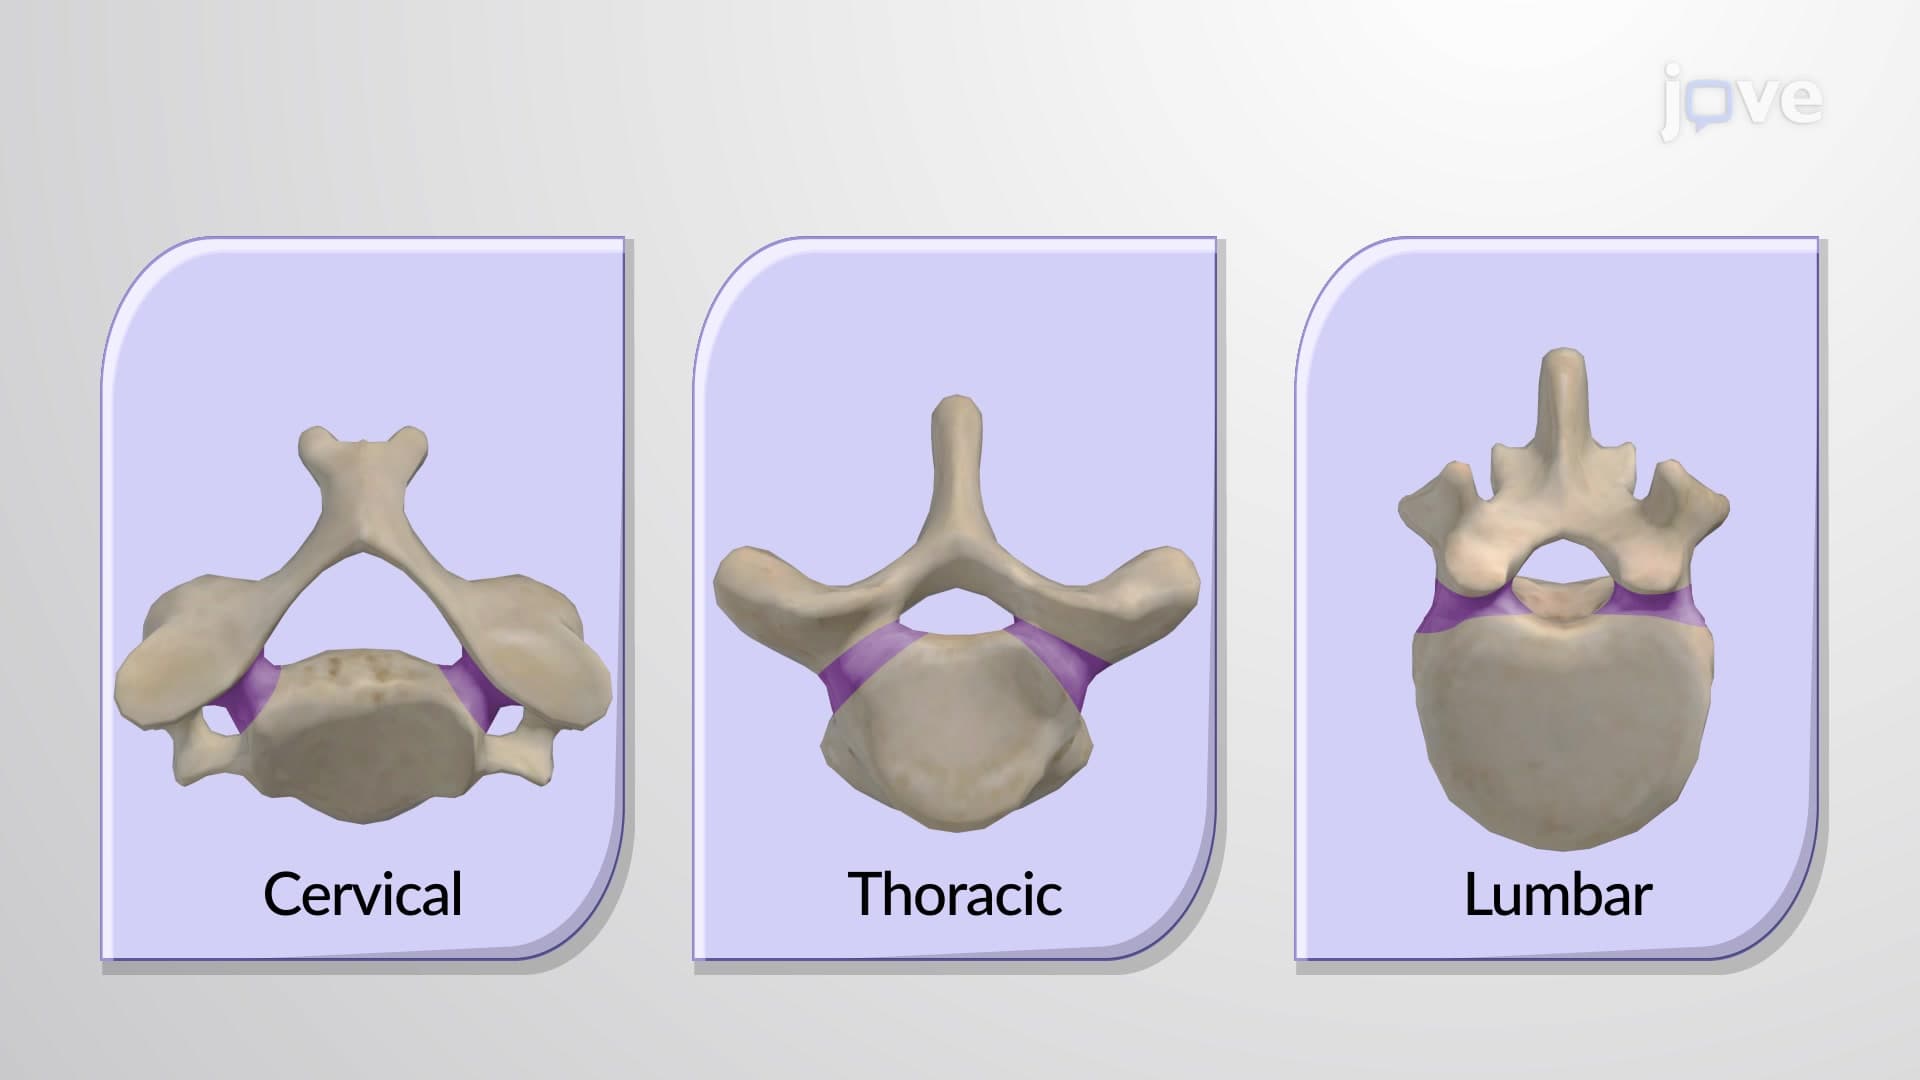
General Structure of a Vertebra
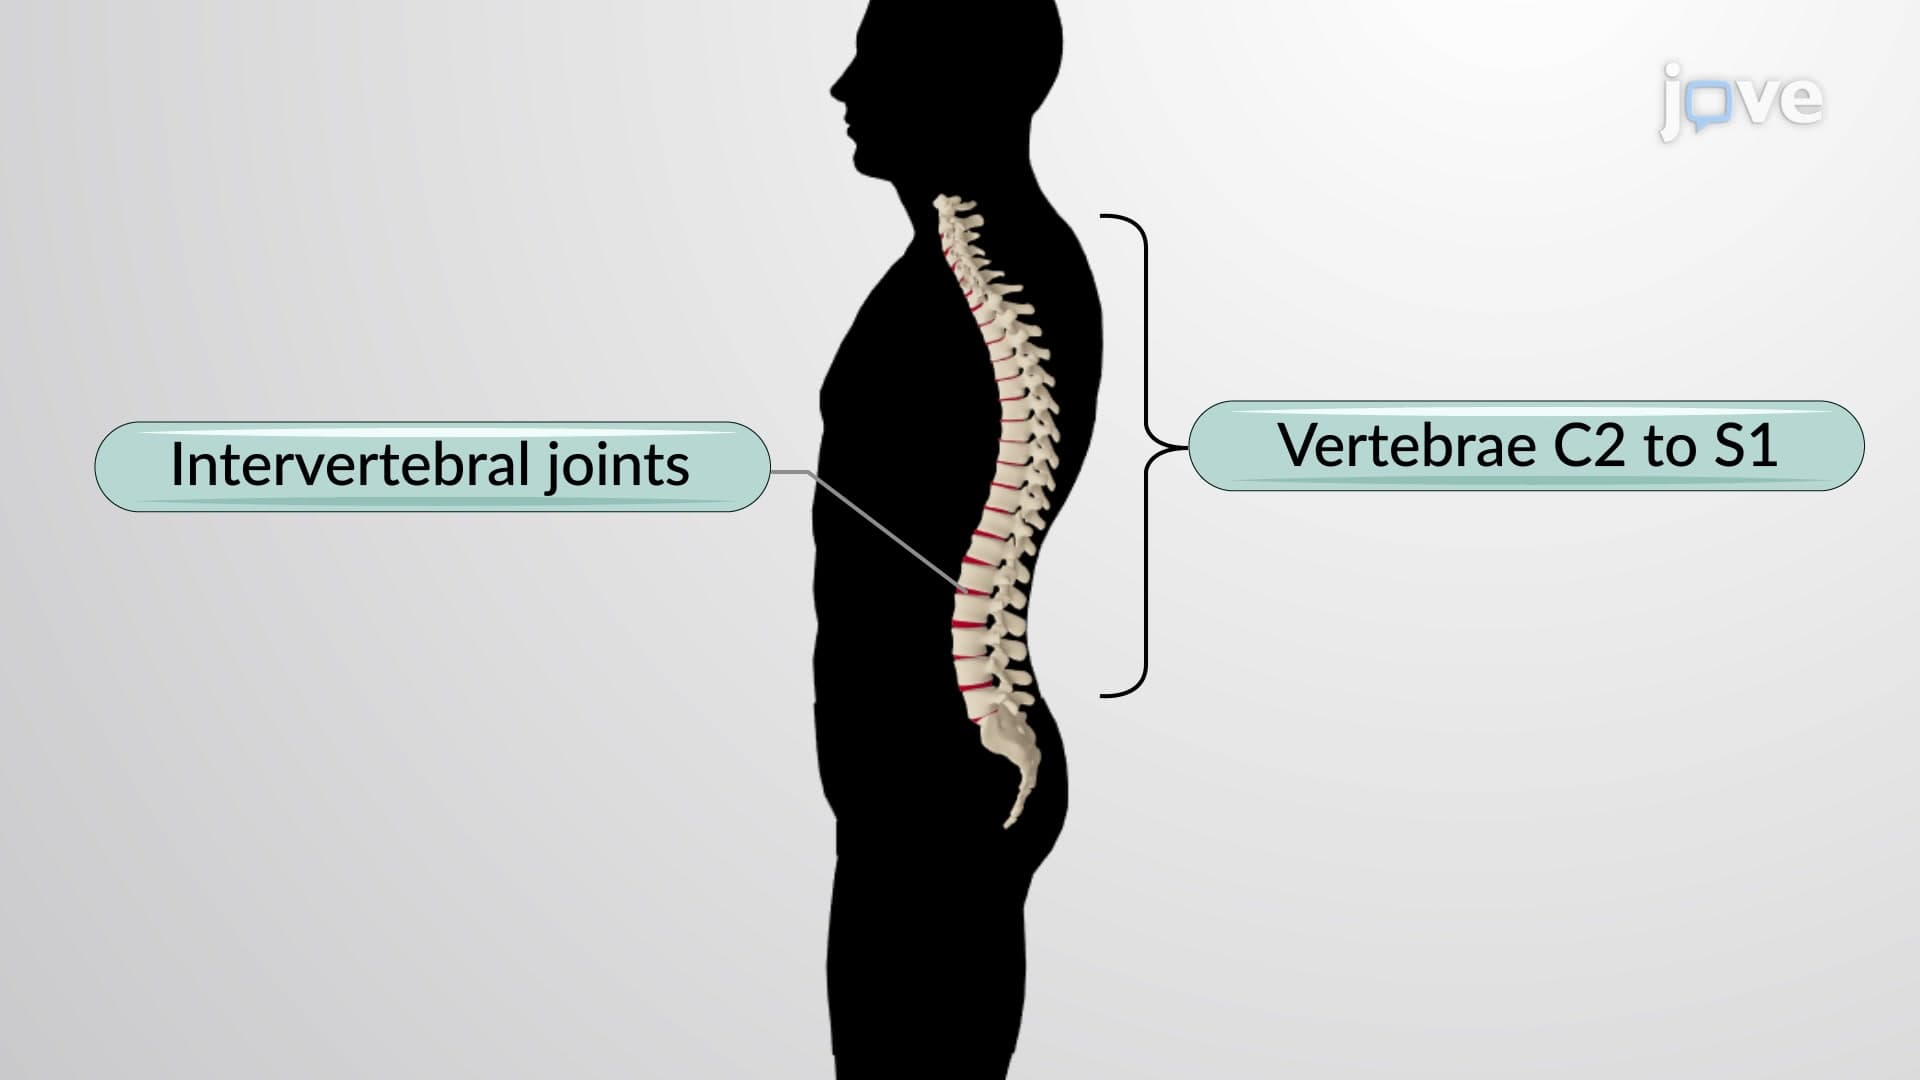 01:28
Articulations of the Vertebral Column
 01:11
Deformation of Member under Multiple Loadings
In the case of a member with a variable cross-section, the strain is not constant but depends on the position. The deformation of an...
 01:12
Differential Leveling