Related Experiment Video
Updated: Jan 8, 2026
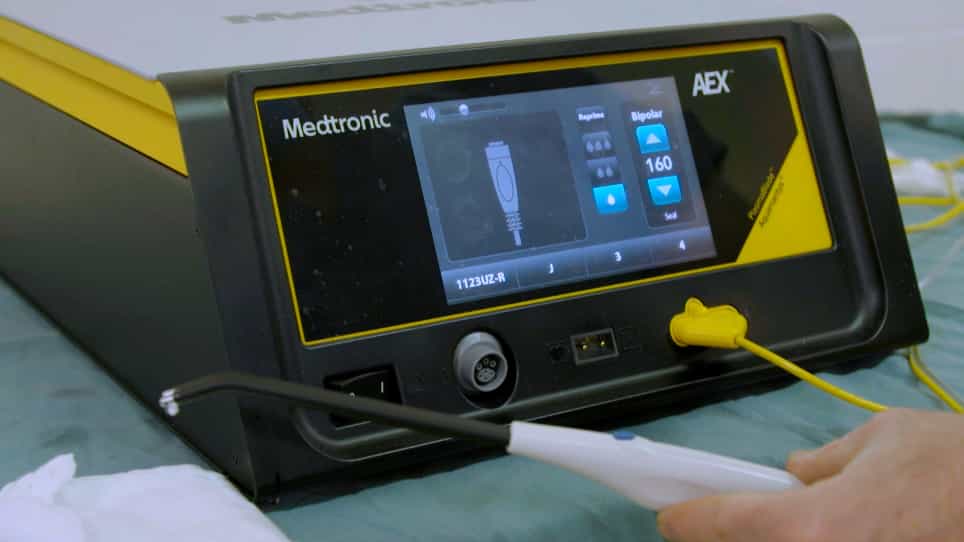

A Saline/Bipolar Radiofrequency Energy Device As an Adjunct for Hemostasis in Solid Organ Injury/Trauma
Published on: July 28, 2020
Western Trauma Association critical decisions in trauma: Penetrating thoracic injury
Manuel Lorenzo1, Raul Coimbra, Chasen A Croft
1From the Department of Surgery (M.L.), Methodist Dallas Medical Center, Dallas, Texas; Division of Trauma and Acute Care Surgery (R.C.), Surgeon-in-Chief Riverside University Health System Medical Center, Moreno Valley; Department of Surgery (R.C.), Loma Linda University School of Medicine, Loma Linda, California; Department of Surgery (C.A.C.), University of Florida College of Medicine, Gainesville, Florida; Department of Surgery (J.L.H.), University of Kansas Medical Center, Kansas City, Kansas; Department of Surgery (K.S.S.), Yale University School of Medicine, Bridgeport Hospital, Bridgeport, Connecticut; Department of Surgery (E.E.M.), University of Colorado, Denver, Colorado; Department of Surgery (M.A.S.), Uniformed Services University of the Health Sciences, Bethesda, Maryland; Department of Surgery (W.L.B.), Scripps Memorial Hospital, La Jolla, California; Department of Surgery (D.H.L.), University Hospital, Rutgers Health New Jersey Medical School, Newark, New Jersey; Department of Surgery (M.A.C.), The University of Tennessee Health Science Center, Memphis, Tennessee; Department of Surgery (R.K.-J.), Peacehealth Southwest Medical Center, Vancouver; Department of Surgery (J.P.K.), Madigan Medical Center, Fort Lewis, Washington; Department of Surgery (N.N.), University of Miami Miller School of Medicine, Miami, Florida; Department of Surgery (R.C.M.), University of Colorado, Denver, Colorado; Department of Surgery (N.K.), University of Arizona College of Medicine, Phoenix, Arizona; Medical College of Wisconsin (A.M.H.), Milwaukee, Wisconsin; Department of Surgery (R.T.), University of California/San Francisco, San Francisco, California; Department of Surgery (A.R.P.), Medical University of South Carolina, Charleston, South Carolina; Department of Surgery (G.A.M.), New York Grossman School of Medicine, New York University Langone Health, New York, New York; Department of Surgery (M.S.), St Michael's Hospital, Toronto, Ontario; Department of Surgery (T.R.K.), Mission Hospital, Asheville, North Carolina; Department of Surgery (A.J.K.), The University of Tennessee Health Science Center, Memphis, Tennessee; Department of Surgery (K.L.B.), Virginia Tech Carilion School of Medicine, Carilion Clinic, Roanoke, Virginia; Department of Surgery (J.L.S.), University of Pittsburg Medical Center, Pittsburg, Pennsylvania; Department of Surgery (A.M.), University of Vermont, Burlington, Vermont; and Department of Surgery (C.J.F., D.M.S.), University of Maryland School of Medicine, Baltimore, Maryland.

No abstract available in PubMed .
More Related Videos
 15:11
Surgical Fixation of Sternal Fractures: Preoperative Planning and a Safe Surgical Technique Using Locked Titanium Plates and Depth Limited Drilling
Published on: January 5, 2015
 09:37
Complete and Partial Aortic Occlusion for the Treatment of Hemorrhagic Shock in Swine
Published on: August 24, 2018
Related Concept Videos
 01:26
Flail Chest-II
Assessment:
1. Clinical Evaluation:
History:
 01:27
Pneumothorax-II
Clinical Manifestations:
 01:22
Cardiopulmonary Resuscitation II: ACLS Airway Management
 01:26
Pneumothorax-I
Pneumothorax can be even further classified as spontaneous, traumatic, and tension pneumothorax.
 01:29
Pulmonary Embolism II: Diagnostic Studies and Interprofessional Care
 01:28
Esophageal Perforation-II: Clinical Manifestations and Management
Clinical Manifestations: