Related Experiment Video
Updated: Jan 7, 2026
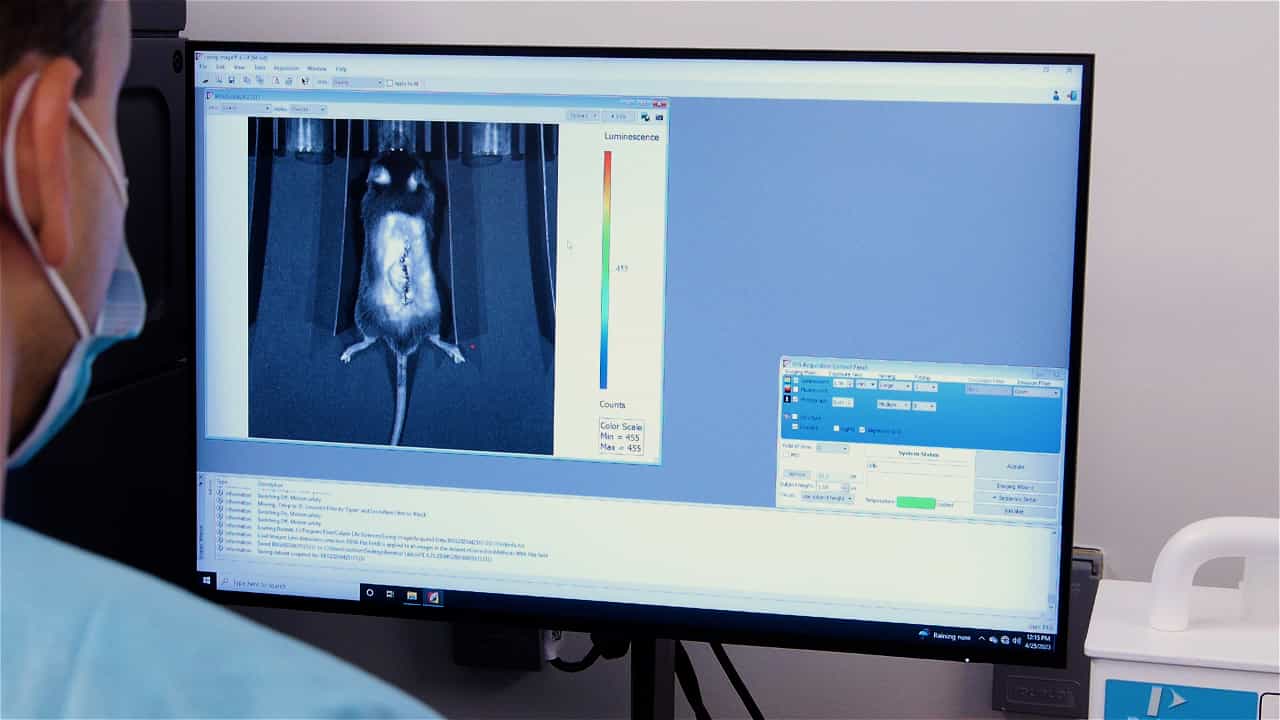

In Vivo Mouse Model of Spinal Implant Infection
Published on: June 23, 2020
Risk factors for periosteal fluid collection and surgical site infection based on cranioplasty material: Analysis of
Chung Mo Koo1, In-Ho Jung2, Sang Koo Lee2
1Department of Pediatric Neurology, Yongin Severance Hospital, Yonsei University College of Medicine, Yongin, Republic of Korea.

Objective:
This study aimed to clarify how the choice of cranioplasty material influences the risk of postoperative periosteal fluid collection (PFC) and surgical site infection (SSI) through large-scale analysis.
Methods:
A retrospective review was conducted on 434 patients who underwent cranioplasty over a ten-year period. Patients were grouped by implant material: autologous bone (n = 339), polyetheretherketone (PEEK; n = 39), polymethylmethacrylate (PMMA; n = 31), and titanium (n = 25). Multivariable logistic regression identified risk factors for PFC and SSI.
Results:
PFC occurred in 22.1 % of cases overall, but was significantly more frequent with PEEK (56.4 %) and PMMA (51.6 %) than with autologous bone (16.8 %) and titanium (4.0 %) (p < 0.001). PEEK use increased the risk of PFC by 6.47-fold compared to autologous bone (OR: 6.47, p < 0.001), while PMMA also showed a significant risk (OR: 3.78, p < 0.001). Shunt operation (OR: 4.56, p = 0.001) and traumatic brain injury (OR: 3.28; p < 0.001) were further independent predictors. SSI occurred in 9.0 % overall, with no statistically significant difference between materials after multivariate adjustment (p = 0.915), but PFC was the strongest independent risk factor for SSI (OR: 10.93, p < 0.001).
Conclusion:
Selection of cranioplasty material significantly affects the risk of PFC, which is strongly associated with subsequent SSI. PEEK and PMMA implants substantially increase PFC compared to autologous bone and titanium, while titanium demonstrates the lowest risk. These findings suggest that, in addition to patient-specific considerations, material properties and their impact on tissue integration must be central to clinical decision-making in cranioplasty.


