Related Experiment Video
Updated: Jan 7, 2026

Multiplex Therapeutic Drug Monitoring by Isotope-dilution HPLC-MS/MS of Antibiotics in Critical Illnesses
Published on: August 30, 2018
Discharge Delays and Costs Associated With Outpatient Parenteral Antimicrobial Therapy for Multidrug-Resistant
Stormmy R Boettcher1, Rachel M Kenney1, Nathan A Everson1
1Department of Pharmacy, Henry Ford Hospital, Detroit, Michigan, USA.

Background:
Outpatient parenteral antimicrobial therapy (OPAT) coordination is challenging in multidrug-resistant organism (MDRO)-infected patients. The study purpose was to describe barriers and medication costs associated with OPAT utilizing therapies for MDRO.
Methods:
This was an institutional review board-approved, retrospective cohort of hospitalized, MDRO-infected adults medically stable for discharge (MSDC) with an intended OPAT for cefiderocol, ceftazidime/avibactam, ceftolozane/tazobactam, eravacycline, meropenem/vaborbactam, or tigecycline from 1 January 2017 through 31 March 2025. Cohorts included patients who received an intended or modified OPAT regimen, defined as transition to alternative intravenous (IV)/oral therapy, in-hospital completion of IV therapy, or in-hospital death. Secondary outcomes included post-MSDC medication costs, length of stay (LOS), and oral-switch therapy opportunities.
Results:
One hundred-twenty patients were included; 29% received a modified OPAT regimen. β-lactams were the most intended OPAT regimen (67%). Patients with a modified OPAT regimen had higher median (interquartile range [IQR]) medication costs ($4828 [$1209-$18 066] vs $1975 [$494-$4872], P < .001), more frequently experienced discharge delays ≥1 day (89% vs 66%, P = .011) and discharge referral disposition changes (40% vs 16%, P = .006), and had a prolonged median (IQR) LOS (20 [14-46] vs 13 [7-27] days, P = .023), compared to those who received an intended OPAT regimen. Oral-switch therapy opportunities were identified in 40% of patients. After adjusting for Medicaid, referral disposition changes (adjusted odds ratio [aOR], 3.46 [95% confidence interval {CI}, 1.21-9.89) and initial β-lactam therapy (aOR, 4.08 [95% CI, 1.55-10.79]) were associated with an increased odds of receiving a modified OPAT regimen.
Conclusions:
Modified OPAT regimens are common and associated with increased costs, prolonged LOS, and discharge delays in MDRO-infected patients. These findings support the use of oral-switch therapy and improved care coordination.
Insights
Coordinating outpatient parenteral antimicrobial therapy (OPAT) for multidrug-resistant organism (MDRO) infections presents challenges. Modified OPAT regimens increase costs and prolong hospital stays, highlighting the need for oral-switch therapies.
Area of Science:
- Infectious Diseases
- Antimicrobial Stewardship
- Health Economics
Background:
- Outpatient parenteral antimicrobial therapy (OPAT) coordination is complex for patients with multidrug-resistant organism (MDRO) infections.
- Understanding barriers and costs is crucial for optimizing OPAT for MDROs.
Purpose of the Study:
- To describe the barriers and medication costs associated with OPAT for MDRO-infected patients.
- To identify factors influencing the modification of OPAT regimens.
Main Methods:
- Retrospective cohort study of hospitalized MDRO-infected adults medically stable for discharge (MSDC).
- Included patients receiving cefiderocol, ceftazidime/avibactam, ceftolozane/tazobactam, eravacycline, meropenem/vaborbactam, or tigecycline for OPAT.
- Analyzed medication costs, length of stay (LOS), discharge delays, and oral-switch therapy opportunities.
Main Results:
- 29% of patients received a modified OPAT regimen.
- Modified OPAT regimens were associated with significantly higher medication costs ($4828 vs $1975) and prolonged LOS (20 vs 13 days).
- Discharge delays (89% vs 66%) and referral disposition changes (40% vs 16%) were more frequent in modified OPAT groups.
Conclusions:
- Modified OPAT regimens are common in MDRO-infected patients and linked to increased costs, prolonged LOS, and discharge delays.
- Findings support the implementation of oral-switch therapy and enhanced care coordination for OPAT.
- Referral disposition changes and initial beta-lactam therapy were associated with higher odds of modified OPAT.


Related Concept Videos
 01:24
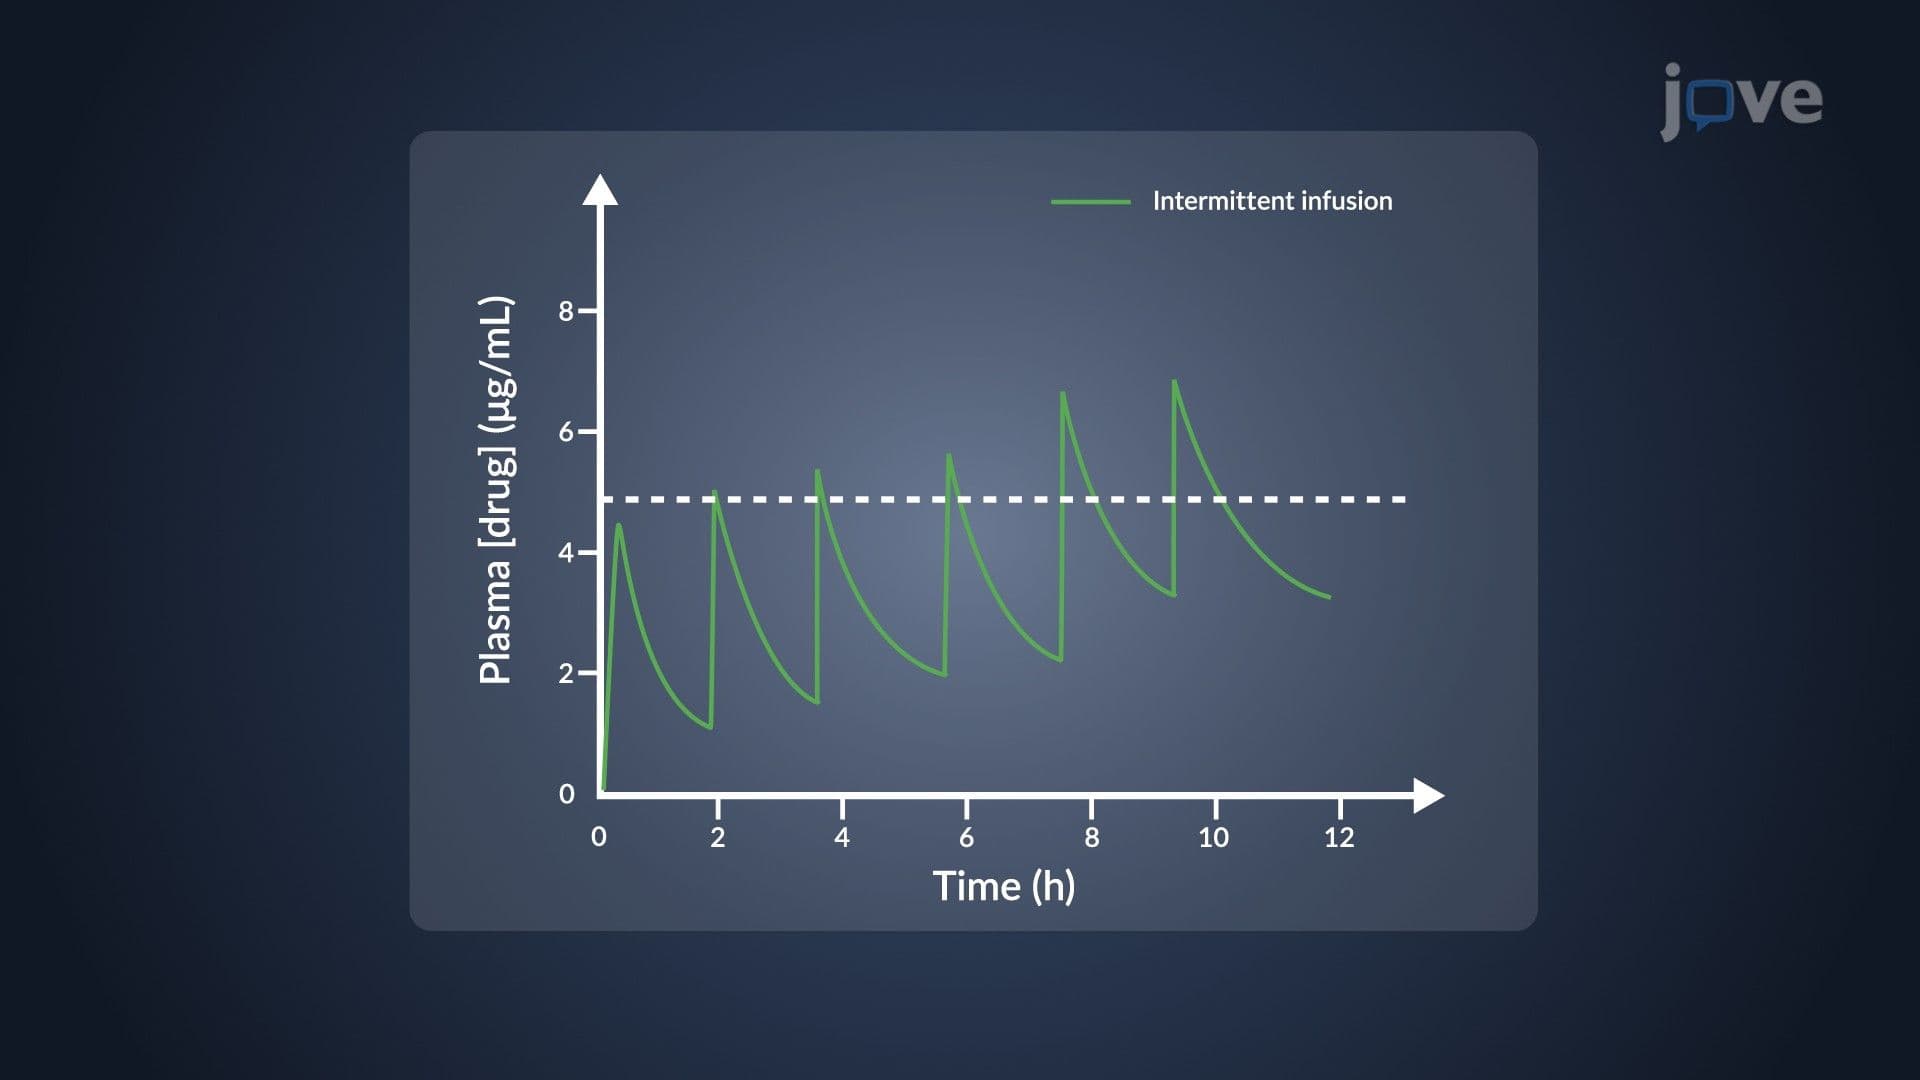
Drug Accumulation During Multiple Dosing: Intermittent IV Infusions
 01:26
Pharmacokinetics in Pediatric Patients: Drug Excretion
 01:28
Acute Pyelonephritis II: Diagnostic Studies and Management
 01:30
Urinary Tract Infection III: Diagnostic Studies and Interprofessional Care
 01:22
Pharmaceutical Alternatives: Stability-Related Therapeutic Nonequivalence
 01:25
Peritoneal Dialysis II: Peritoneal Dialysis Systems and Complications