Related Experiment Video
Updated: Jan 19, 2026

Author Spotlight: Advancing Pelvic Prolapse Treatment with a Non-Mesh Approach using Laparoscopic Pectopexy
Published on: October 25, 2024
Laparoscopic Management of Retained IUD, Isthmocele, and Cervical Stenosis With Concurrent Transabdominal Cerclage in
Maria C Alzamora Schmatz1, Gabrielle Mintz2, Liron Bar-El3
1Department of Minimally Invasive Gynecologic Surgery, Cleveland Clinic, Cleveland, Ohio (Drs Schmatz, Billow).

Objective:
To show a minimally invasive surgical approach for managing a retained intrauterine device (IUD) in a patient with severe cervical stenosis and a cesarean scar defect.
Setting:
Tertiary care center with expertise in complex gynecologic surgery.
Participants:
A 33-year-old G1P1001 with a history of cesarean delivery. She had a prior LEEP and IUD insertion, followed by cold-knife conization where IUD strings were transected. She presented with pelvic pain, irregular bleeding, and cervical stenosis. She underwent multiple failed IUD removal attempts complicated by uterine and rectovaginal septum perforations. Imaging revealed an isthmocele with minimal residual myometrium and cervical shortening.
Intervention:
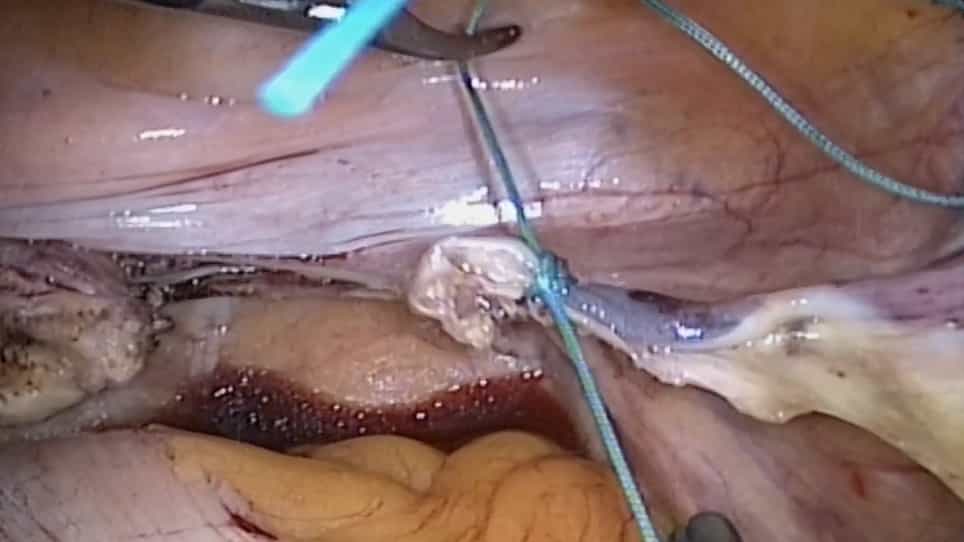
The patient underwent laparoscopic transuterine IUD removal, transuterine cervical dilation with intrauterine catheter placement to maintain cervical patency, isthmocele repair, and transabdominal cerclage. A transabdominal approach was selected over transvaginal cerclage or expectant management because of severe cervical distortion from previous excisional procedures and cervical shortening. A multidisciplinary team guided preoperative evaluation and counseling. Discussions included reproductive implications, potential improvement in symptoms and fertility optimization following isthmocele repair, the need for cesarean delivery after transabdominal cerclage, and limited evidence supporting cerclage in patients without prior preterm birth [1]. Key operative steps included lysing bladder adhesions, using the isthmocele as the uterine entry point for IUD removal, dilating the cervix through the uterus and placing an intrauterine catheter, repairing the isthmocele in two layers [2,3], and placing the cerclage. At her two-week postoperative visit, the catheter was removed, and office hysteroscopy was performed without complication or need for dilation.
Conclusion:
This video emphasizes the importance of patient-centered care and shared decision-making in managing complex reproductive surgical cases. It highlights multidisciplinary collaboration in guiding evidence-informed yet individualized care, aligning with fertility preservation goals. The surgical approach shows how minimally invasive techniques can be adapted to address multiple pathologies simultaneously, minimizing risk and optimizing reproductive potential. VIDEO ABSTRACT.
Related Concept Videos
 01:21
Inflammatory Bowel Disease V: Surgical Management
Here are some common surgical interventions for IBD:
 01:25
Urinary Tract Calculi VI: Surgical Management