Related Experiment Video
Updated: Jan 22, 2026


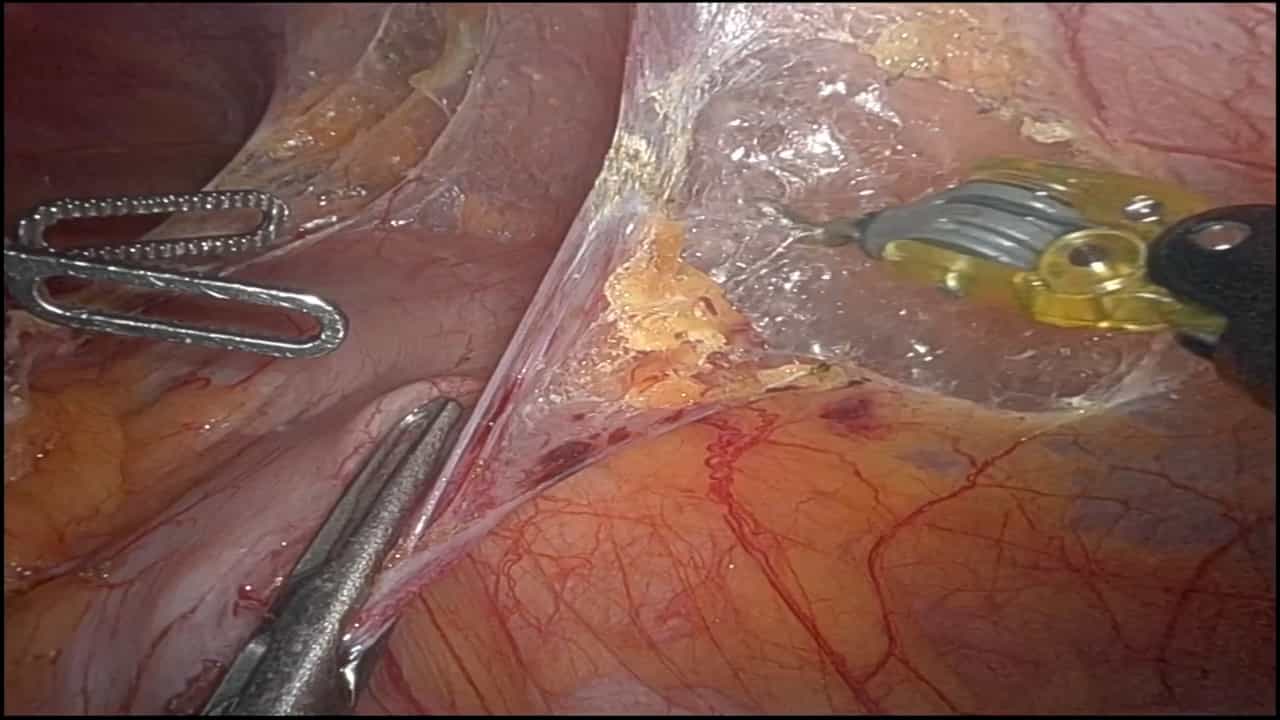
Laparoscopic Splenectomy with Pericardial Devascularization for Hypersplenism and Esophageal Variceal Hemorrhage Due to Portal Hypertension
Published on: November 15, 2024
Recurrent gastric variceal bleeding due to wandering spleen - complete resolution following laparoscopic splenectomy:
Byung Chul Jin1, Seung Young Seo, Hyeon Seok Baek
1Department of Internal Medicine, Division of Gastroenterology and Hepatology, Jeonbuk National University Medical School, Research Institute of Clinical Medicine of Jeonbuk National University-Biomedical Research Institute of Jeonbuk National University Hospital, Jeonju, South Korea.

Background:
Wandering spleen is a rare clinical entity caused by laxity or absence of splenic suspensory ligaments, predisposing to torsion of the vascular pedicle and subsequent vascular compromise. In unusual cases, splenic vein torsion may lead to left-sided (sinistral) portal hypertension with isolated gastric varices in the absence of cirrhosis. Although uncommon, variceal bleeding from this mechanism can be severe and requires timely recognition.
Case Presentation:
We report a 56-year-old man who presented with recurrent melena. Esophagogastroduodenoscopy revealed large fundic gastric varices without esophageal varices, and cross-sectional imaging identified a wandering spleen displaced into the pelvic cavity with venous congestion but no evidence of liver disease. Endoscopic cyanoacrylate injection provided temporary hemostasis; however, because of persistent vascular compromise and risk of rebleeding, laparoscopic splenectomy was performed. The postoperative course was uneventful, and follow-up computed tomography 5 months later confirmed complete resolution of perigastric varices and splenic venous congestion, demonstrating the reversibility of sinistral portal hypertension once splenic outflow obstruction is corrected.
Conclusion:
Wandering spleen with splenic vein torsion should be considered in patients presenting with isolated gastric varices and no signs of liver cirrhosis. While endoscopic therapy may achieve transient hemostasis, it does not correct the underlying hemodynamic disturbance. Splenectomy represents the definitive treatment, achieving durable hemodynamic correction and preventing further bleeding. Early recognition and surgical management are therefore essential for optimal outcomes in this rare but clinically significant condition.
Related Concept Videos
 01:24
Esophageal Varices-I: Introduction
 01:22
Bleeding in Fresh Concrete
Bleeding can cause several issues in the concrete structure. Sometimes, the rising water gets trapped beneath large aggregate...
 01:28
Esophageal Varices-II: Clinical Features and Management
In the initial assessment, a thorough review of the patient's medical history is vital to identify risk factors such as liver disease, alcohol...
 01:16
Gastric Motility
Peristaltic Waves and Chyme Formation
Upon food entry, the stomach initiates...
 01:16
Gastric Emptying
 01:26
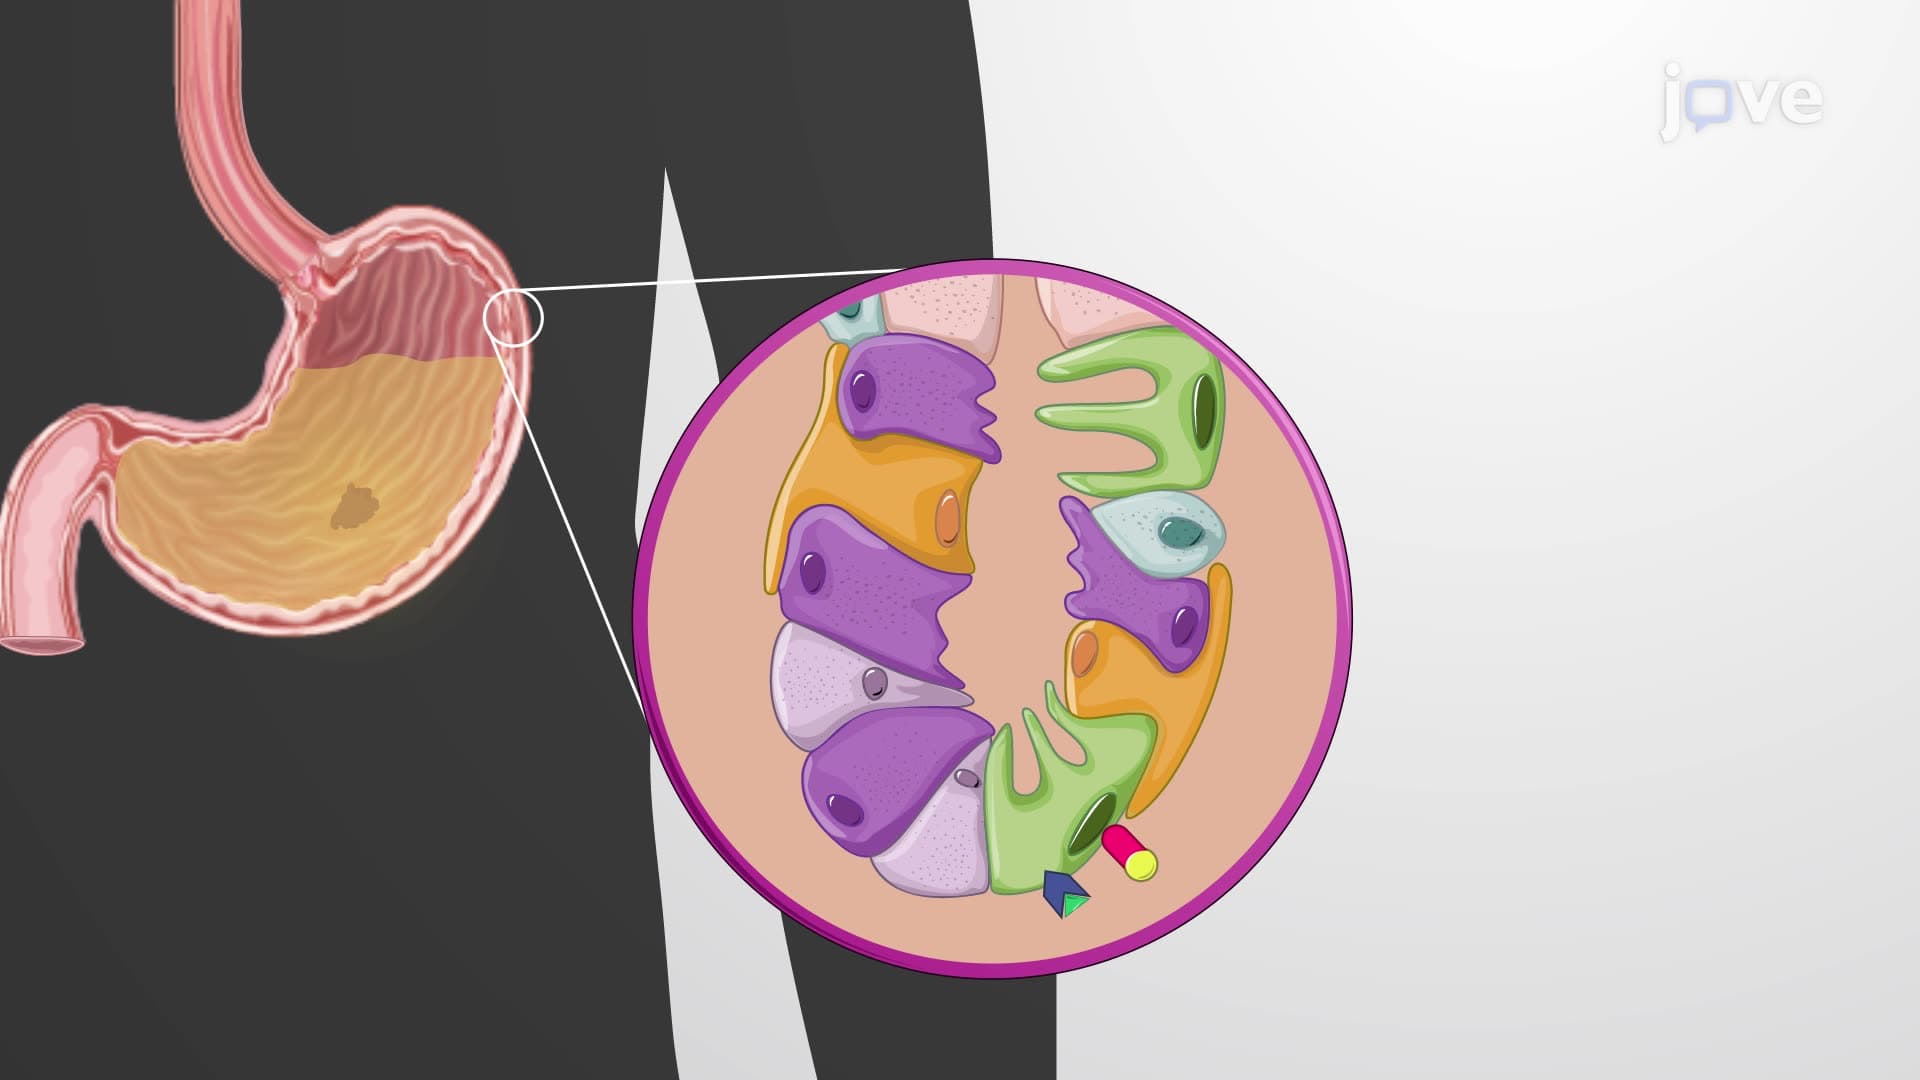
Gastric Phase of Digestion
When food enters the stomach, it stretches the stomach walls and activates stretch receptors. This triggers local reflexes of the enteric nervous system, mediated through the myenteric plexus. These...