Related Experiment Video
Updated: Sep 24, 2026


Treatment with Locking Intramedullary Nailing for Intertrochanteric Fracture of the Femur Utilizing a New Awl with a Distal Positioner
Published on: June 6, 2025
Cerclage for Fracture Reduction is Not Associated with Nonunion in Vancouver B or C Periprosthetic Femur Fractures
Christopher R Leland1,2,3,4,5, Alice W Wong1,3, Carla H Lehle1,3,6
1Harvard Medical School Orthopaedic Trauma Initiative, Boston, MA, USA.

Objectives:
To determine whether circumferential cerclage wiring for fracture reduction during lateral locked plating (LLP) of Vancouver B1 and C periprosthetic femur fractures is associated with nonunion.
Methods:
Design: Retrospective cohort study.
Setting:
Three academic Level I trauma centers.
Patient Selection Criteria:
Patients aged >50 years with a Vancouver B1 or C periprosthetic femur fracture (OTA/AO IV.3B1 and IV.3C) who underwent open reduction and internal fixation with a single LLP with or without circumferential cerclage for fracture reduction from 2010-2023 were included.
Outcome Measures And Comparisons:
The primary outcome was nonunion. The association between cerclage use and nonunion was assessed using multivariable logistic regression controlling for age, sex, ASA classification, and Vancouver classification. Secondary outcomes included deep infection and implant revision.
Results:
141 patients were included: 102 patients (72%; median age 78 years [IQR, 70-87]; 67% female) were treated with cerclage for fracture reduction and 39 patients (28%; median age 82 years [IQR, 70-89]; 85% female) were not. More patients treated with cerclage sustained a Vancouver B1 than Vancouver C fracture (n=78/102 [76%] vs. n=24/39 [24%]; P<0.001). Plates were longer (16 holes [IQR, 13-18] vs. 14 holes [IQR, 13-16]; P=0.02), stainless steel (n=91/102 [89%] vs. n=27/39 [69%]; P<0.01), and used in neutralization mode (n=96/102 [94%] vs. n=28/39 [72%]; P=0.001) in patients treated with cerclage. Nonunion occurred in 4 patients (4%) treated with cerclage and 4 patients (10%) without (P=0.30). Cerclage use was not associated with developing nonunion in multivariable regression (adjusted odds ratio, 0.3; 95% CI, 0.1-1.8; P=0.19). Infection occurred in 6 patients (6%) treated with cerclage and 0 patients (0%) without (P=0.28). Implant revision occurred in 8 patients (8%) treated with cerclage and 6 patients (15%) without (P=0.31).
Conclusions:
While baseline between-group differences were noted in Vancouver classification, the judicious use of circumferential cerclage wiring for fracture reduction and stabilization in Vancouver B and C periprosthetic femur fractures with stable implants was not associated with nonunion. No differences were noted in incidence of deep infection or implant revision following cerclage use in this population.
Level Of Evidence:
Therapeutic Level III.
More Related Videos
 04:19
Minimally Invasive Treatment for Thoracolumbar Burst Fracture Using Sagittal Alignment Screws and A Trauma Reduction Device
Published on: November 8, 2024
 11:21
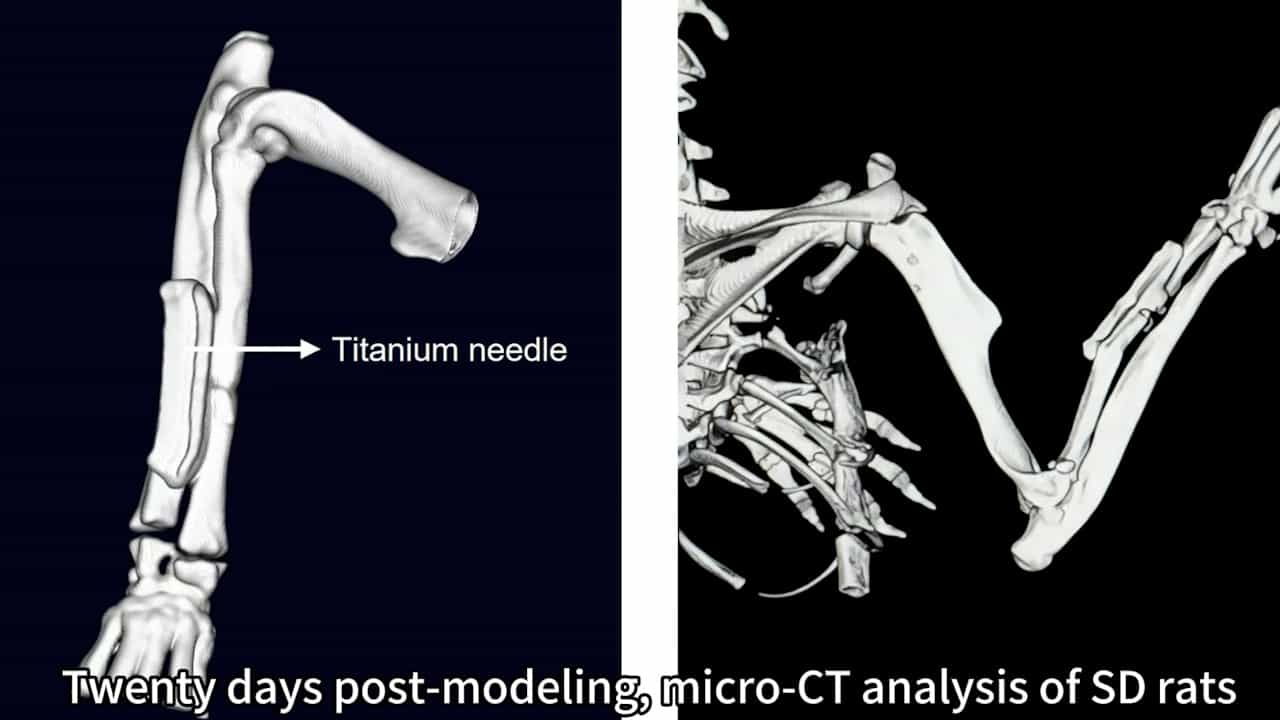
Development of a Novel Internal Fixation Model for Rat Radial Fractures: Fracture Healing Assessment and Dorsal Root Ganglion Isolation
Published on: March 13, 2026
