Related Experiment Video
Updated: Jan 22, 2026


Simultaneous Laryngopharyngeal and Conventional Esophageal pH Monitoring
Published on: December 14, 2020
Esophageal Acid Suppression Unmasks Latent Esophageal Acid-Symptom Phenotypes in GERD
Jerry D Gardner1, George Triadafilopoulos2,3
1Division of Gastroenterology and Hepatology, Stanford University School of Medicine, 420 Broadway Street, Pavilion D, 2Nd Floor, Redwood City, CA, 94063, USA. gardnerj@verizon.net.

Background:
Post-prandial esophageal acid exposure is a key determinant of symptom generation in gastroesophageal reflux disease. When esophageal acid exposure is high, high symptom intensity may mask individual variation in the relationship between acid exposure and perception.
Aims:
To compare how suppression of esophageal acid by omeprazole or by ranitidine combined with antacid influences post-meal heartburn severity and to determine whether active treatment unmasks distinct esophageal acid-symptom phenotypes.
Methods:
Two clinical studies used standardized meal tests in subjects with gastroesophageal reflux disease. In the omeprazole study, subjects were tested at baseline and after eight days of treatment. In the ranitidine plus antacid study, subjects were tested after placebo and active treatment in a randomized crossover design. Post-prandial esophageal acid concentration and heartburn intensity were measured for three hours (omeprazole) or four and one-half hours (ranitidine plus antacid). Total values were compared by receiver operating characteristic analysis and by quadrant classification of high and low acid-symptom relationships.
Results:
Both active treatments significantly reduced esophageal acid and heartburn intensity compared with control. Under control conditions, nearly all subjects exhibited high acid exposure with high symptom severity. Active treatment redistributed subjects across four distinct phenotypes. Discordant distributions (high-low or low-high) were similar in both trials, whereas concordant distributions differed markedly, reflecting distinct pharmacologic effects on esophageal acid-symptom coupling.
Conclusions:
Post-prandial suppression of esophageal acid unmasks latent esophageal acid-symptom phenotypes in gastroesophageal reflux disease. Recognition of these patterns may improve the understanding of treatment response variability and guide individualized therapy.


Related Concept Videos
 01:24
Esophageal Varices-I: Introduction
 01:22
Esophageal Perforation-I: Introduction
The location of esophageal perforation can vary, occurring anywhere along the esophagus....
 01:30
Esophageal Strictures-I: Introduction
Etiology
The primary cause of esophageal strictures is long-standing gastroesophageal reflux disease (GERD), accounting for about 70 to 80% of adult cases. Chronic acid reflux can lead to injury and scarring of the esophageal lining, culminating in...
 03:27
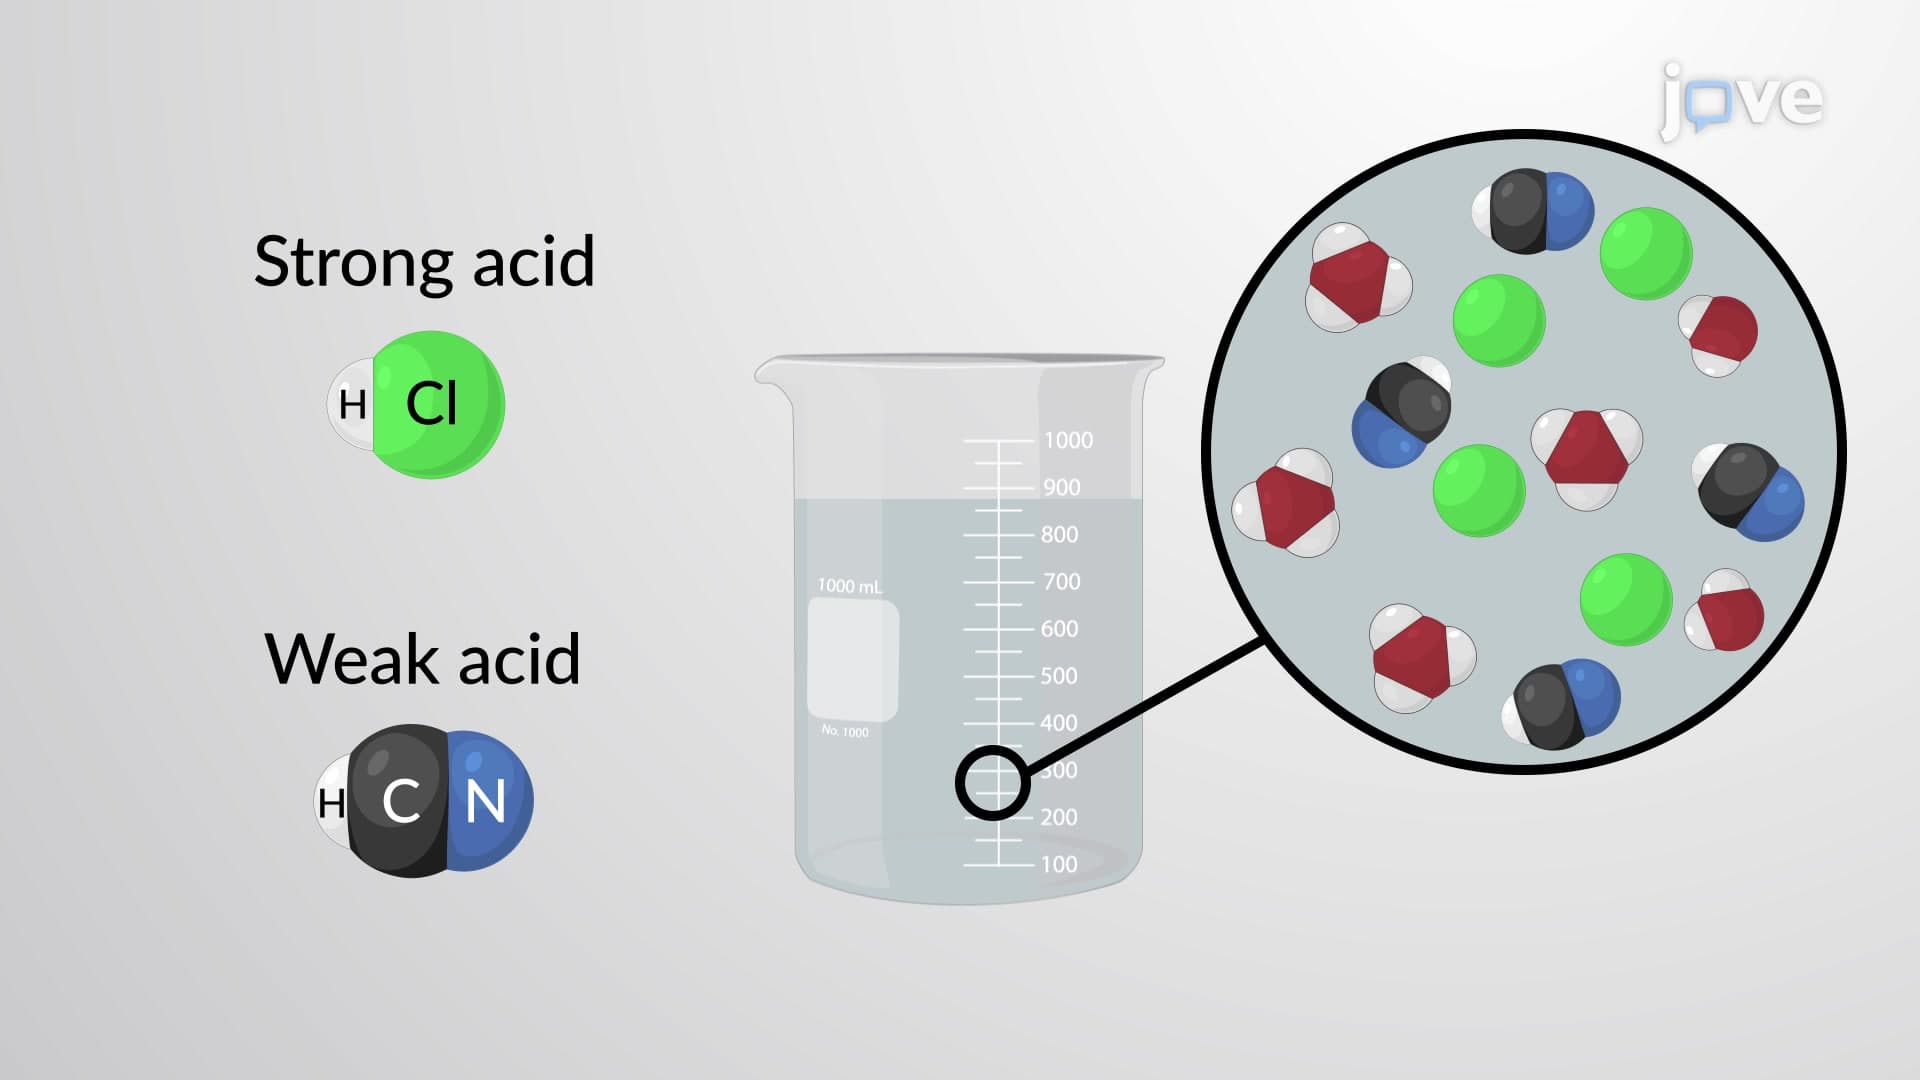
Mixtures of Acids
A Mixture of a Strong Acid and a Weak Acid
In a mixture of a strong acid and a weak acid, the strong acid dissociates completely and becomes a source of almost all the hydronium ions...
 01:26
Esophageal Strictures-II: Clinical Features and Management
Healthcare providers should gather a comprehensive medical history and conduct a physical examination for diagnosis. If esophageal stricture is...
 01:31
Acid Suppressive Drugs for Peptic Ulcer Disease: Antacids
However, this neutralization reaction between...