Related Experiment Video
Updated: Jan 23, 2026
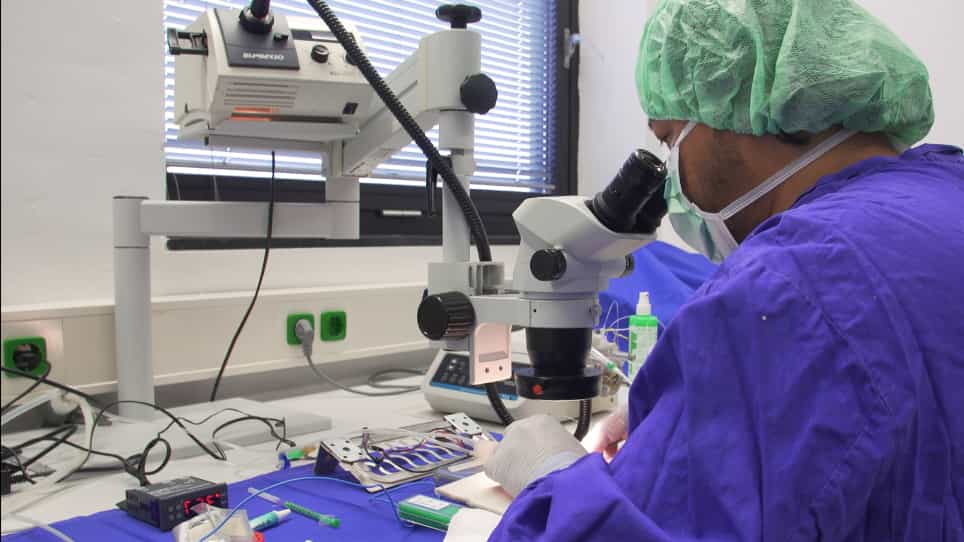

Veno-Venous Extracorporeal Membrane Oxygenation in a Mouse
Published on: October 24, 2018
Protocols for anticoagulation management in pediatric extracorporeal membrane oxygenation: A comparative
Mirte L Jansen1, Nina C Boom2, Nienke Schalij2
1Pediatric Intensive Care Unit, Department of Intensive Care, Leiden University Hospital, Leiden, The Netherlands.

Insights
Monitoring unfractionated heparin in pediatric Extracorporeal Membrane Oxygenation (ECMO) using activated clotting time, activated partial thromboplastin time, or anti-Xa assays did not impact bleeding or survival. The anti-Xa group showed shorter ECMO duration and hospital stays.
Area of Science:
- Pediatric Critical Care Medicine
- Cardiovascular Surgery
- Pharmacology
Background:
- Anticoagulation is crucial for children on Extracorporeal Membrane Oxygenation (ECMO) to prevent thrombosis.
- Current laboratory tests for monitoring unfractionated heparin (UFH) have limitations, necessitating research into optimal methods.
- The choice of monitoring test can influence UFH dosing and patient outcomes.
Purpose of the Study:
- To compare the incidence of hemorrhagic complications among pediatric ECMO patients based on the UFH monitoring method used.
- To evaluate secondary outcomes including thrombotic events, neurological complications, and survival rates.
- To assess the impact of different UFH monitoring strategies on ECMO duration and hospital length of stay.
Main Methods:
- A retrospective cohort study analyzed 118 pediatric ECMO runs from 2010-2021.
- Patients were stratified into three groups based on the UFH monitoring assay: activated clotting time (ACT), activated partial thromboplastin time (aPTT), and anti-Xa.
- Outcomes assessed included hemorrhagic and thrombotic complications, neurological events, survival, ECMO duration, and hospital stay.
Main Results:
- No significant differences in hemorrhagic complications (46.7% ACT vs. 52.5% aPTT vs. 60.4% anti-Xa; p=0.48) were observed across the groups.
- Thrombotic complications, neurological complications, and 30-day survival rates did not differ significantly between the monitoring groups.
- The anti-Xa guided group experienced shorter ECMO duration and hospital stays, received higher UFH doses, and had the shortest duration of ECMO and hospital stay (p=0.02 for both).
Conclusions:
- The choice of UFH monitoring test (ACT, aPTT, anti-Xa) in pediatric ECMO patients was not associated with differences in hemorrhagic complications or mortality.
- The anti-Xa assay guided higher UFH doses and was associated with reduced ECMO and hospital lengths of stay.
- Further research is warranted to determine if combined testing strategies offer superior anticoagulation management in pediatric ECMO.
Abstract:
IntroductionIn children undergoing Extracorporeal Membrane Oxygenation (ECMO), anticoagulation is given to counterbalance the risk of thrombosis. Several laboratory tests are available to monitor heparin, but the ideal method still needs to be determined.MethodsThis retrospective cohort study included all patients under 18 years on ECMO support between 2010 and 2021. At our institution, the test used to monitor unfractionated heparin changed over time, dividing patients into three periods, using either activated clotting time (ACT) (2010-2014), activated partial thromboplastin time (aPTT) (2014-2018) or anti-Xa (2018-2021). The primary objective was to compare the occurrence of hemorrhagic complications. Secondary objectives included thrombotic complications, neurological complications, and survival.ResultsWe included 118 ECMO runs of which 30 ACT-guided, 40 aPTT-guided, and 48 anti-Xa-guided. No statistically significant differences were found in hemorrhagic complications [respectively 46.7% vs. 52.5% vs. 60.4%; p = 0.48], thrombotic complications (p = 0.15), neurological complications (p = 0.13), or 30-days survival (p = 0.84). Duration of ECMO and length of hospital stay were both the shortest in the anti-Xa-guided group (respectively p = 0.02; p = 0.02). During ECMO, the anti-Xa-guided group received a higher unfractionated heparin dose compared to the aPTT- and ACT-guided group [respectively 839 [651-981] vs. 543 [407-692] vs. 330 [223-489] IU/kg d-1, p < 0.001].ConclusionIn our study, the test or titration method used to guide heparin-dosing in children on ECMO, was not associated with hemorrhagic complications and death. Of note, the dose of unfractionated heparin was significantly higher in the anti-Xa-guided group. Combined testing may be more effective than a single method, more studies are needed to establish the optimal strategy.


Related Concept Videos
 01:18
Anticoagulant Drugs: Vitamin K Antagonists and Direct Oral Anticoagulants
Warfarin, a prominent vitamin K antagonist family member, exerts its effect by inhibiting the enzyme VKORC1 (vitamin K epoxide reductase complex 1). By hindering this enzyme, warfarin...
 01:29
Appendicitis-II: Diagnostic Studies and Management
Diagnosing Appendicitis
It requires a multifaceted approach, starting with a detailed physical examination to pinpoint the location and nature of the pain and identify any associated symptoms. Laboratory tests play a crucial role. A complete Blood Count (CBC) typically reveals leukocytosis (an increased number of...
 01:28
Acute Pyelonephritis II: Diagnostic Studies and Management
 01:30
Anticoagulant Drugs: Low-Molecular-Weight Heparins
 01:25
Extracorporeal Removal of Drugs: Hemoperfusion and Hemofiltration
 02:26
Comparing Copy Number Variations and SNPs
Copy number variations or CNVs are the structural variations that cover more than 1kb of DNA sequence. The single nucleotide polymorphism (SNP), on the other hand, is a single nucleotide change or a point mutation that is found in more than 1%...