Related Experiment Video
Updated: Jan 24, 2026
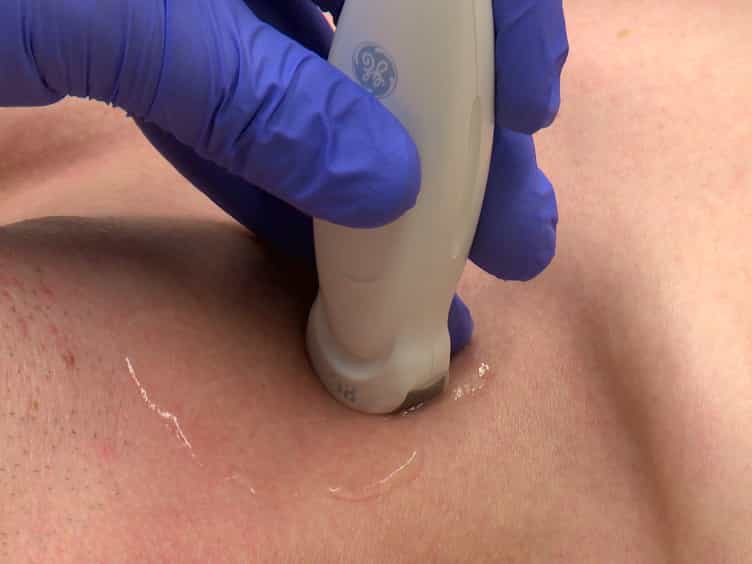

The Supraclavicular Fossa Ultrasound View for Central Venous Catheter Placement and Catheter Change Over Guidewire
Published on: December 23, 2014
Venous Sinus Stenting Using a Ledge-Reducing Catheter, 0.088-in. Catheter-Extender With an External Single Point of
Oded Goren1, Fabio Settecase2, George Luh3
1Neurosurgery Geisinger Health System Danville PA.

Background:
Venous sinus stenting (VSS) is increasingly performed for managing venous sinus stenosis associated with refractory idiopathic intracranial hypertension and/or pulsatile tinnitus. The Monopoint System (MS; Route 92 Medical, San Mateo, CA) is a telescoping catheter system with a single point of control outside the body, consisting of an 8F Guide Catheter (Base Camp), a 0.088-in. inner diameter catheter-extender (HiPoint 88), and a ledge-reducing delivery catheter (Tenzing 8). In this study, we describe the MS technique for VSS and our multicenter clinical experience.
Methods:
We retrospectively reviewed consecutive patients who underwent VSS with the MS from 2022 to 2023 for intracranial hypertension and/or pulsatile tinnitus at 13 sites. Base Camp is placed in the internal jugular bulb. HiPoint 88 is advanced over the Tenzing 8 through the stenosis. The stent-delivery system is placed across the stenosis (inside the HiPoint 88), then unsheathed by HiPoint pull-back, followed by successful stent deployment. Operators were also surveyed on MS performance.
Results:
Seventy-one patients were included, 97% female, mean age 40 ± 11 years, body mass index 35 ± 11. The primary indication for venous stenting was intracranial hypertension (79%, 56/71) and/or debilitating pulsatile tinnitus (87%, 62/71). Visual changes were present in 74%, with papilledema in 63%. Hipoint 88 advanced beyond the stenosis over Tenzing 8 in all cases, and all stents (diameters 6-10 mm and lengths 30-80 mm) successfully deployed. Median stenosis decreased from 80% (interquartile range 75-87) to 0% (interquartile range 0-0) post stenting (P<0.001). There were no Monopoint-related complications. compared with the operators' typical VSS catheter setup/technique, MS was rated "better" in 93% and "slightly better" in 6%; operators cited ease of crossing the stenosis, improved trackability and support, as well as lack of stent-catheter length incompatibilities. Headache, pulsatile tinnitus, and papilledema improved in 81%, 95%, and 91%, respectively.
Conclusion:
The MS is a safe and effective catheter platform for VSS.
More Related Videos

Related Concept Videos
 01:13
Controls in Experiments
 01:20
Venous Thrombosis II: Clinical Manifestations and Diagnostic Studies
 01:11
Work Done on a System by External Force
In the presence of a non-conservative opposing force, like friction, some part of the work done...
 01:16
ECG Interpretation of Arrhythmias I: Sinus Arrhythmias
Types of Arrhythmias
Sinus Node Arrhythmias
Sinus Bradycardia: Originating from the sinoatrial (SA) node, sinus bradycardia involves slower impulses, resulting in a heart rate of less than 60 beats per minute (bpm). Causes include sleep, vagal stimulation, beta-blockers, hypothyroidism,...
 01:04
Venous Return
What is Venous Return?
Venous return refers to the rate at which blood flows back to the heart from the body's peripheral veins. It's an integral part of the circulatory system...
 01:24
External and Internal Respiration