Related Experiment Video
Updated: Jan 25, 2026

Acupoint Needle-Embedding Combined with Ironing Therapy for Postoperative Pain After Anal Surgery
Published on: June 23, 2023
Low-level laser therapy in oral surgery: how strong is the evidence for improved postoperative outcomes?
1NIHR Academic Clinical Lecturer in Oral Surgery, Peninsula Dental School, University of Plymouth, Plymouth, UK. araz.ahmed@plymouth.ac.uk.

A Commentary On:
Chaple Gil A, Díaz L, Von Marttens A, Sotomayor C, Basualdo J, Beltrán V, Jorquera G, Caviedes R, Fernández E. The efficacy of low-level laser therapy in oral surgery: a systematic review of randomized controlled trials. Photodiagnosis Photodyn Ther 2025; https://doi.org/10.1016/j.pdpdt.2025.104594 .
Design:
This systematic review followed PRISMA 2020 guidelines and evaluated randomised controlled trials investigating the effect of low-level laser therapy on postoperative healing and comfort following oral surgery. The protocol was registered in PROSPERO. The Cochrane RoB 2 tool was used for quality assessment, and the PROPS framework was applied to interpret the clinical relevance of outcomes such as pain and wound healing.
Case Selection:
Eighteen randomised controlled trials involving 771 participants were included. The surgical procedures comprised third molar extraction, implant placement and a range of periodontal and mucogingival procedures. Most participants were healthy adults. Laser parameters ranged from 660 to 1064 nm in wavelength and from 3 to 35 J/cm² in fluence.
Data Analysis:
Because of variability in laser parameters, timing of therapy and outcome measures, meta-analysis was not feasible. The authors therefore synthesised the findings narratively, focusing on postoperative pain, inflammation and tissue healing.
Results:
Low-level laser therapy significantly improved early epithelialisation and soft tissue healing in the included trials, particularly when wavelengths between 660 and 810 nm and fluences between 3 and 12 J/cm² were used. Several studies reported reductions in inflammatory cytokines such as tumour necrosis factor alpha and interleukin-6, together with increased vascular endothelial growth factor expression. Pain scores decreased by ~30-55% within the first postoperative week, and several trials reported fewer postoperative complications, including delayed healing and local infection, in laser-treated groups. Twelve studies were judged to be at low risk of bias, five had some concerns and one was at high risk. Follow-up was predominantly short term (7-14 days) for soft-tissue outcomes, although a minority of implant-related studies extended observation to several months to assess bone and peri-implant parameters.
Conclusions:
Low-level laser therapy appears to accelerate early healing and reduce postoperative pain after oral surgery, with no significant adverse effects reported and some evidence of reduced postoperative complication rates. However, heterogeneity in dosimetry, protocols and outcome assessment, together with generally small sample sizes and limited long-term follow-up, reduces confidence in the precision and durability of these effects, and the overall certainty of evidence remains low.

Related Concept Videos
 02:55
The Evidence for Evolution
 02:28
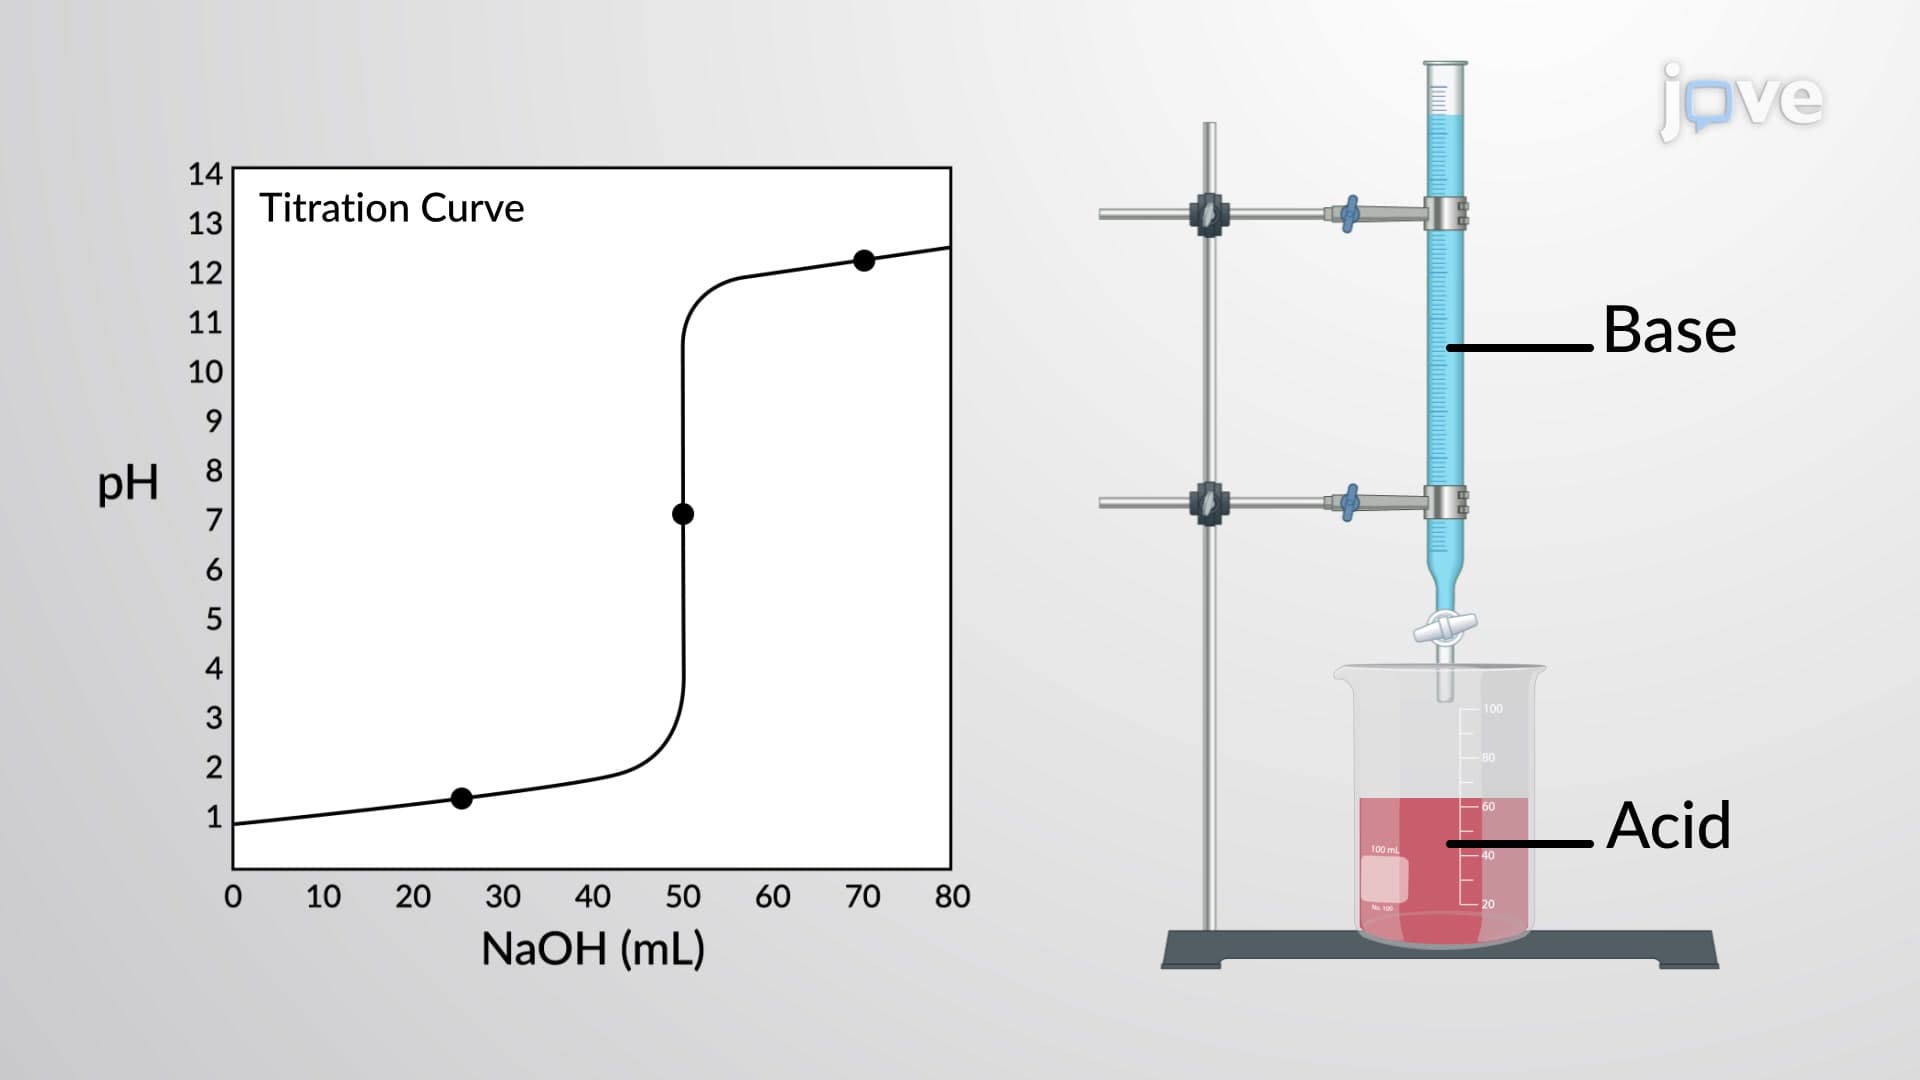
Titration Calculations: Strong Acid - Strong Base
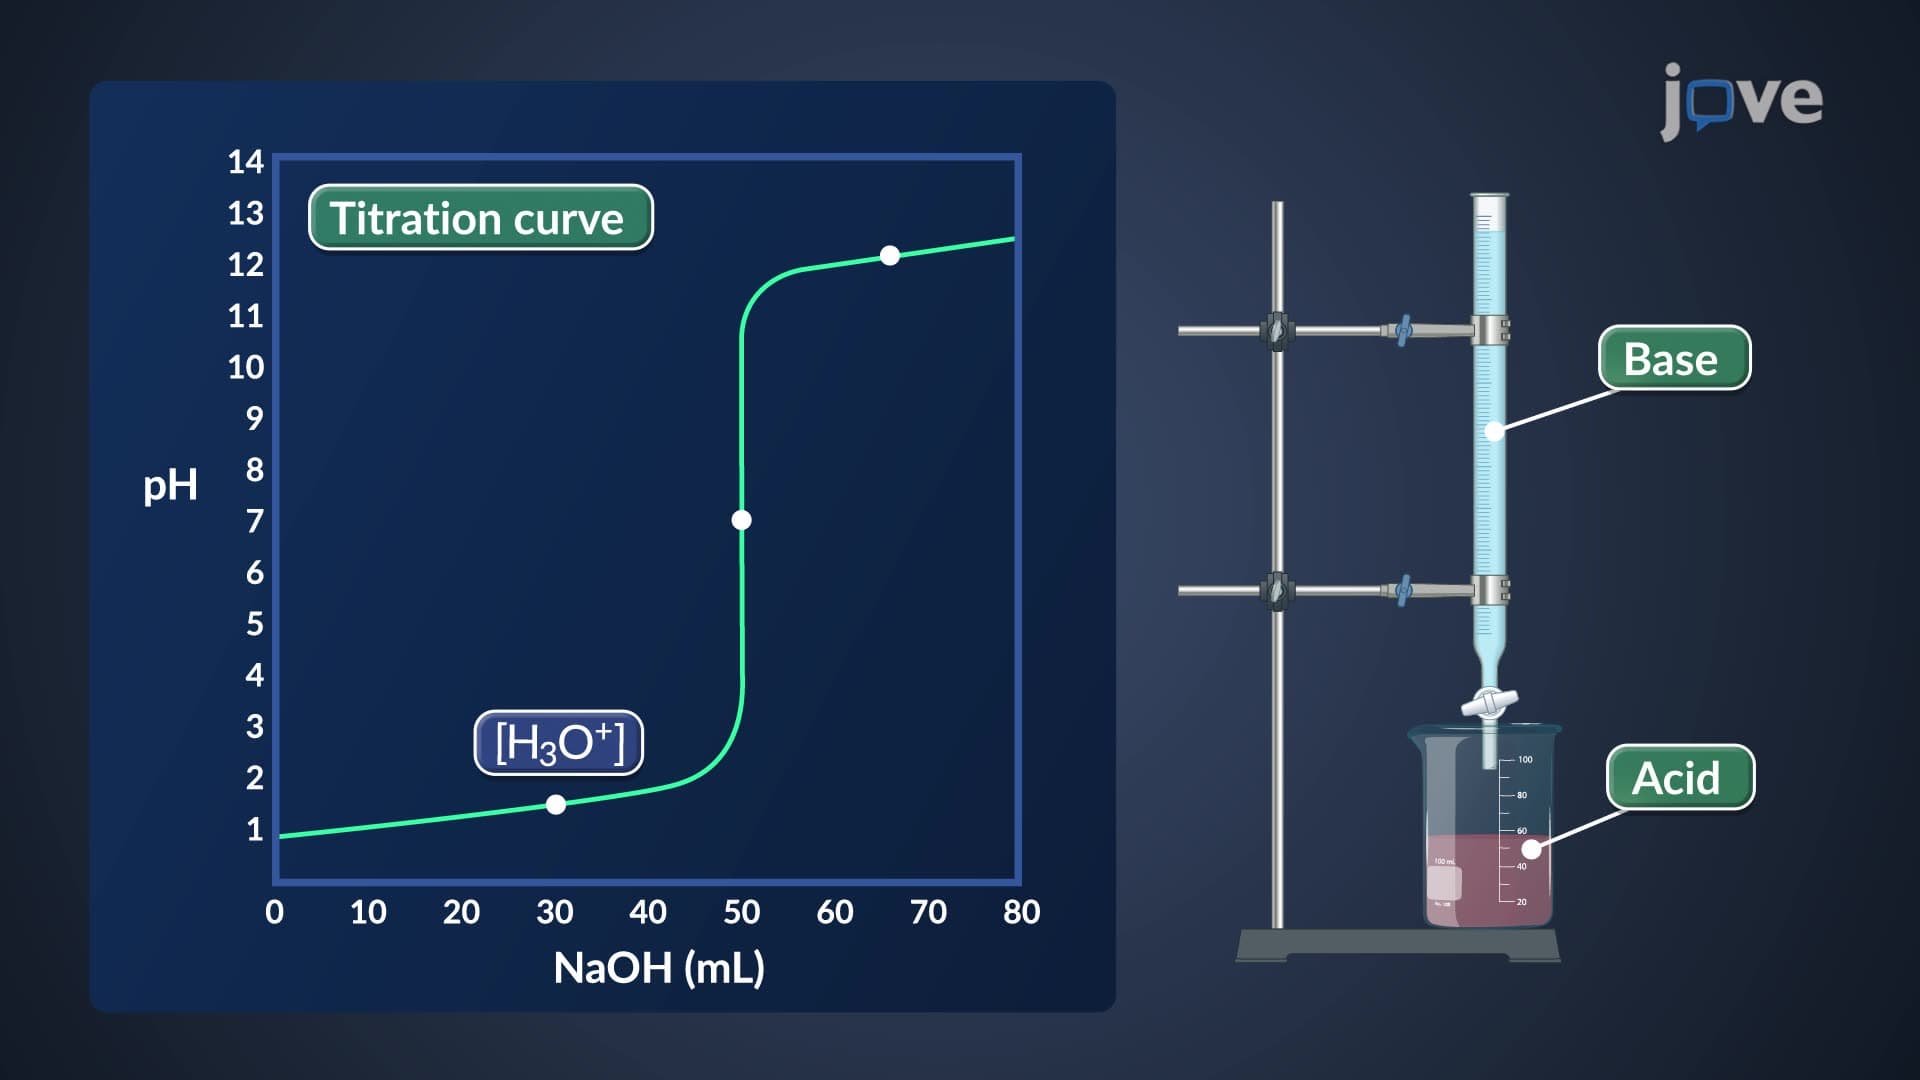
A titration is carried out for 25.00 mL of 0.100 M HCl (strong acid) with 0.100 M of a strong base NaOH. The pH at different volumes of added base solution can be calculated as follows:
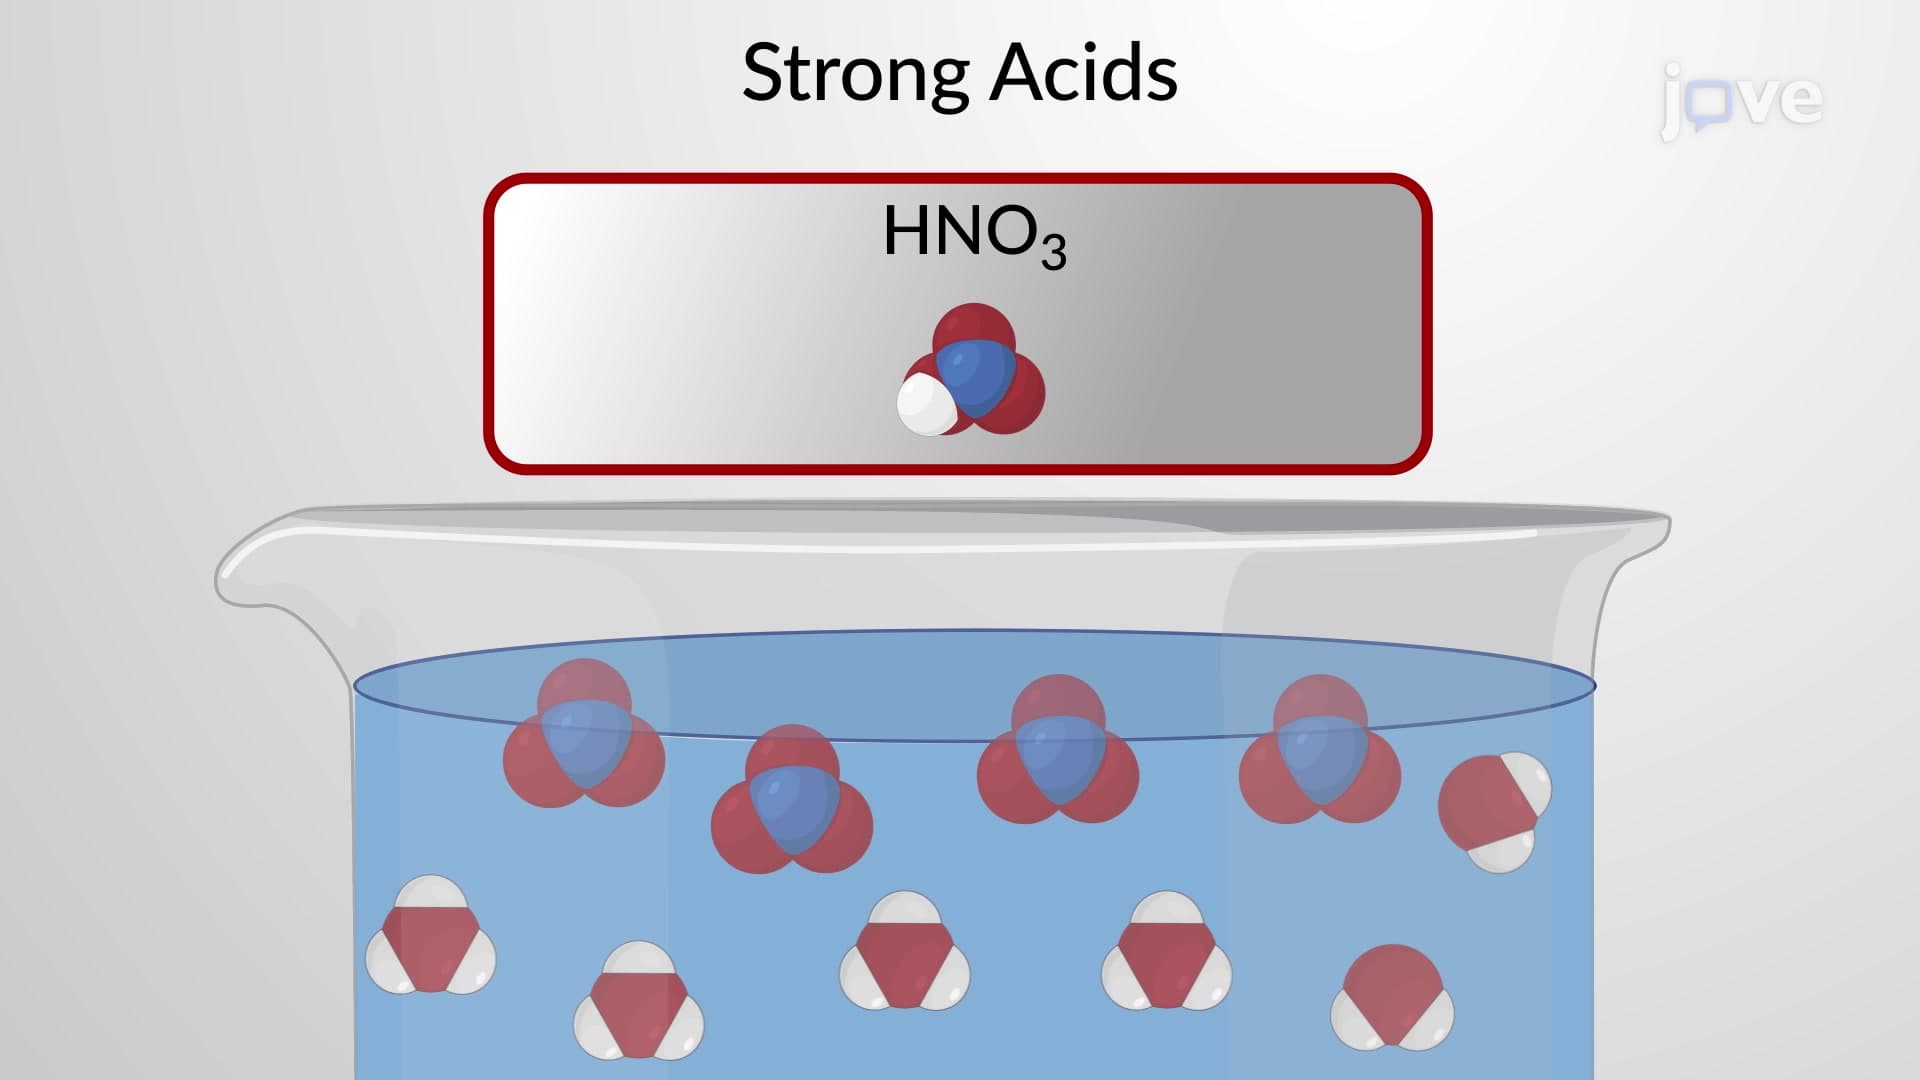
(a) Titrant volume = 0 mL. The solution pH is due to the acid ionization of HCl. Because this is a strong acid, the ionization is complete and the hydronium ion molarity is 0.100 M. The pH of the solution is then:
 03:22
Strong Acid and Base Solutions
 01:23
Titration of a Strong Acid with a Strong Base
 02:24
Predicting Reaction Outcomes
 03:55
Titration Calculations: Weak Acid - Strong Base
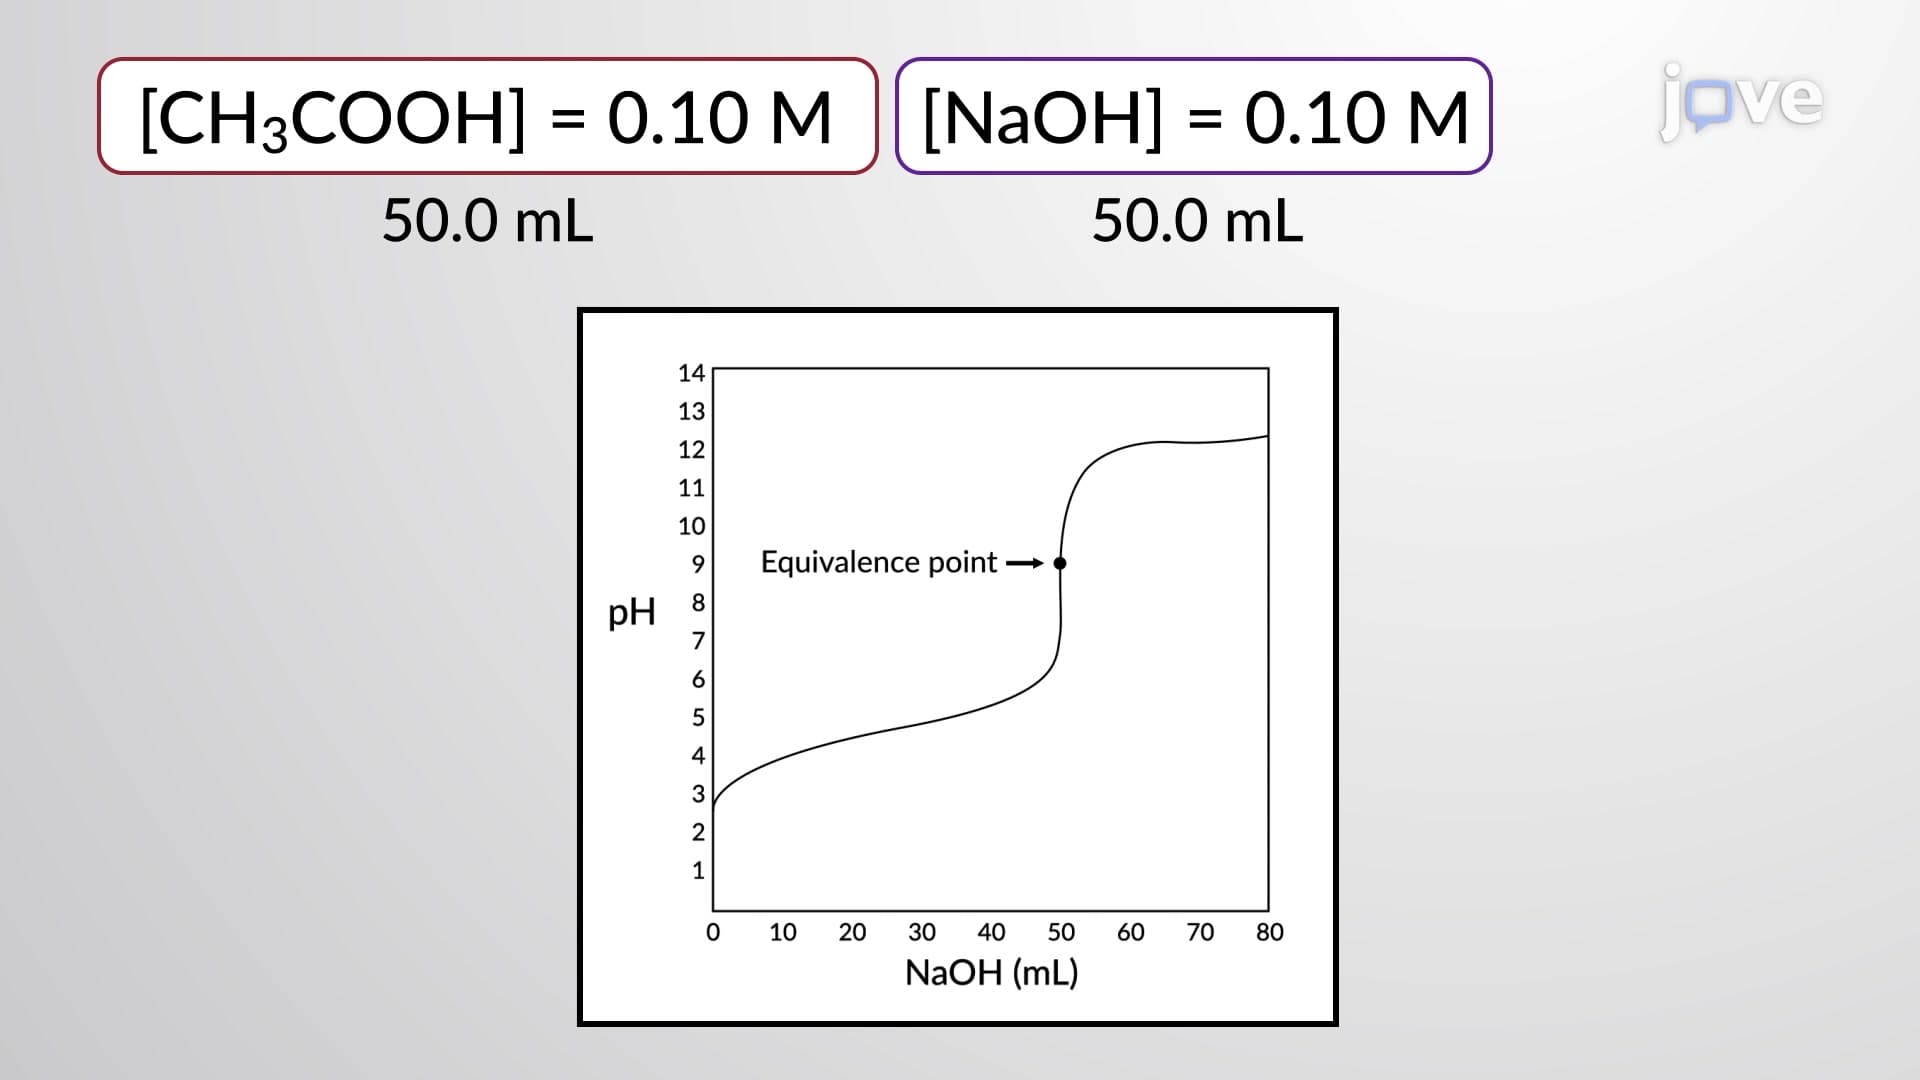
For the titration of 25.00 mL of 0.100 M CH3CO2H with 0.100 M NaOH, the reaction can be represented as: