Related Experiment Video
Updated: Jan 29, 2026
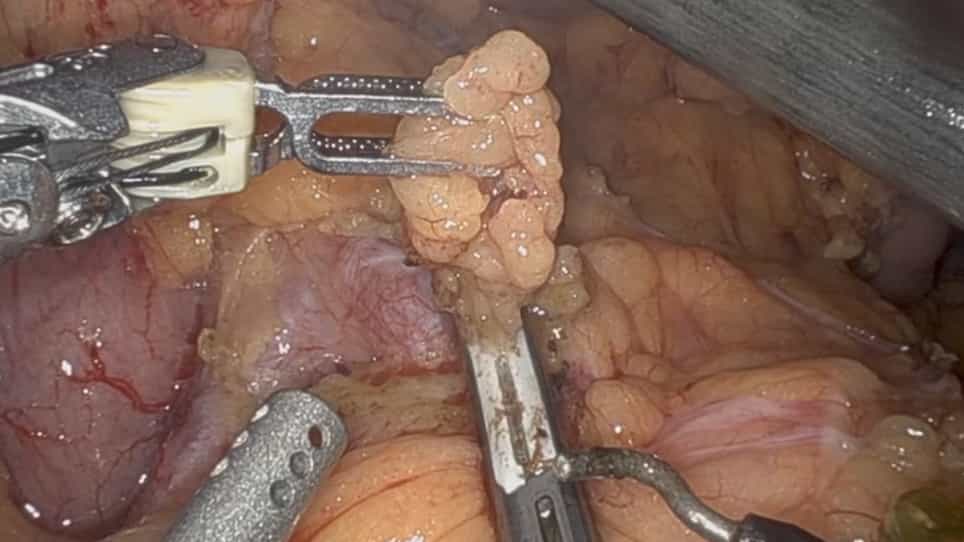

Robot Assisted Distal Pancreatectomy with Celiac Axis Resection DP-CAR for Pancreatic Cancer: Surgical Planning and Technique
Published on: August 14, 2021
Class IA Pancreatosplenectomy with Class IA Celiac Axis Resection, SMA Isolation, and Lateral Venous Reconstruction
Valentin Artaud1, Xavier Giudcelli1, Laurent Sulpice2
1Service de Chirurgie Hépatobiliaire et Digestive, Hôpital Pontchaillou, Centre Hospitalier Universitaire, Rennes, France.

Surgical treatment of pancreatic tumors invading the celiac axis is increasingly performed following induction therapy. This generally consists of a pancreatosplenectomy with celiac axis resection. When performed without revascularization, it is classified as IA.1 This video presents a 52-year-old patient with no medical history, in whom a pancreatic body mass was incidentally discovered. Imaging revealed a locally advanced lesion involving the celiac axis, contacting the superior mesenteric artery and the portal-mesenteric confluence. Biopsies were noncontributory, CA 19-9 was normal, and the staging workup was negative. After multidisciplinary discussion, induction therapy was recommended. The patient received 12 courses of FOLFIRINOX followed by 50.4 Gy radiochemotherapy with capecitabine. In the absence of progression, surgical resection was undertaken. Preoperative hepatic and left gastric artery embolization was performed to promote collateral circulation and reduce postoperative morbidity.2,3 A distal splenopancreatectomy with celiac axis resection, full isolation of the superior mesenteric artery, and lateral resection of the portal-mesenteric axis including the splenic vein origin were performed. Venous reconstruction was achieved using a peritoneal patch. The procedure was uneventful, and postoperative recovery was uncomplicated. Locally advanced pancreatic body tumors involving the celiac trunk and/or superior mesenteric artery may be suitable for resection after optimal neoadjuvant therapy and preoperative vascular conditioning. Such complex procedures require a multidisciplinary approach and should be performed in specialized pancreatic surgery centers with interventional radiology expertise in selective embolization.
Surgical treatment of pancreatic tumors invading the celiac axis is increasingly performed following induction therapy. This generally consists of a pancreatosplenectomy with celiac axis resection. When performed without revascularization, it is classified as IA.1 This video presents a 52-year-old patient with no medical history, in whom a pancreatic body mass was incidentally discovered. Imaging revealed a locally advanced lesion involving the celiac axis, contacting the superior mesenteric artery and the portal-mesenteric confluence. Biopsies were noncontributory, CA 19-9 was normal, and the staging workup was negative. After multidisciplinary discussion, induction therapy was recommended. The patient received 12 courses of FOLFIRINOX followed by 50.4 Gy radiochemotherapy with capecitabine. In the absence of progression, surgical resection was undertaken. Preoperative hepatic and left gastric artery embolization was performed to promote collateral circulation and reduce postoperative morbidity.2,3 A distal splenopancreatectomy with celiac axis resection, full isolation of the superior mesenteric artery, and lateral resection of the portal-mesenteric axis including the splenic vein origin were performed. Venous reconstruction was achieved using a peritoneal patch. The procedure was uneventful, and postoperative recovery was uncomplicated. Locally advanced pancreatic body tumors involving the celiac trunk and/or superior mesenteric artery may be suitable for resection after optimal neoadjuvant therapy and preoperative vascular conditioning. Such complex procedures require a multidisciplinary approach and should be performed in specialized pancreatic surgery centers with interventional radiology expertise in selective embolization.
More Related Videos
 12:34
Robot-Assisted Radical Antegrade Modular Pancreatosplenectomy Including Resection and Reconstruction of the Spleno-Mesenteric Junction
Published on: January 3, 2020
 12:07
Laparoscopic Radical Antegrade Modular Pancreatosplenectomy via Dorsal-Caudal Artery Approach for Pancreatic Neck-Body Cancer
Published on: November 18, 2022
Related Concept Videos
 01:25
Drug Classes and Categories
 01:25
Antibody Structure and Classes
The basic structure of an antibody consists of four protein chains: two identical heavy chains and two identical light chains. These chains are held together by disulfide bonds and other non-covalent interactions, forming a Y-shaped structure.
 01:15
Antihypertensive Drugs: Thiazide-Class Diuretics
 01:24
Antiarrhythmic Drugs: Class II Agents as β-Adrenergic Blockers
 01:22
Antiarrhythmic Drugs: Class I Agents as Sodium Channel Blockers
Class 1A Antiarrhythmic Drugs: These drugs work by moderately blocking sodium channels,...
 01:12
Antiarrhythmic Drugs: Class III Agents as Potassium Channel Blockers