Related Experiment Video
Updated: Jun 5, 2026
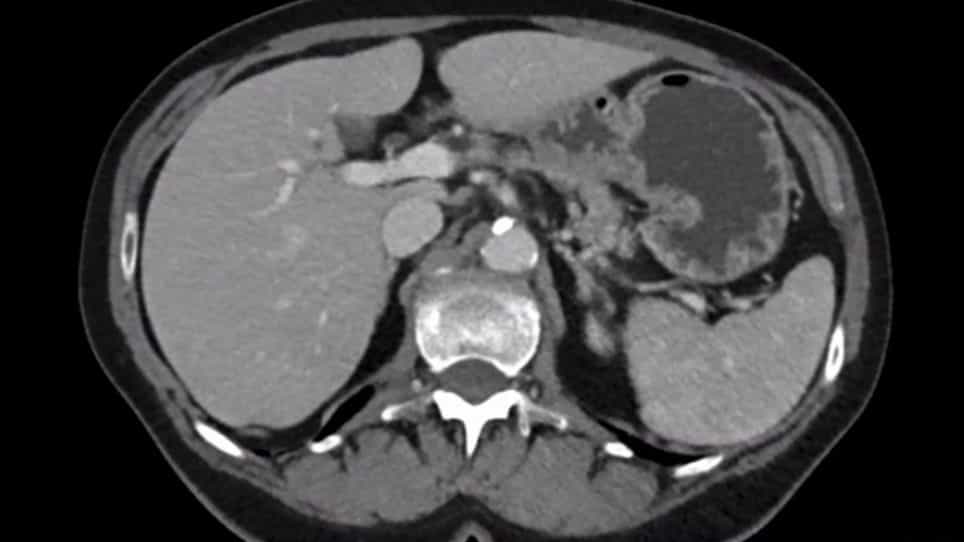

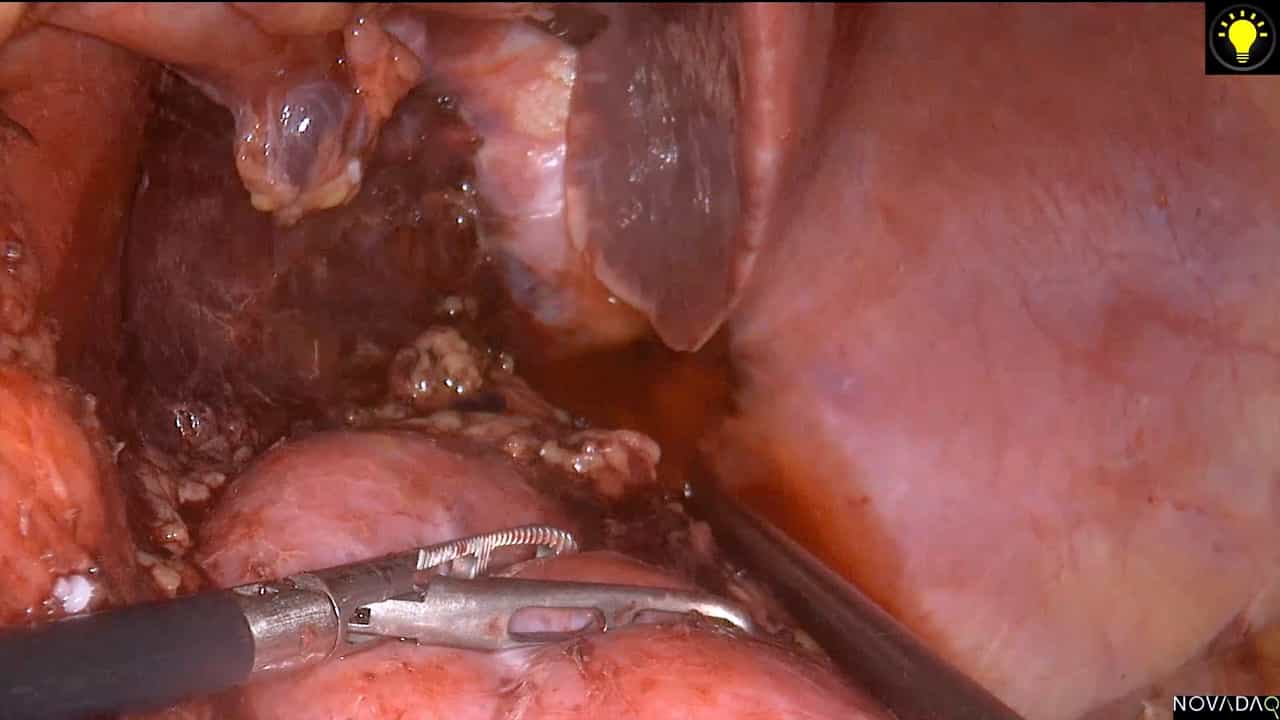
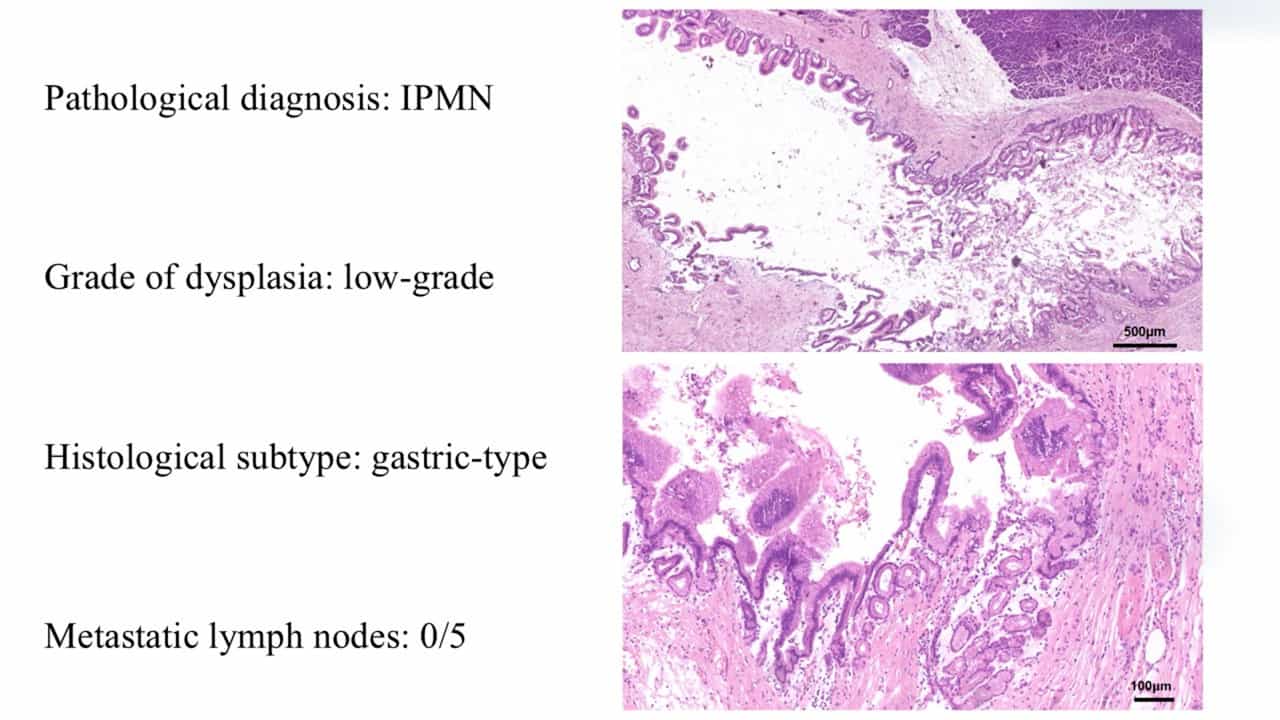
Laparoscopic Radical Left Pancreatectomy for Pancreatic Cancer: Surgical Strategy and Technique Video
Published on: June 6, 2020
Predicting Best Performers After Minimally Invasive Left Pancreatectomy: Insights From a National Cohort
Clément Pastier1,2, Marc-Anthony Chouillard1, Charles De Ponthaud2,3,4
1Department of HPB Surgery and Liver Transplantation, AP-HP, Beaujon Hospital, University of Paris Cité, Centre de Recherche sur l'Inflammation, INSERM Unité Mixte de Recherche 1149, Clichy, France.

Objective:
To evaluate predictors of ideal postoperative trajectories after minimally invasive left pancreatectomy (MILP).
Summary Background Data:
Postoperative course after MILP can be assessed through the Ideal Outcome (IO), but no predictive tool is currently available.
Methods:
MILP performed between 2010-2022 across 55 French centers were included. 90-days IO required absence of mortality, severe complications, postoperative pancreatic fistula grade B/C (CR-POPF), reoperation, readmission, and length of stay (LOS)≤75 th percentile; Best Performer (BP) was IO with LOS≤25 th p. Predictors were evaluated using multivariable logistic regression and extreme gradient boosting (XGB). Model performance was assessed with nested cross-validation and 1,000-iteration bootstrap resampling.
Results:
Among 2,092 MILP, mortality was 1.3%, reoperation 5.6%, severe morbidity 17.9%, CR-POPF 18.8%, and readmission 15.3%; median LOS 9 days [IQR 7-13]. IO and BP occurred in 59.6% and 28.1%. Following a stepwise strategy, starting with a preoperative multivariable logistic regression model (AUC 0.57), then a preoperative-only XGBoost model (AUC 0.59), improved by inclusion of intraoperative variables (AUC 0.62); finally, after refining the endpoint to Best Performer (IO+LOS ≤25th percentile), the final XGBoost model achieved an AUC of 0.72 (95%CI 0.70-0.74). SHAP analysis identified center-volume and operative duration as the strongest contributors, followed by age, BMI, conversion, blood loss, and splenectomy. At the optimal threshold, sensitivity reached 0.78, specificity 0.57, PPV 0.41, and NPV 0.87. An online risk calculator is at disposal.
Conclusions:
Predicting ideal postoperative trajectory after MILP remains challenging; identifying determinants may help optimize postoperative pathways by integrating preoperative and intraoperative determinants of recovery.