Related Experiment Video
Updated: Jan 31, 2026
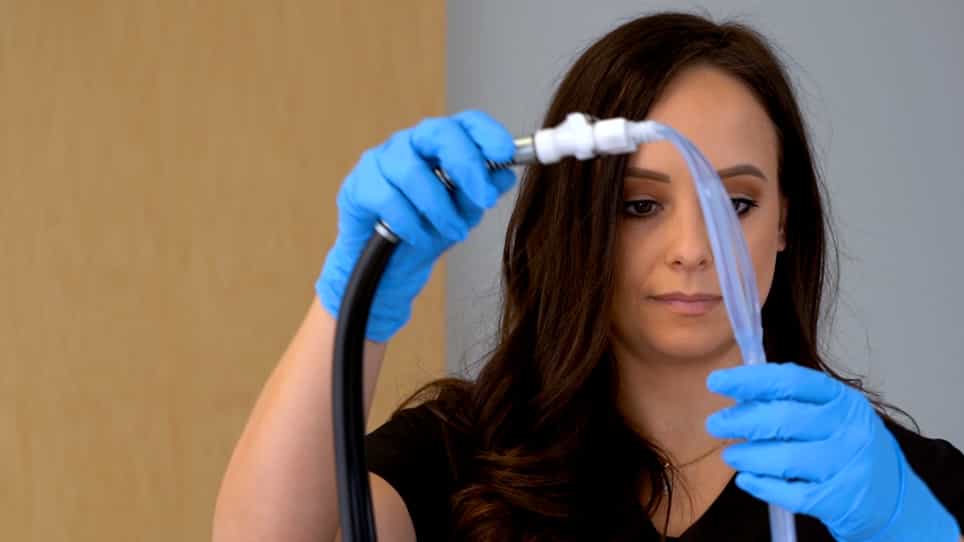

Cooling or Warming the Esophagus to Reduce Esophageal Injury During Left Atrial Ablation in the Treatment of Atrial Fibrillation
Published on: March 15, 2020
Longitudinal Esophageal Wall Rupture and Mediastinitis Due to Esophageal Warming Balloon Dysfunction During Left
Roza Makarian1, Seurs Ward1,2, Nafteux Philippe1,2
1Department of Thoracic Surgery, University Hospital Leuven, Leuven, Belgium.

Introduction:
Atrial fibrillation (AF) is a common supraventricular tachyarrhythmia associated with an increased risk of stroke and mortality. Catheter ablation using pulmonary vein isolation is a standard treatment for patients refractory to antiarrhythmic drugs, where radiofrequency ablation and cryoablation are the two most commonly used procedures. Although generally safe, esophageal baro- and thermal injuries remain a rare but life-threatening complication due to the close anatomical relationship between the esophagus and the left atrium. Various protective strategies, such as esophageal temperature monitoring and displacement, aim to mitigate this risk, yet their efficacy and safety are still under investigation.
Case Presentation:
A 72-year-old male with persistent AF underwent cryoablation with an esophageal warming device to prevent esophageal thermal injury. Despite an uneventful procedure, postoperatively, the patient developed severe thoracic pain. Imaging revealed esophageal perforation with active bleeding. Conservative management, including nil per os, antibiotics, and drainage, was initially pursued. However, worsening clinical status necessitated thoracoscopic intervention. Findings included extensive hematoma and inflammation, precluding primary repair. Conservative treatment with enteral nutrition and drainage led to gradual improvement, and the patient was discharged on Day 24. Follow-up confirmed near-complete healing, with no recurrence of AF.
Conclusion:
Severe esophageal complications post-cryoablation remain rare but pose significant morbidity. In this case, overinflation of the esophageal warming device likely contributed to barotraumatic injury, worsening of esophageal fragility, leading to a major perforation with extensive mediastinitis. While protective devices aim to reduce ETI, their potential risks must be carefully considered. Optimal patient selection and refined protective strategies are crucial to enhancing procedural safety.
More Related Videos
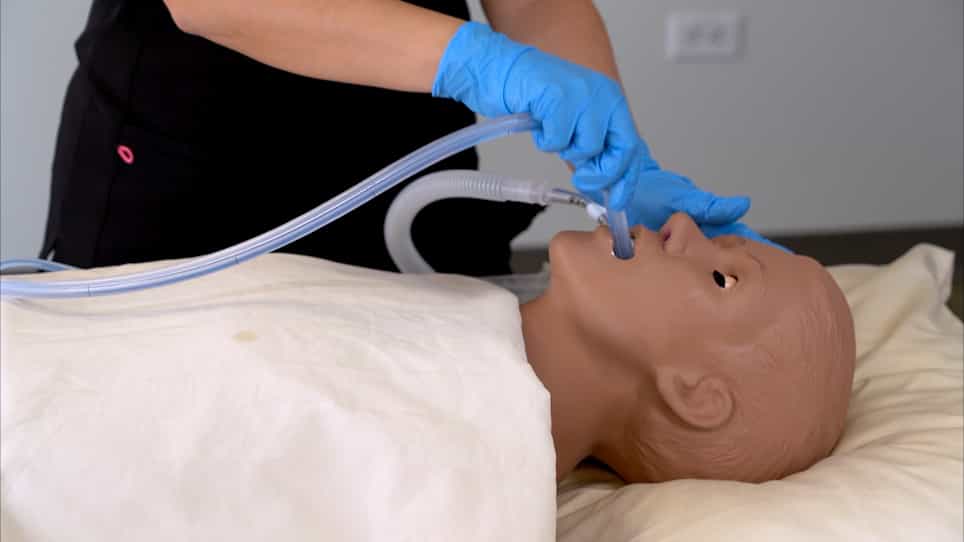

Related Concept Videos
 01:24
Esophageal Varices-I: Introduction
 01:22
Esophageal Perforation-I: Introduction
The location of esophageal perforation can vary, occurring anywhere along the esophagus....
 01:30
Esophageal Strictures-I: Introduction
Etiology
The primary cause of esophageal strictures is long-standing gastroesophageal reflux disease (GERD), accounting for about 70 to 80% of adult cases. Chronic acid reflux can lead to injury and scarring of the esophageal lining, culminating in...
 01:26
Esophageal Strictures-II: Clinical Features and Management
Healthcare providers should gather a comprehensive medical history and conduct a physical examination for diagnosis. If esophageal stricture is...
 01:28
Esophageal Perforation-II: Clinical Manifestations and Management
Clinical Manifestations:
 01:28
Esophageal Varices-II: Clinical Features and Management
In the initial assessment, a thorough review of the patient's medical history is vital to identify risk factors such as liver disease, alcohol...