Related Experiment Video
Updated: Feb 1, 2026
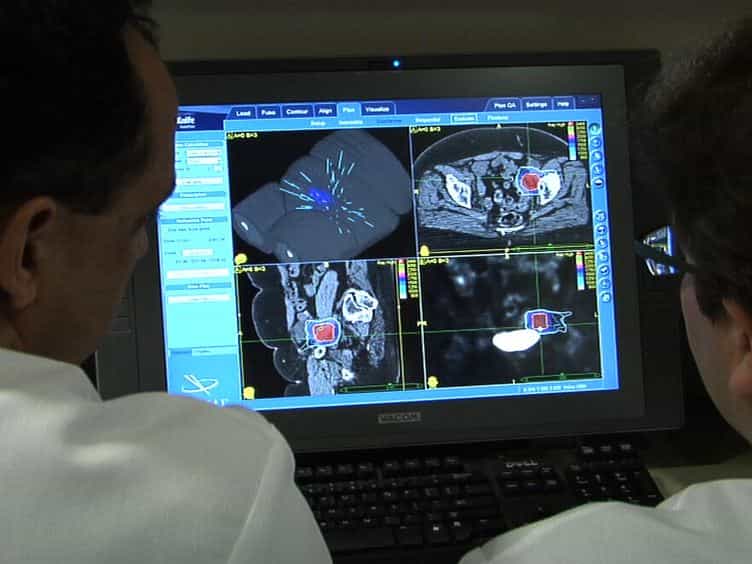
Stereotactic Radiosurgery for Gynecologic Cancer
Published on: April 17, 2012
De novo headache after microsurgical resection or stereotactic radiosurgery of brain arteriovenous malformation
Gui-Jun Zhang1, Wei Wang2, Jun-Feng Huo3,4
1Department of Neurosurgery, Shandong Provincial Hospital Affiliated to Shandong First Medical University, Jinan, China.

Objective:
The aim of this study was to elucidate the adverse factors associated with brain arteriovenous malformation (BAVM)-related de novo headache after stereotactic radiosurgery (SRS) or microsurgery.
Background:
There is a paucity of literature on posttreatment de novo headaches in initially headache-naïve patients who undergo treatment.
Methods:
This retrospective cohort study analyzed patients aged 18 years or older who underwent SRS or microsurgery for a BAVM at our single center in Sichuan Province, China, between January 2010 and December 2019. Patients who did not present with headaches before treatment were included. Headache diagnosis and characteristics were performed according to the International Classification of Headache Disorders, 3rd edition criteria. The primary outcome was BAVM-related de novo headache after treatment. Statistical analysis was conducted on demographic, clinical, and radiographic characteristics to assess the distributions of the two groups of patients with and without posttreatment de novo headache. Subgroup analysis was further conducted on the SRS and microsurgery.
Results:
Over the 10-year study period, we identified 194 patients with BAVM who presented without headache and who underwent SRS or microsurgery. Thirty-seven patients (19.1%) developed posttreatment de novo headache. In the SRS treatment cohort, statistically significant differences were detected between the headache and nonheadache subgroups with respect to the Spetzler-Martin (SM) grade (p = 0.018) and lesion diameter (p = 0.028). Multivariable logistic regression analysis confirmed that only the higher SM grade remained an independent adverse factor for de novo headache (adjusted odd ratio [OR] = 3.48, 95% confidence interval [CI] = 1.29-9.35, p = 0.013; high grade versus low grade BAVM). In the microsurgery treatment cohort, the lesion size in the de novo headache subgroup was significantly larger than that in the nonheadache subgroup, with a mean lesion diameter of 3.8 ± 0.3 cm versus 2.9 ± 0.2 cm (p = 0.024). Univariable logistic regression analysis revealed that only a larger diameter was significantly associated with increased odds of de novo headache (OR = 1.52, 95% CI = 1.04-2.21, p = 0.030; per 1 cm increase in diameter).
Conclusion:
In the microsurgery treatment subgroup, a larger BAVM was associated with increased odds of de novo headache (per 1 cm increase); in the SRS treatment subgroup, grades III-V were associated with increased odds of de novo headache.


Related Concept Videos
 01:23
Brain Waves
 01:30
Organization of the Brain
Hindbrain
The hindbrain, located at the base of the brain, plays a vital role in regulating automatic processes that sustain life. It includes the medulla oblongata, which is essential for...
 01:14
Brain Imaging
These technologies include computerized axial tomography (CAT or CT scans), positron-emission tomography (PET scans), magnetic resonance imaging (MRI), functional magnetic resonance imaging (fMRI), and Transcranial Magnetic...
 00:49
The Blood-brain Barrier
 01:18
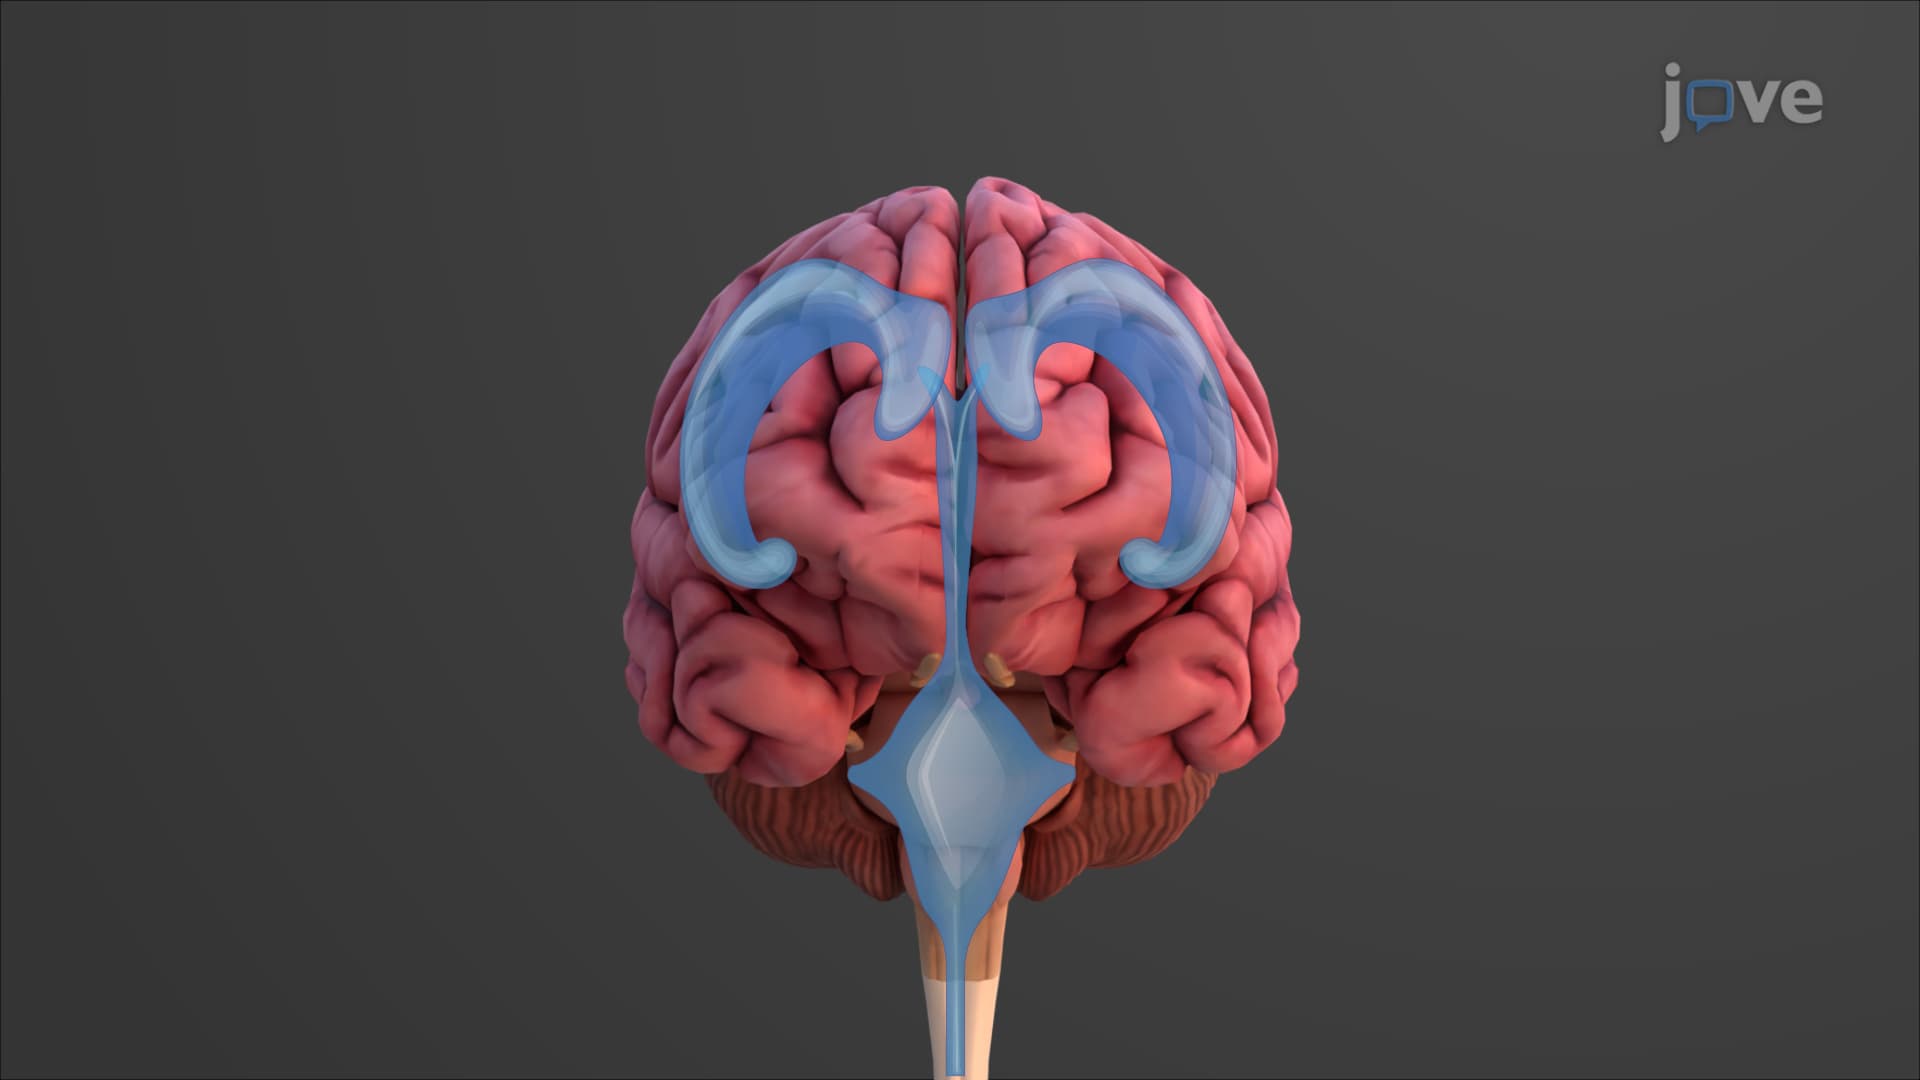
Anatomy of the Brain: Ventricles
 01:22
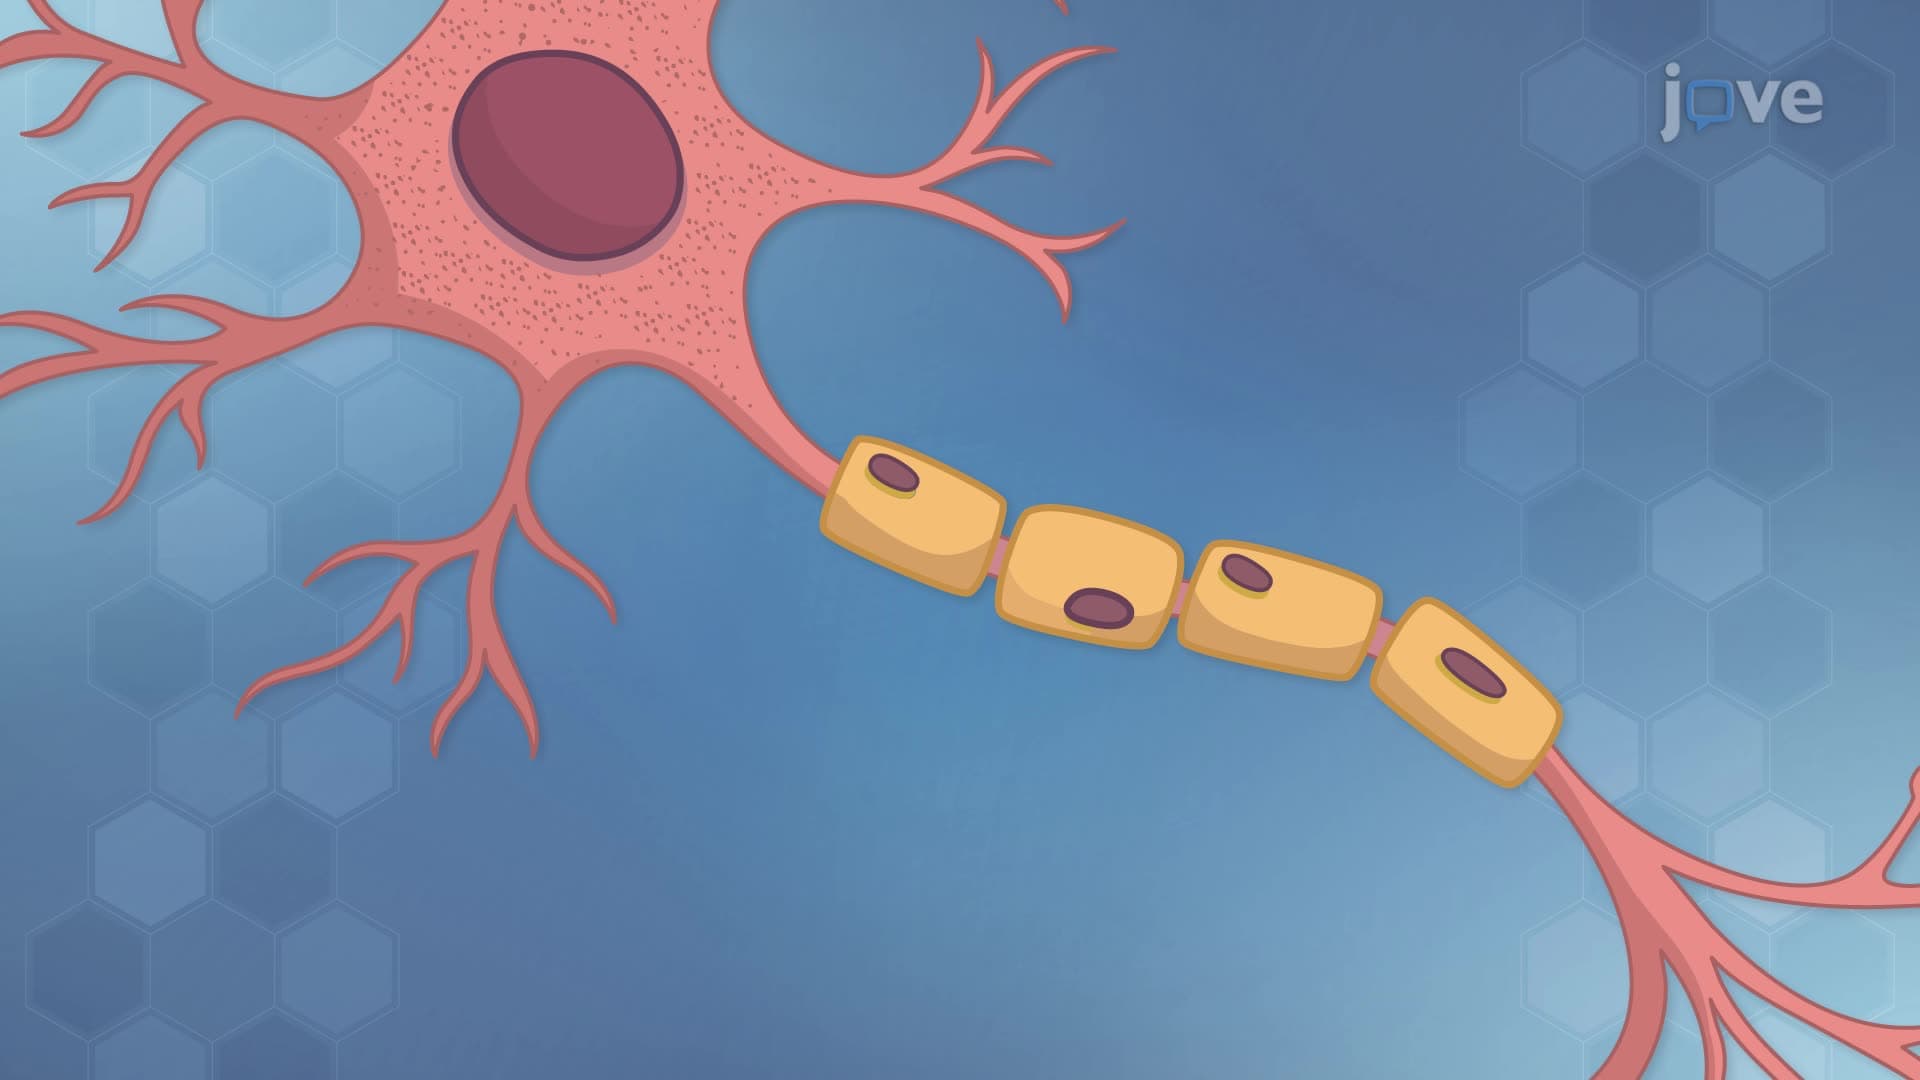
Neurons as Communicators of the Brain
Cell Body
The cell body, also known...