Related Experiment Video
Updated: Feb 7, 2026
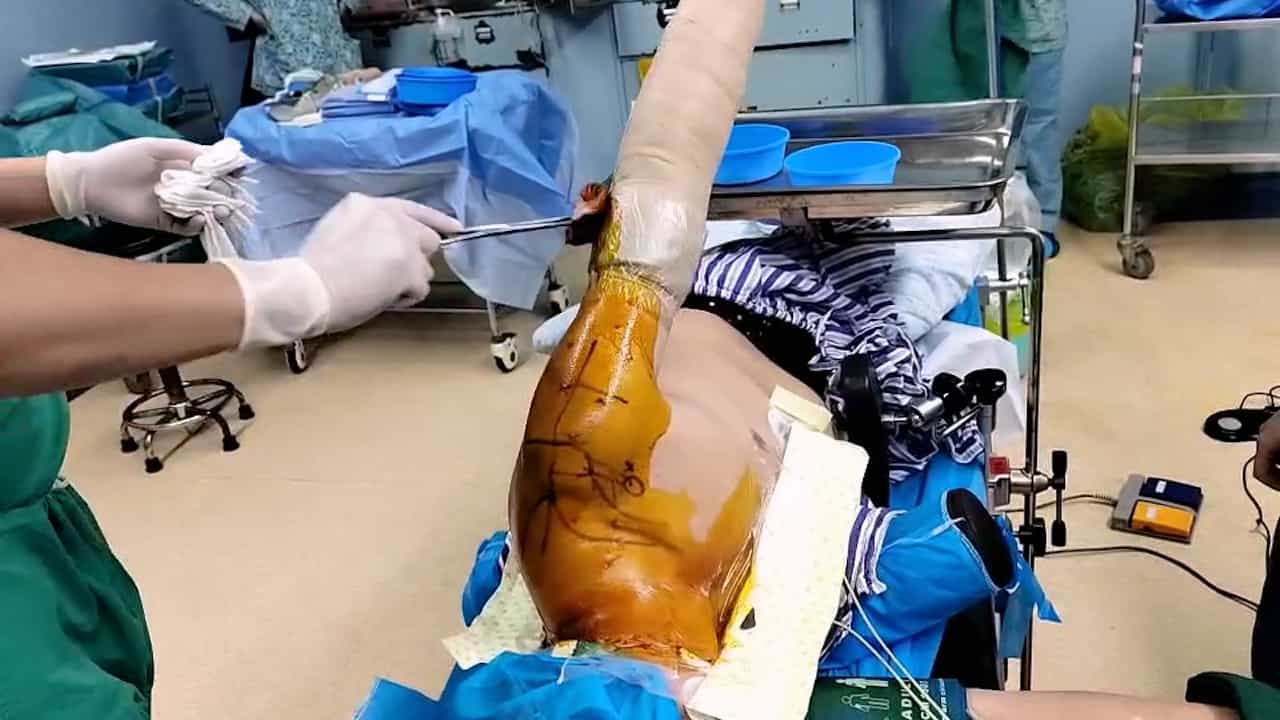

Arthroscopic Management of Massive Irreparable Rotator Cuff Tears: Whole Rotator Cable Reconstruction Using Proximal Biceps Tendon Autograft
Published on: June 6, 2025
Biceps Anterior Cable Reconstruction for Massive Rotator Cuff Tears
Matthew P Kolevar1, Sophia McMahon1, Jenna Dvorsky1
1Department of Orthopaedic Surgery, University of Pittsburgh, Pittsburgh, Pennsylvania, USA.

Background:
Massive rotator cuff tears (MRCTs) involving the rotator cable are associated with increased tendon retraction, fatty infiltration, and high retear rates after repair. Biceps anterior cable reconstruction (ACR) is a surgical technique that augments rotator cuff repair by reconstructing the anterior cable with the long head of the biceps tendon (LHBT), improving greater tuberosity coverage and biomechanical stability.
Indications:
Biceps ACR is indicated for full-thickness MRCTs with anterior cable involvement in patients with an intact LHBT and no advanced glenohumeral arthritis. Risk factors for repair failure, including the full-thickness retracted pattern of a tear, patient age, and activity level, are considered when deciding to add a concomitant ACR.
Technique Description:
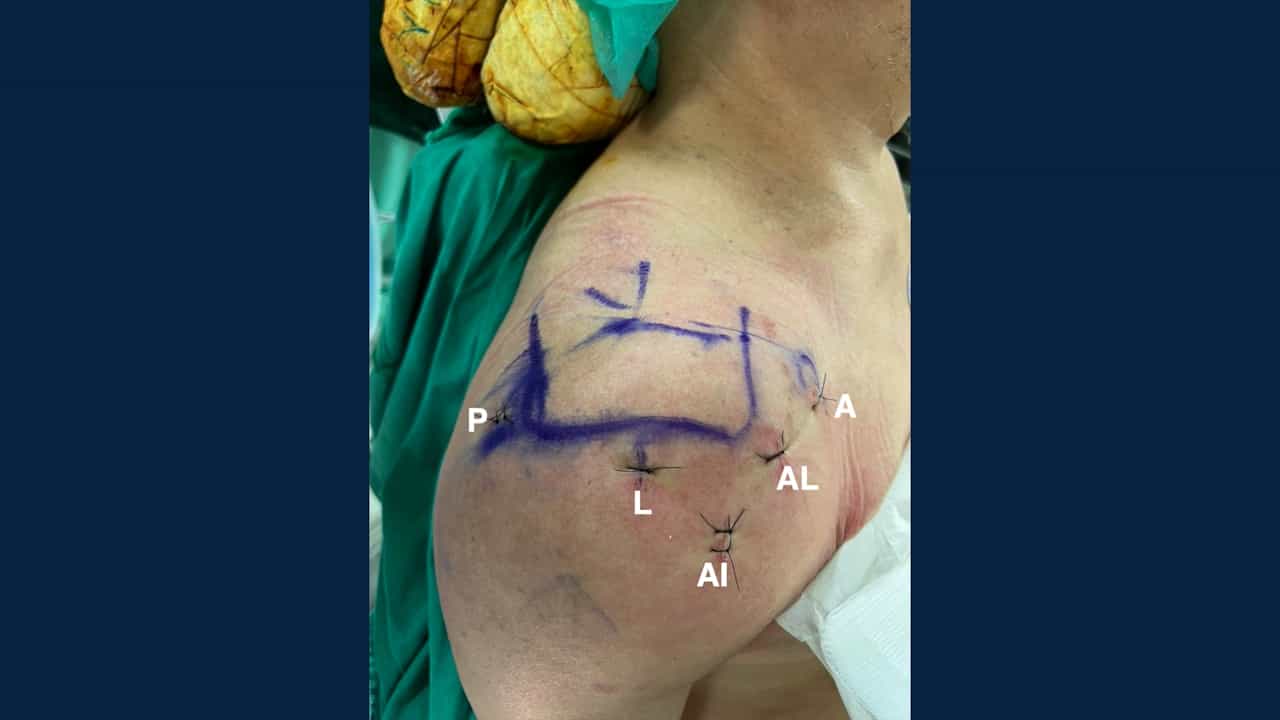
A knotless repair stitch from an anchor at the anteromedial footprint of the greater tuberosity is passed circumferentially around the proximal LHBT. The biceps is left attached to the glenoid, and the repair stitch is tightened, which reduces the biceps tendon to the anterior aspect of the greater tuberosity. This allows the biceps tendon to slide and find its optimal tension, tenodeses the biceps tendon to the greater tuberosity, and reconstructs the anterior cable. This provides greater tuberosity coverage and reduces the tear distance. The remaining sutures from the anteromedial anchor can be passed through the rotator cuff. The remaining rotator cuff can be repaired using a variety of standard techniques. Simple side-to-side stitches can be placed in the biceps tendon and rotator cuff as needed.
Results:
Biceps ACR improves greater tuberosity coverage and enhances biomechanical stability by decreasing superior translation and subacromial contact pressure. Clinical studies have demonstrated excellent patient-reported outcomes and lower retear rates when biceps ACR is added to arthroscopic rotator cuff repair.
Discussion/Conclusion:
Biceps ACR is a viable option for MRCTs with anterior cable involvement and a high risk for failure.
Patient Consent Disclosure Statement:
The author(s) attests that consent has been obtained from any patient(s) appearing in this publication. If the individual may be identifiable, the author(s) has included a statement of release or other written form of approval from the patient(s) with this submission for publication.
More Related Videos
Related Concept Videos
 01:29
Cable: Problem Solving
 01:13
Cable Subjected to Its Own Weight
A generalized loading function is employed to analyze a cable subjected to its own weight. This function considers the force acting along the cable's arc length rather than its projected length, providing a more accurate...
 01:31
Energy Stored In A Coaxial Cable
In the simplest form, a coaxial cable can be represented by two long hollow concentric cylinders in which the current flows in opposite directions. The magnetic field inside and outside the coaxial cable is determined by using Ampère's law. The magnetic field inside...
 01:28
Cable Subjected to Concentrated Loads
 01:24
Cable Subjected to a Distributed Load
 01:30
Kinematic Equations for Rotation
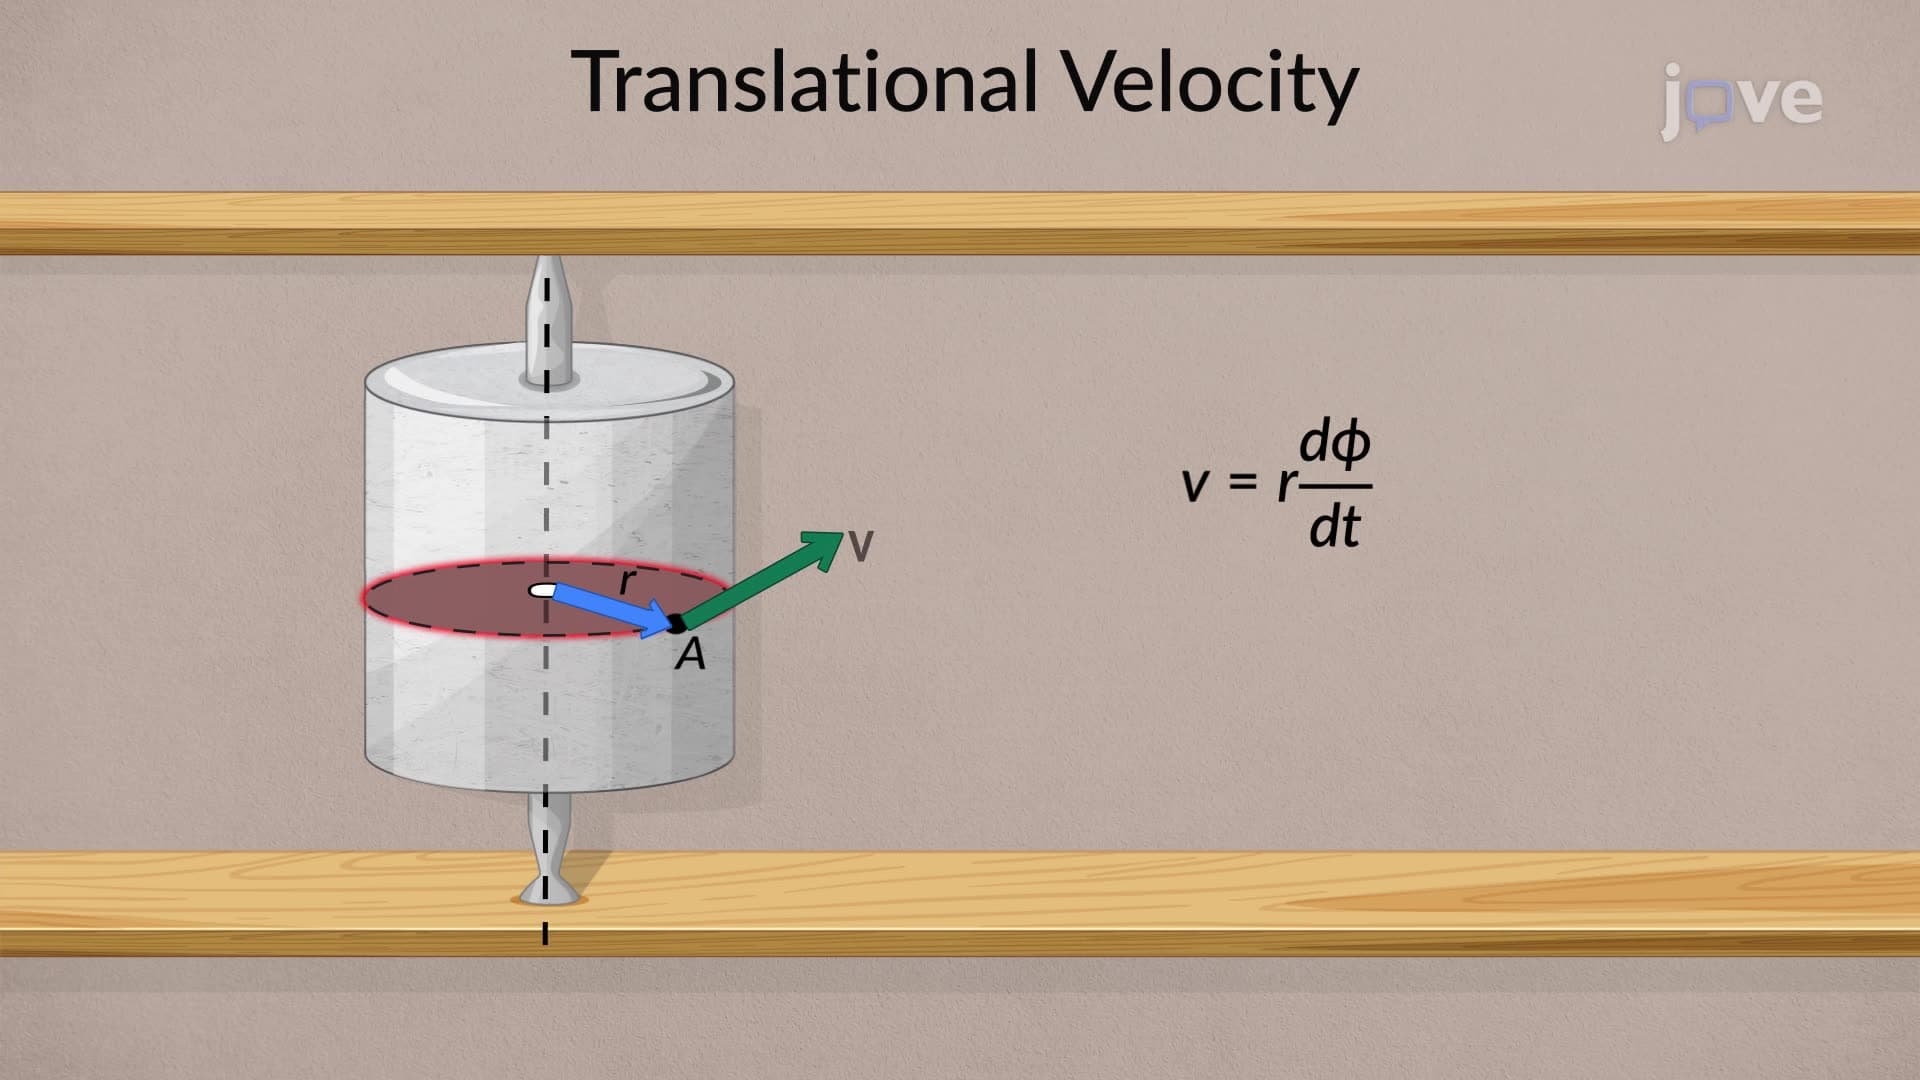
For instance, imagine a point A on a rigid body engaged in circular motion. The translational velocity of this particular point can be calculated by taking the time derivatives of the displacement equation, which essentially measures the...