Related Experiment Video
Updated: Feb 12, 2026
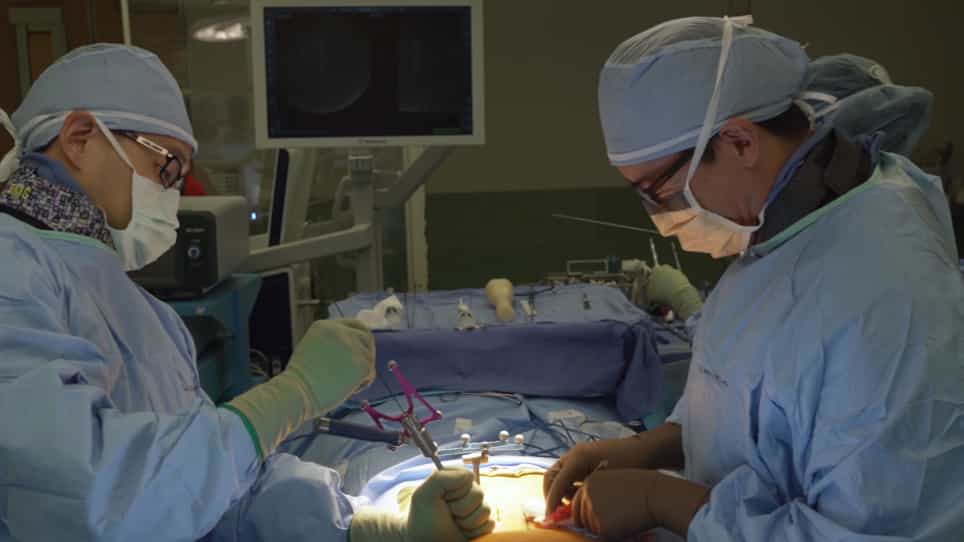

Cone Beam Intraoperative Computed Tomography-based Image Guidance for Minimally Invasive Transforaminal Interbody Fusion
Published on: August 6, 2019
The role of IVUS in BEVAR as additional intraoperative tool: procedure guidance and quality control imaging
Michele Piazza1, Carmine Spiezia2, Francesco Squizzato2
1Division of Vascular and Endovascular Surgery, Department of Cardiac, Thoracic, Vascular Sciences and Public Health, University of Padua, Padua, Italy - mikpia79@hotmail.com.

Background:
Intravascular ultrasound (IVUS) is a catheter-based imaging technique that utilizes high-frequency sound waves to produce real-time, cross-sectional images of the vessel lumen. IVUS is a well-known endovascular imaging tool for peripheral and aortic procedures, with potential benefit also during branched endovascular aortic repair (BEVAR).
Methods:
We conducted a single-center retrospective observational study, including 47 patients undergoing elective BEVAR procedure from 2020 to 2024. Exclusion criteria were acute dissection, frank rupture. Two groups were compared: an IVUS-guided group, with routine IVUS for BEVAR procedure guidance, as intraoperative tool for post - implant bridging stent quality control; a NON-IVUS-guided group underwent standard BEVAR procedures without IVUS use. Primary endpoints are technical success of IVUS assessment for each target vessel, incidence of intraoperative branch instability detected by IVUS, and absence of IVUS-related adverse events. Secondary endpoints are procedural metrics, rate of intraoperative revisions prompted by IVUS findings, and postoperative outcomes such as branch instability requiring reintervention, as confirmed by follow-up imaging.
Results:
There were 27 BEVAR (nine type I-III, 11 type IV, seven post-dissection TAAAs) in IVUS group and 20 (seven type I-III, eight type IV, five post-dissection TAAAs) in NON-IVUS group. Overall, there were no differences in operative time (median procedure time 310 vs. 318 min; P=0.89) and Xray exposure (47.3 vs. 47.5 mGy, P=0.99) between the two groups. There was a significant reduction of contrast volume for the main graft deployment phase (P=0.021) and X-ray reduction during the bridging stent phase (P=0.012); 76 TVVs were treated in group NON-IVUS group and over 103 bridged target vessels in IVUS group, the number of branch instability as kinking or compression identified with IVUS and not with angiography was 22%; this required additional unplanned reinforcement with stent reinforcement in 16% of the cases.
Conclusions:
This study suggests that IVUS is a safe and potentially valuable adjunctive imaging technology for intra-operative detection of TVV instability and highly sensitive in the identification of morphological defects, reducing Xray exposure or contrast volume for selected steps of the procedure. Long term investigations on larger cohorts are required to validate these promising results.

Related Concept Videos
 01:05
Quality Control
Quality control helps track data, visualize trends, and identify variations, making it easier to detect deviations that may affect the accuracy of an analysis. One way to do this is by generating a quality control chart, which...
 01:27
Conjugate Addition (1,4-Addition) vs Direct Addition (1,2-Addition)
Conjugate addition results in a thermodynamically stable product. The reaction retains the stronger C=O bond at the expense of the weaker C=C π bond. The process is slow as the β carbon is less electrophilic than the carbonyl carbon.
Direct addition products are...
 01:23
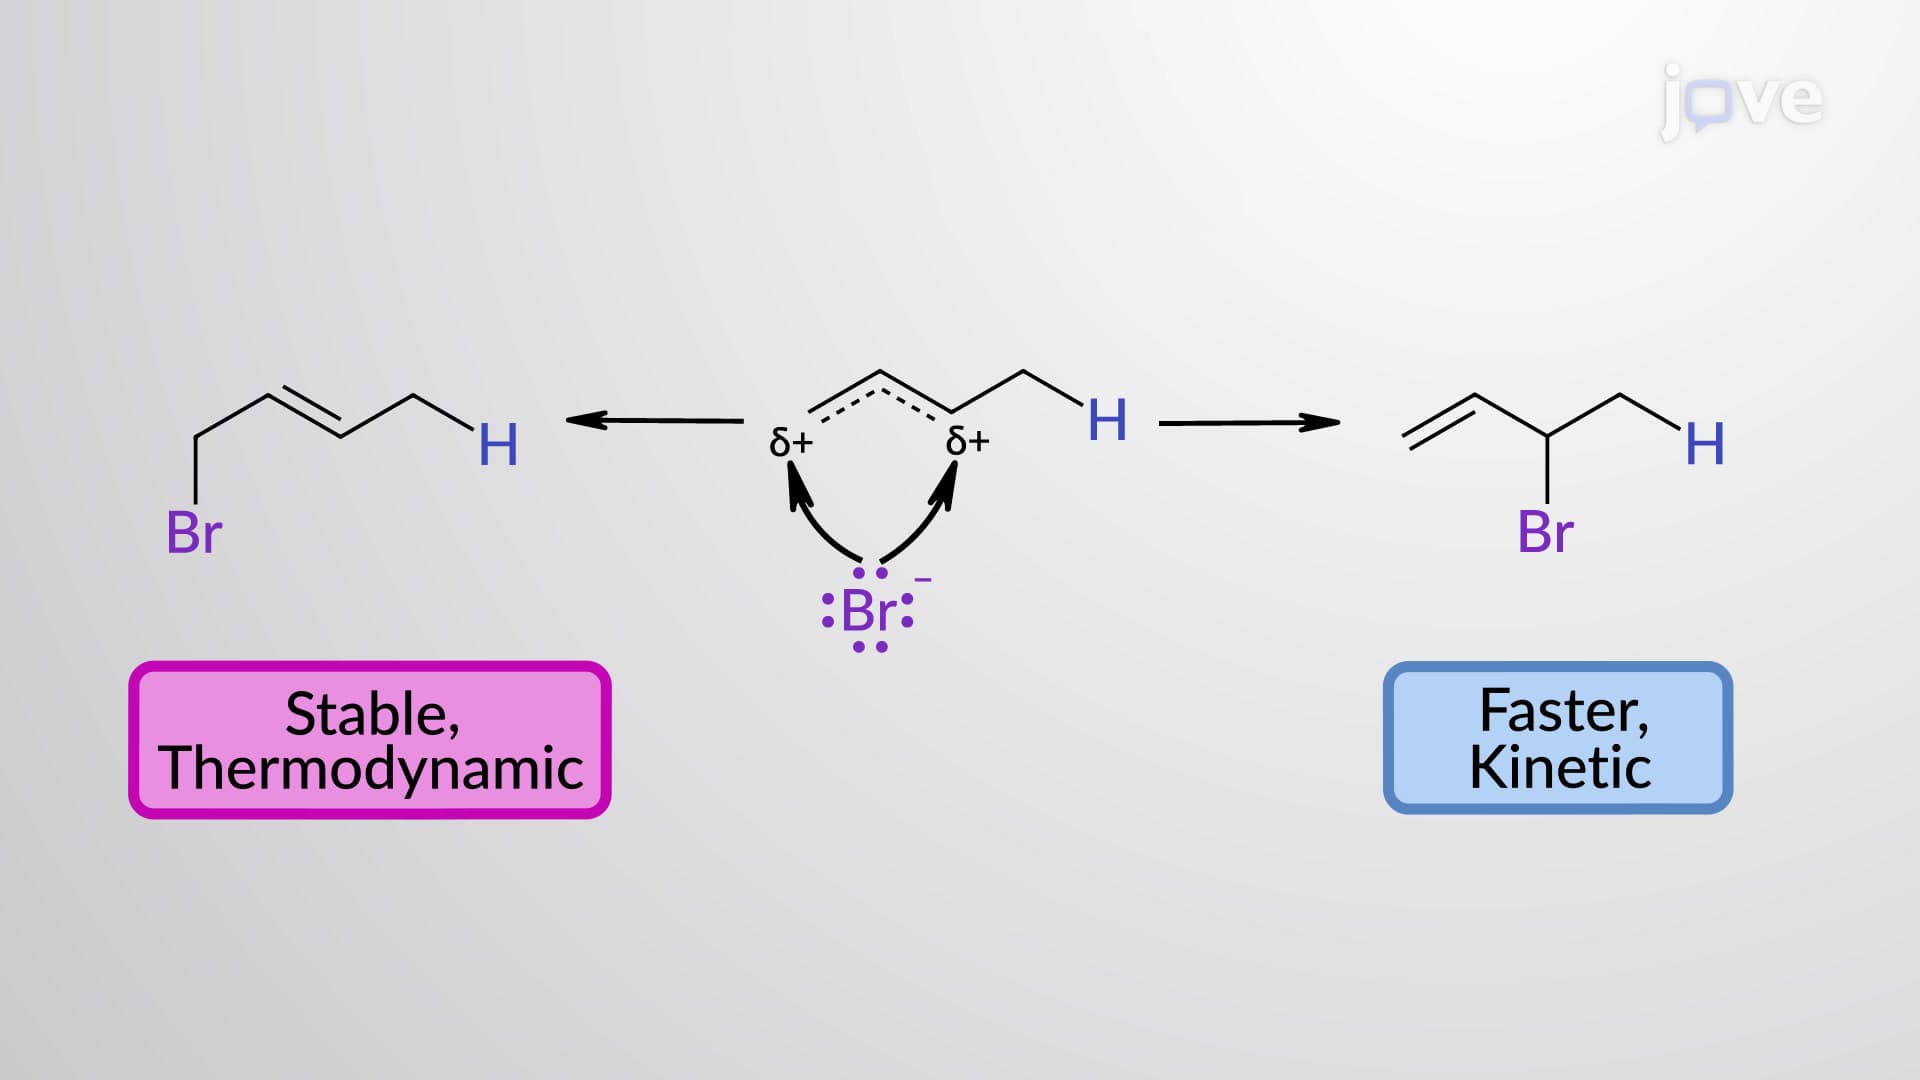
Electrophilic Addition of HX to 1,3-Butadiene: Thermodynamic vs Kinetic Control
 01:08
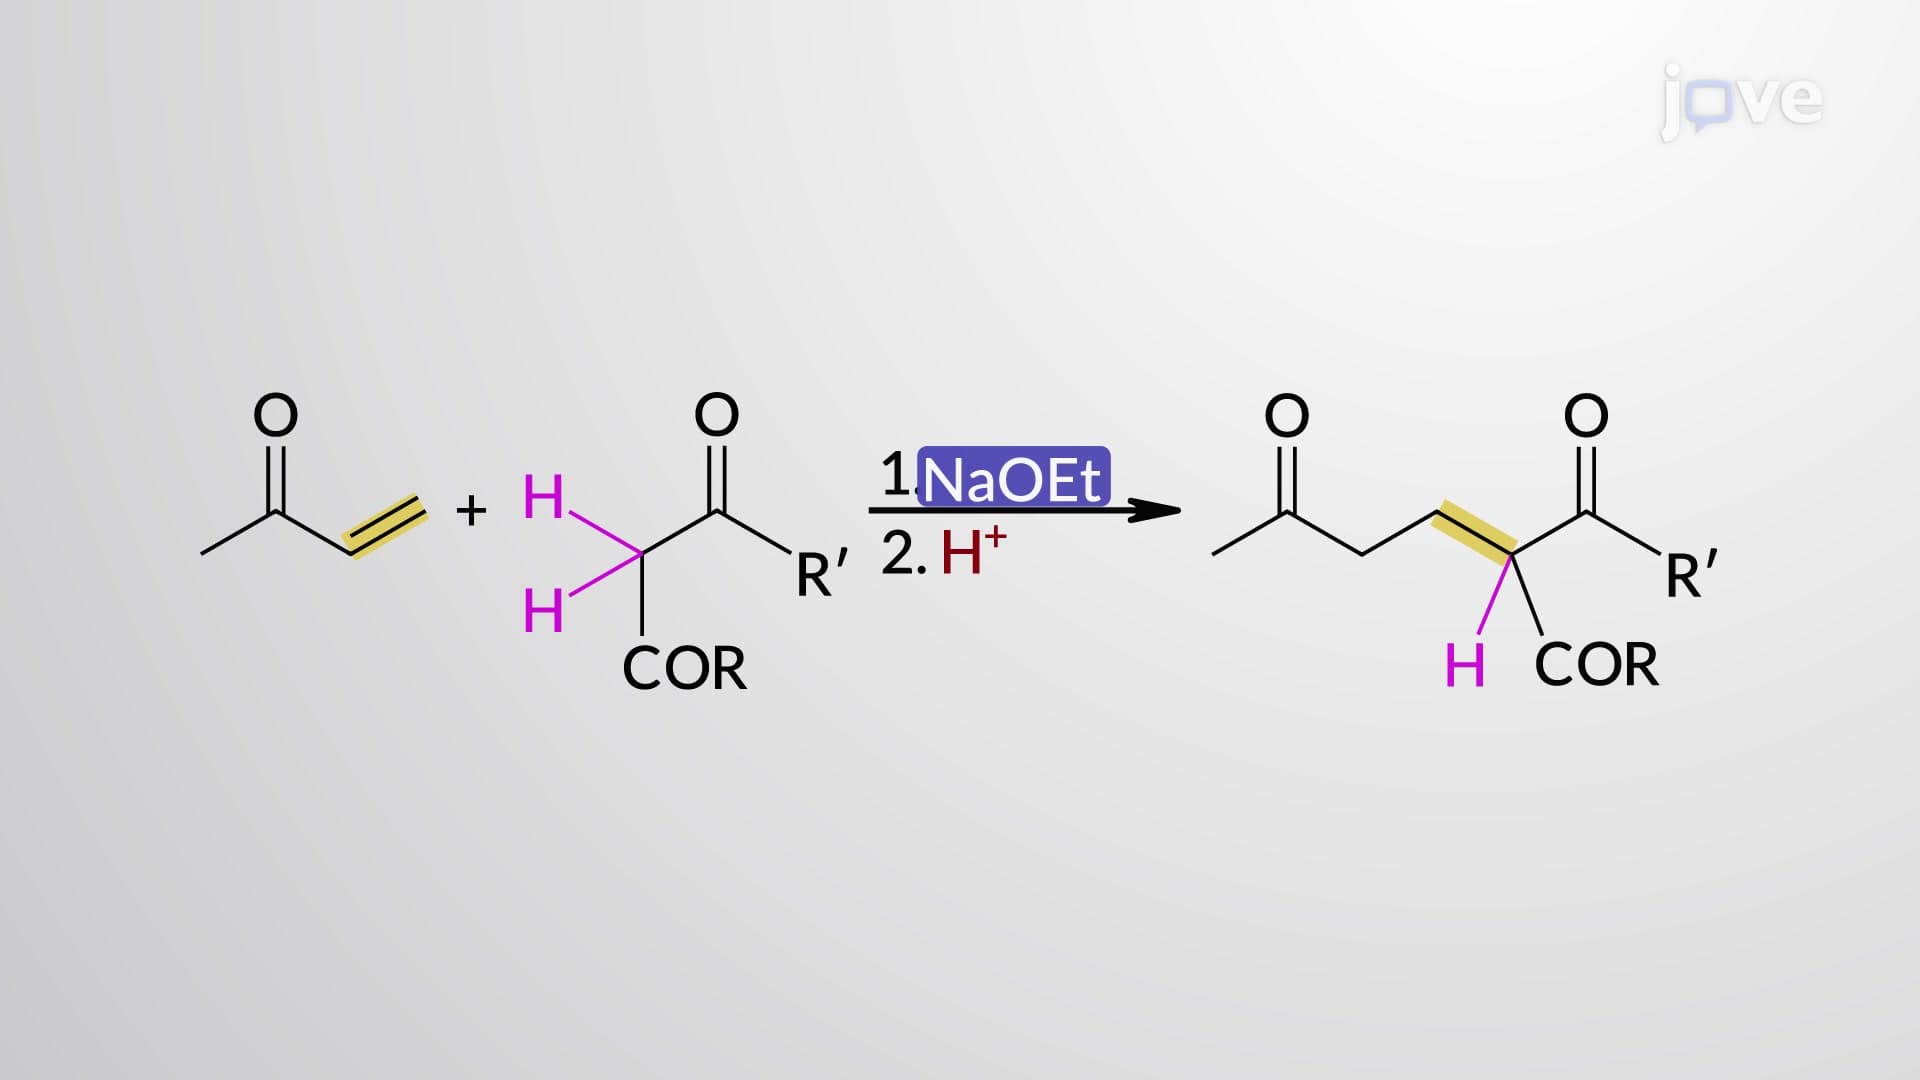
Conjugate Addition of Enolates: Michael Addition
 01:19
Quality Assurance
 01:19
Quality of Water