Related Experiment Video
Updated: Feb 17, 2026

Author Spotlight: A Reproductive Hysteroscopy Approach for Complete Endometrial Polyp Removal and Enhanced Endometrial Receptivity
Published on: August 2, 2024
Surgical Management of Early Pregnancy Loss by Operative Hysteroscopy Versus Vacuum Aspiration: Short-Term Outcomes
Maya Naor-Dovev1, Boris Beloshevski1, Matan Mor1
1Department of Obstetrics and Gynecology, Shamir Medical Center (Drs. Naor-Dovev, Beloshevski, Mor, Segal, Eisenberg, Smorgick), Zerifin, Israel; The Gray Faculty of Medicine, Tel Aviv University (Drs. Naor-Dovev, Beloshevski, Mor, Segal, Eisenberg, Smorgick), Tel Aviv, Israel.

Study Objective:
To evaluate the surgical management of early pregnancy loss by vacuum aspiration vs operative hysteroscopy in terms of feasibility, safety, and postoperative intrauterine adhesions (IUA) and retained products of conception (RPOC).
Design:
A nonblinded randomized-controlled trial.
Setting:
A university-affiliated department of obstetrics and gynecology.
Participants:
Study participation was offered to women with early (<10 gestational weeks) pregnancy loss.
Interventions:
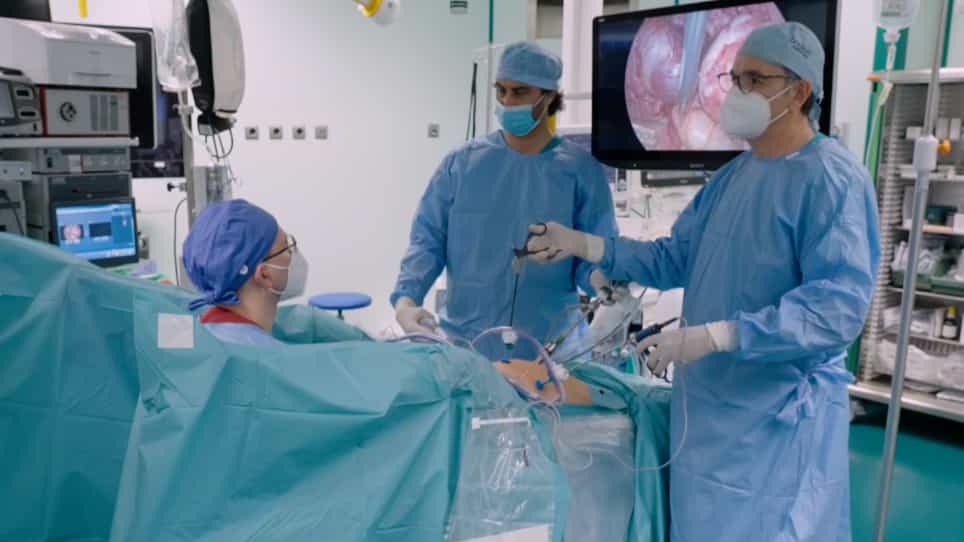
All procedures were performed under general anesthesia. Vacuum aspiration was performed by means of a plastic vacuum curette. Operative hysteroscopy was carried out by means of a tissue removal device (TruClear Elite hysteroscope mini, from Medtronic). The presence of IUA and RPOC was evaluated on 6-week postoperative hysteroscopy.
Results:
A total of 100 patients underwent either vacuum aspiration (n = 50) or operative hysteroscopy (n = 50). The mean gestational age was similar in both groups (8.7 ± 0.7 vs 8.8 ± 0.9 weeks, respectively, p = .6). The operating room time and the procedure time were significantly shorter in the vacuum aspiration group compared with the hysteroscopy group (27.5 ± 6.3 vs 36.3 ± 6.7 minutes and 7.2 ± 2.5 vs 9.8 ± 3.7 minutes, respectively, p < .01). Two cases in the hysteroscopy group were converted to vacuum aspiration due to reduced visibility. The intraoperative complications included 2 cases of laryngospasm in the hysteroscopy group. Follow-up hysteroscopy was available for 90 patients. The rates of postoperative IUA were significantly higher in the vacuum aspiration group (19/42 cases, 45.2%) compared with the operative hysteroscopy group (2/48 cases, 4.2%) (p < .01). Suspected RPOC were diagnosed in 5/42 (11.9%) of the vacuum aspiration patients and 11/48 (22.9%) of the hysteroscopy patients (p = .1), however, pathology-confirmed RPOC were found in 3/42 (7.1%) and 6/48 (12.5%) cases, respectively (p = .4).
Conclusion:
Operative hysteroscopy for the surgical management of early pregnancy loss may safely reduce the rates of postoperative IUA compared to vacuum aspiration.