Related Experiment Video
Updated: Feb 20, 2026
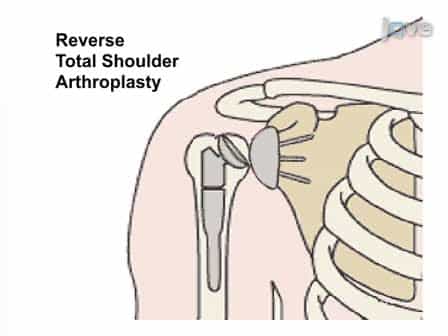

Reverse Total Shoulder Arthroplasty
Published on: July 5, 2011
[Surgical revision for instability following reverse shoulder arthroplasty]
Freya M Reeh1, Jan N Riesselmann2, Helmut Lill2
1Klinik für Orthopädie und Unfallchirurgie, DIAKOVERE Friederikenstift, Humboldtstr. 5, 30169, Hannover, Deutschland. freya.reeh@diakovere.de.

Objective:
In the case of unstable shoulder joint arthroplasty with recurrent dislocations, the aim of surgery is to restore increased soft tissue tension and, thus, joint stability.
Indications:
Indications include recurrent dislocations of the shoulder arthroplasty or instability of the arthroplasty in the case of obvious biomechanical weaknesses.
Contraindications:
In addition to general contraindications such as comorbidities that prevent surgery, surgery should initially be avoided in favor of infection remediation in the case of a critical soft tissue situation in the access area and an existing infection.
Surgical Technique:
After positioning in the modified beach-chair position with the upper body elevated by 30° and the arm moving freely on a separate table, the deltoid-pectoral approach is performed. The arthroplasty is exposed and luxated using a Homann hook. Increased lateralization can now be achieved by changing the baseplate and/or the glenosphere (+2 or +4 mm in each case). The "jumping distance" can also be increased by selecting a larger glenosphere. If the glenohumeral inclination angle of the inserted arthroplasty is 155°, the epiphysis is changed to an angle of 135° (if necessary, with the addition of a spacer) so that additional humeral (bifocal) lateralization is achieved. If the tuberosities can no longer be refixed or are even missing, a tuberculoplasty is performed using a cement construct attached laterally to the arthroplasty epiphysis. After a final stability check and radiological control, a Redon drain is inserted and the wound is closed.
Postoperative Management:
Immediately postoperatively, the patient is fitted with an abduction orthosis and the affected shoulder is immobilized for 2 weeks (formation of a neocapsule). This is followed by early functional active and passive therapy without weight-bearing on the arm for a total of 6 weeks.
Results:
For unstable arthroplasty, the surgical treatment described above can achieve a significant improvement in the stability of the arthroplasty with a low redislocation rate. Nevertheless, attention should be paid to biomechanically correct arthroplasty implantation with refixation of the tuberosity during the initial treatment.