Related Experiment Video
Updated: Feb 24, 2026
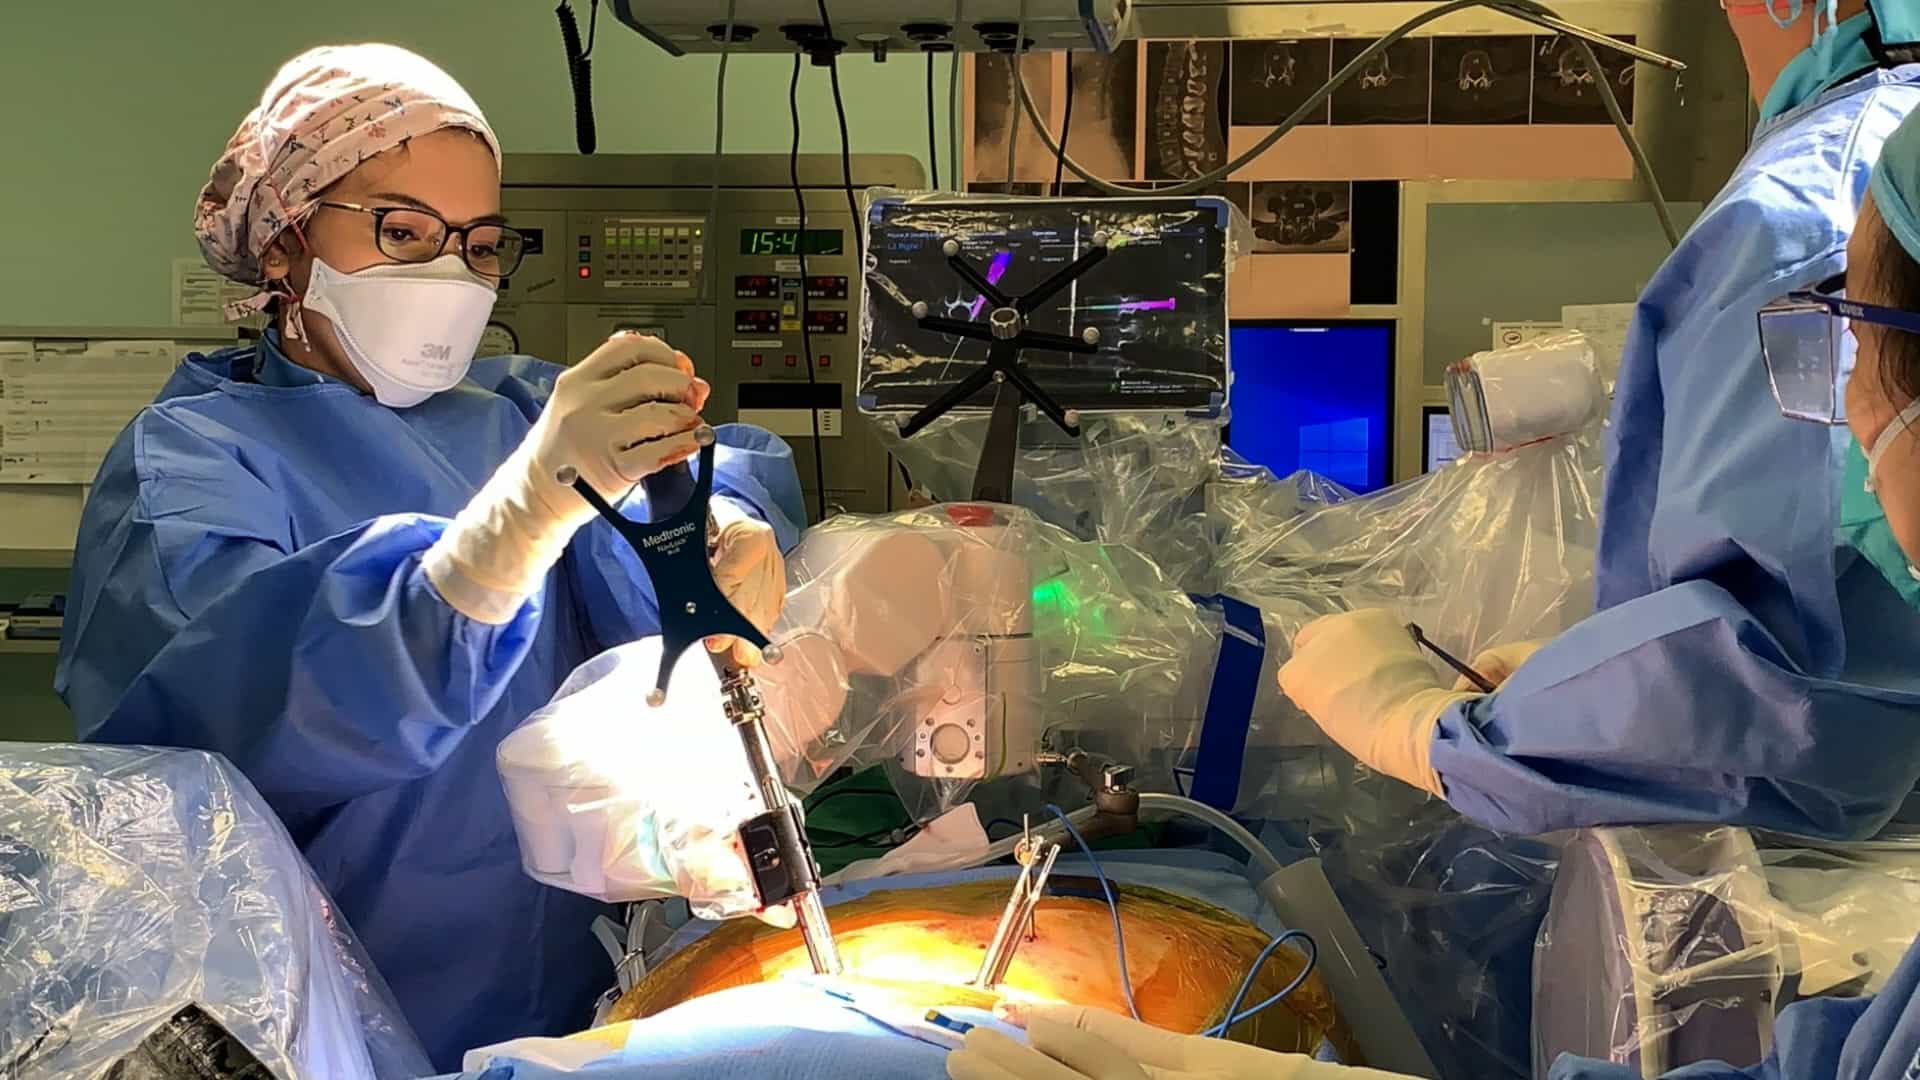

Multilevel Oblique Lumbar Interbody Fusion in Degenerative Lumbar Disc Disease with Instability
Published on: July 25, 2025
Interplay of Anatomy and Surgical Approach: A Comparative Review of Neurovascular Risk in Lateral and Oblique Lumbar
Ali Hamide1, Maryam Babar1, Aymen Arain1
1Medical School, Edward Via College of Osteopathic Medicine, Monroe, USA.

Abstract:
Degenerative conditions of the lumbar spine, such as disc herniation, spinal stenosis, and degenerative spondylolisthesis, represent a significant global health burden, frequently leading to chronic pain, neurological deficits, and diminished quality of life. Traditional open surgical approaches for lumbar interbody fusion, while effective, often involve extensive soft tissue dissection, which can lead to considerable blood loss, prolonged recovery times, and muscle damage. In response to these challenges, minimally invasive surgical (MIS) techniques have rapidly evolved, aiming to achieve comparable clinical outcomes with reduced iatrogenic tissue injury. Among the prominent MIS strategies for lumbar interbody fusion, two approaches have gained significant traction: lateral lumbar interbody fusion (LLIF), which encompasses techniques such as the direct lateral transpsoas interbody fusion (LTIF), and oblique lumbar interbody fusion (OLIF). Both techniques offer distinct advantages by providing access to the lumbar disc space from a corridor largely anterior to the posterior spinal elements, thereby minimizing disruption to the paraspinal musculature and bony structures. However, these benefits come with unique anatomical challenges. The success and safety of both LLIF/LTIF and OLIF are intrinsically linked to a precise understanding and careful navigation of the retroperitoneal space, particularly concerning the intricate lumbar plexus and associated major vascular structures. The proximity of vital nerves and vessels to the surgical corridors presents a significant risk of iatrogenic injury, which can lead to severe neurological deficits, vascular complications, and compromise patient outcomes. Furthermore, the inherent anatomical variability of the lumbar plexus and vascular structures among individuals adds another layer of complexity to these approaches, necessitating meticulous preoperative planning and intraoperative vigilance. This comparative review aims to synthesize the current literature on the distinct anatomical considerations and associated neurovascular risks encountered during lateral lumbar interbody fusion (LLIF/LTIF) and oblique lumbar interbody fusion (OLIF) approaches. By elucidating the specific anatomical challenges of each technique and the strategies employed to mitigate complications, we seek to provide a comprehensive overview for clinicians and researchers involved in the field of minimally invasive spinal surgery.