Related Experiment Video
Updated: Feb 25, 2026
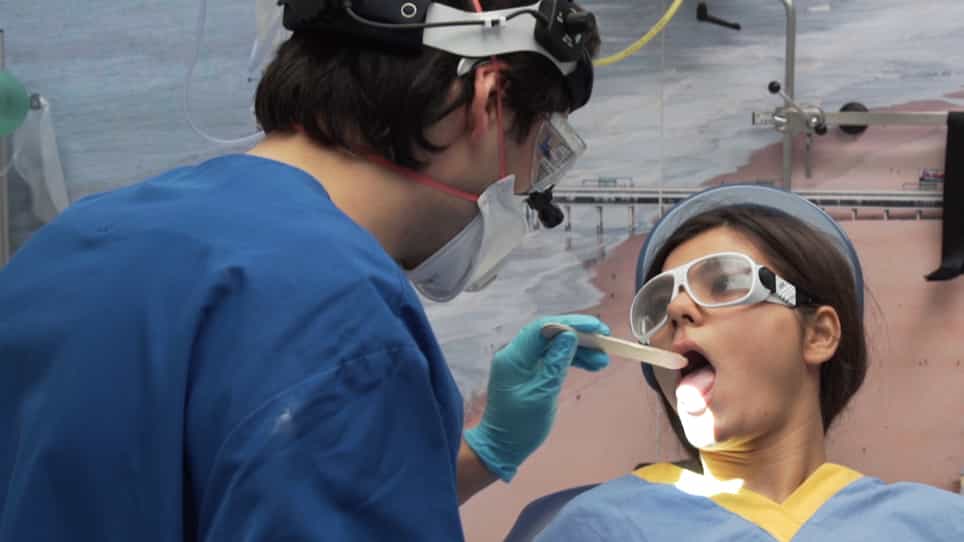
CO2-Lasertonsillotomy Under Local Anesthesia in Adults
Published on: November 6, 2019
Effect of Boyle-Davis mouth gag placement on intracranial pressure in children undergoing tonsillectomy: A
Kayacan Kaya1, Başak Akca1, Aysun Ankay Yilbas1
1Department of Anesthesiology and Reanimation, Hacettepe University Faculty of Medicine, Ankara, Turkey.

Insights
Pediatric adenotonsillectomy using a Boyle-Davis mouth gag may slightly increase intracranial pressure (ICP), indicated by optic nerve sheath diameter (ONSD). This transient ONSD rise is mainly due to positioning, not hypercapnia, suggesting careful patient positioning is crucial.
Area of Science:
- Pediatric Anesthesiology
- Neurocritical Care
- Ophthalmology
Background:
- Pediatric adenotonsillectomy commonly uses the Boyle-Davis mouth gag.
- Mouth gag placement may transiently elevate intracranial pressure (ICP).
- Optic nerve sheath diameter (ONSD) ultrasonography is a noninvasive ICP marker.
Purpose of the Study:
- To assess the impact of endotracheal intubation and Boyle-Davis mouth gag on ONSD in children.
- To evaluate changes in eyeball transverse diameter (ETD) and the ONSD/ETD ratio during the procedure.
Main Methods:
- Prospective observational study of 120 pediatric patients (2-18 years).
- Bilateral ONSD and ETD measurements at four time points: post-induction, post-intubation, post-gag placement, and post-gag removal.
- Statistical analysis included repeated-measures ANOVA and linear mixed-effects models, adjusting for end-tidal carbon dioxide (EtCO2) and mean arterial pressure (MAP).
Main Results:
- A statistically significant overall time effect was observed for ONSD and ONSD/ETD (P < .01).
- Mouth gag placement (T2) showed a significant increase in ONSD (+0.108 mm) and ONSD/ETD (+0.0033) compared to post-induction (T0), persisting after adjustment for EtCO2 and MAP.
- EtCO2 demonstrated a modest positive association with ONSD, while MAP was not significant. Heart rate and MAP varied significantly over time.
Conclusions:
- Boyle-Davis mouth gag suspension causes a small, transient increase in ONSD and ONSD/ETD, peaking during gag placement.
- The observed changes are primarily attributed to positioning and suspension forces, rather than hypercapnia.
- Findings underscore the importance of careful patient positioning and monitoring in pediatric patients undergoing adenotonsillectomy with mouth gag use.
Abstract:
Pediatric adenotonsillectomy frequently requires Boyle-Davis mouth gag placement, which may transiently increase intracranial pressure (ICP). Ultrasonographic optic nerve sheath diameter (ONSD) is a validated noninvasive marker of ICP. This study aims to investigate the impact of endotracheal intubation and Boyle-Davis mouth gag placement on ONSD, eyeball transverse diameter (ETD), and ratio of optic nerve sheath diameter to eyeball transverse diameter (ONSD/ETD) ratio in children. In this prospective observational study of 120 children (American Society of Anesthesiologists I-II, 2-18 years), bilateral ONSD and ETD were measured at post‑induction (T0), post‑intubation (T1), post‑gag placement (T2), and post‑gag removal (T3). Unadjusted profiles used repeated-measures ANOVA. Adjusted analyses used linear mixed-effects models with time and random intercept for subject; end-tidal carbon dioxide (EtCO2) and mean arterial pressure (MAP) were entered as time-varying covariates. Means (±standard deviation) for ONSD were 5.74 ± 0.46 (T0), 5.79 ± 0.46 (T1), 5.86 ± 0.44 (T2), 5.77 ± 0.48 (T3); for ONSD/ETD: 0.251 ± 0.021, 0.252 ± 0.020, 0.255 ± 0.020, 0.249 ± 0.021. The overall time effect was significant for both outcomes (P < .01). In adjusted models, T2 versus T0 remained higher for ONSD (+0.108 mm; 95% confidence interval (CI): 0.046-0.170; P < .001) and ONSD/ETD (+0.0033; 95% CI: 0.0003-0.0063; P = .03), whereas MAP was not significant and EtCO2 showed a modest positive association with both outcomes (ONSD: +0.007 mm/mm Hg; 95% CI: 0.002-0.012; P < .01). Heart rate and MAP varied over time (both P < .001), EtCO2 rose early and declined by T3 (P < .001). No neurologic events occurred. Mouth-gag suspension produces a small, transient rise in ONSD and ONSD/ETD that peaks at T2 and recedes after removal. Effects persisted after adjustment for EtCO2 and MAP, primarily suggesting contributions from positioning and suspension rather than hypercapnia. Findings support prudent positioning and monitoring in at‑risk children.
More Related Videos


Related Concept Videos
 01:25
Suctioning the Oropharyngeal Airway
After assembling the equipment, the nurse should practice hand hygiene and don appropriate PPE according to infection control guidelines to avoid the...
 01:22
Cardiopulmonary Resuscitation II: ACLS Airway Management
 01:29
Suctioning the Nasopharyngeal Airway
Equipment Required
 01:26
Tonsillitis II: Management