Related Experiment Video
Updated: Aug 1, 2026
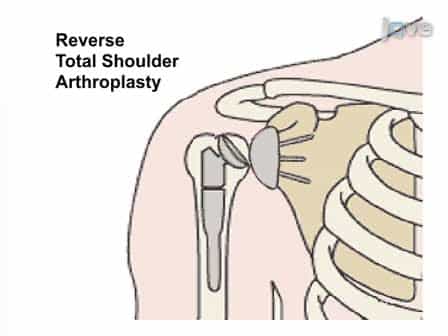
Reverse Total Shoulder Arthroplasty
Published on: July 5, 2011
Shoulder arthroplasty following a previous Latarjet procedure
Matthias Biner1, Bettina Hochreiter1, Philipp Kriechling1
1Department of Orthopedics, Balgrist University Hospital, University of Zurich, Zurich, Switzerland.

Background:
Shoulder arthroplasty in patients with prior Latarjet procedures is technically challenging due to altered anatomy and soft tissue changes. This study aimed to compare clinical outcome measures, complications, and implant survival in primary hemiarthroplasty (HA), anatomic total shoulder arthroplasty (aTSA), and reverse total shoulder arthroplasty (rTSA) in patients with previous Latarjet surgery vs. matched cohorts.
Methods:
A retrospective analysis was conducted including a total of 69 patients, comparing 23 post-Latarjet patients (4 HA, 6 aTSA, 13 rTSA) with a 2:1 matched control group. Outcomes included range of motion, functional scores (absolute and relative Constant-Murley Score [aCS and rCS], Subjective Shoulder Value), complications, revisions, and radiographic findings. Kaplan-Meier survival analysis evaluated reintervention-free survival.
Results:
Demographics were not significantly different between the post-Latarjet and matched cohorts. Patients who underwent HA following a Latarjet demonstrated significantly less improvement in flexion (Δ -10° vs. 50°), abduction (Δ 5° vs. 70°), and external rotation (Δ -15° vs. 30°) compared to their matched controls (all P < .05). Moreover, the improvement in aCS was significantly lower in the post-Latarjet HA group (13.5 vs. 36 points; P = .042). In the rTSA subgroup, flexion improvement was also significantly reduced in post-Latarjet patients compared to the matched cohort (Δ -10° vs. 37.5°; P = .018). Other functional outcomes (aCS, rCS, Subjective Shoulder Value) were comparable across groups. Complication rates were 75% (HA), 33.3% (aTSA), and 15.4% (rTSA) in the post-Latarjet group, compared to 25% (HA), 33.3% (aTSA), and 11.5% (rTSA) in the matched cohorts. Reintervention-free survival at 60 months was lowest for HA (25%), intermediate for aTSA (66.7%), and highest for rTSA (84.6%), with rTSA showing significantly better survival than HA (P = .009).
Conclusion:
While clinical outcomes were largely comparable between post-Latarjet patients and matched cohorts, rTSA may offer the most reliable results with lower complication and revision rates than aTSA and HA. It appears to be the preferred option in this complex setting, although post-Latarjet patients showed reduced range of motion.