Related Experiment Video
Updated: Feb 28, 2026
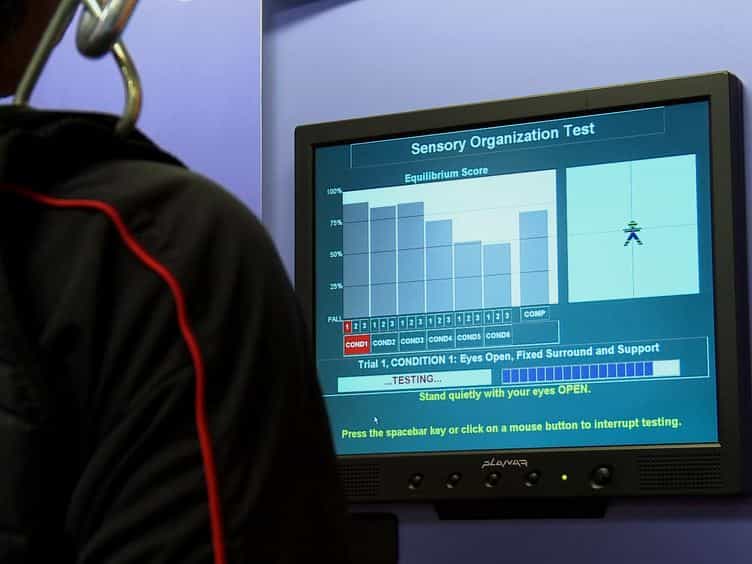

Computerized Dynamic Posturography for Postural Control Assessment in Patients with Intermittent Claudication
Published on: December 11, 2013
Mortality and patient-centered outcomes are worse in patients with dementia undergoing revascularization for
Khanjan B Shah1, Dan Neal2, Salvatore T Scali3
1Division of Cardiovascular Medicine, University of Florida College of Medicine, Gainesville, FL.

Insights
Patients with Alzheimer's Disease and Related Dementias (ADRD) and claudication face higher mortality risks. Following revascularization, ADRD patients experience worse outcomes, including increased readmissions and need for higher care levels.
Area of Science:
- Vascular Surgery
- Neurology
- Geriatrics
Background:
- Claudication and Alzheimer's Disease and Related Dementias (ADRD) frequently coexist due to shared risk factors.
- While conservative treatment is common for claudication, revascularization is an option for severe symptoms.
- Limited data exists on mortality and patient-centered outcomes for individuals with both ADRD and claudication.
Purpose of the Study:
- To evaluate mortality and patient-centered outcomes in a large cohort of patients with claudication.
- To stratify outcomes based on treatment type (medical, endovascular, or open revascularization).
- To compare outcomes between patients with and without ADRD.
Main Methods:
- A large cohort of 297,060 patients treated for claudication between 2017 and 2024 was analyzed.
- Patients were categorized into three treatment groups: medical therapy, endovascular revascularization, or open revascularization.
- Cox proportional hazard models assessed the impact of ADRD on mortality; inpatient complications, readmissions, and discharge disposition were analyzed for revascularization patients.
Main Results:
- 9.3% of claudication patients had ADRD, were older, and more likely female.
- Patients with ADRD had higher all-cause mortality (HR 1.1).
- Among revascularization patients, ADRD was associated with similar inpatient complications but higher 90-day readmissions (OR 1.9) and increased discharge to higher care levels (OR 2.1).
Conclusions:
- ADRD is linked to increased mortality risk in claudication patients.
- For claudication revascularization, ADRD patients face poorer outcomes, including higher readmissions and greater need for post-discharge care.
- Findings emphasize the need for shared decision-making between patients, families, and physicians regarding claudication treatment in ADRD patients.
Objective:
The aims of this study were to describe mortality and patient-centered outcomes in a large cohort of patients with claudication and Alzheimer's disease and related dementias (ADRD) as stratified by treatment type. Claudication and ADRD often coexist owing to shared risk factors. Treatment for claudication is primarily conservative, although revascularization can be considered with quality-of-life-limiting leg symptoms. Mortality risk and patient-centered outcomes in patients with ADRD and claudication have not been described.
Methods:
Patients in the OneFlorida+ dataset with and without ADRD treated for claudication from January 1, 2017, to January 31, 2024, were included. The total cohort was separated into three treatment groups: medical therapy, endovascular revascularization, or open revascularization. Cox proportional hazard modeling was used for the impact of ADRD on all-cause mortality in the total cohort. Among patients undergoing endovascular or open revascularization, clinical outcomes were inpatient complications and 90-day readmissions, and patient-centered outcomes were discharge to higher level of care and discharge home.
Results:
The total cohort for claudication was 297,060 patients and included 27,621 patients (9.3%) with a diagnosis of ADRD. Patients with ADRD were more likely to be older (78.6 years vs 66.1 years; P < .001) and women (54.9% vs 48.9%; P < .001). For the total cohort, all-cause mortality was higher in patients with ADRD regardless of treatment type (hazard ratio, 1.1; 95% confidence interval [CI], 1.05-1.12). For patients who underwent revascularization, patients with ADRD had similar rates of inpatient complications compared with patients without ADRD (odds ratio [OR], 0.85; 95% CI, 0.72-1.01), but had higher rates of 90-day readmissions (OR, 1.9; 95% CI, 1.60-2.15). Patients with ADRD undergoing revascularization were more likely to be discharged to a higher level of care (OR, 2.1; 95% CI, 1.67-2.73) and less likely to be discharged home (OR, 0.54; 95% CI, 0.46-0.64).
Conclusions:
In a large cohort of patients with claudication, patients with ADRD demonstrate a higher risk of all-cause mortality. Among patients who undergo revascularization for claudication, patients with ADRD have worse readmission rates and are more often discharged to higher levels of care, regardless of revascularization strategy. These data should be used by patients, their families, and physicians to facilitate shared decision--making conversations before claudication treatment.
More Related Videos
 07:25
Predicting Amputation using Local Circulating Mononuclear Progenitor Cells in Angioplasty-treated Patients with Critical Limb Ischemia
Published on: September 22, 2020
 13:48
Reduction of Radiation Exposure during Endovascular Treatment of Peripheral Arterial Disease Combining Fiber Optic RealShape Technology and Intravascular Ultrasound
Published on: April 21, 2023
Related Concept Videos
 01:27
Peripheral Artery Disease III: Interprofessional Care
 01:21
Peripheral Arterial Disease II: Clinical Manifestations and Diagnostic Evaluation
 01:26
Peripheral Artery Disease IV: Nursing Management
 01:23
Peripheral Artery Disease V: Postoperative Nursing Management
 01:30
Peripheral Artery Disease I: Introduction
 01:23
Atherosclerosis IV: Nursing Management