Related Experiment Video
Updated: Feb 28, 2026
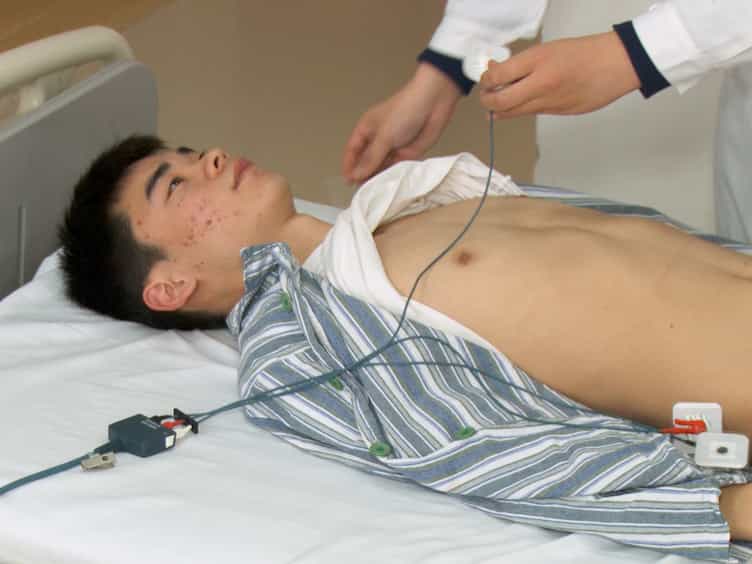

Measuring the Carotid to Femoral Pulse Wave Velocity Cf-PWV to Evaluate Arterial Stiffness
Published on: May 3, 2018
Association of Arterial Velocity Pulse Index and Arterial Pressure-Volume Index with Central Arterial Stiffness and
Hiroto Hommo1, Takuya Sugawara1, Hikaru Ueno1
1Department of Cardiology, Yokohama City University, Yokohama 236-0004, Japan.

Abstract:
Background: The Arterial Velocity Pulse Index (AVI) and Arterial Pressure-Volume Index (API) are novel non-invasive indices of arterial stiffness derived from cuff-oscillometric measurements. Previous studies have shown that elevated AVI and API are associated with the severity of coronary artery disease and the ability to predict future cardiovascular events. However, the hemodynamic and echocardiographic characteristics of patients with concomitantly high AVI and API remain unclear. Methods: We retrospectively analyzed 112 consecutive cardiovascular outpatients (mean age 69.1 ± 12.2 years, 64.3% male) seen between January and April 2019 at Yokohama City University Hospital. The AVI and API were measured using a multifunctional sphygmomanometer (PASESA AVE1500, Shisei Datum, Japan) and averaged over a maximum of three measurements. Patients were classified into four groups according to previously established cutoff values (AVI ≥ 27, API ≥ 32). Central arterial pulse wave parameters were assessed using SphygmoCor XCEL (AtCor Medical, Sydney, Australia), and echocardiographic parameters were obtained according to standard protocols. Intergroup differences were analyzed using the Kruskal-Wallis test with Steel-Dwass post hoc comparisons. Results: Compared with the low-risk group (low AVI/low API), the high-risk group (high AVI/high API) had significantly higher brachial systolic BP (139.2 [132.8-149] vs. 128 [120-136.7] mmHg, p = 0.0011), central systolic BP (127.5 [122.3-139] vs. 117.7 [110.3-123.7] mmHg, p = 0.0018), and central pulse pressure (56.2 [51.4-60.3] vs. 37.7 [32-43] mmHg, p < 0.001). The forward and reflected wave amplitudes were significantly greater, with prolonged ejection duration and aortic T2 time. The Buckberg subendocardial viability ratio was significantly lower in the high-risk group (129.5 [119.7-145.2] vs. 148.3 [130-168.3], p = 0.040). Echocardiography revealed reduced e' velocity (5 [4.1-5.8] vs. 6.7 [5.2-8] cm/s, p = 0.035) and increased E/e' (13.2 [11.1-15.1] vs. 9.7 [7.9-11.3], p = 0.026) in the high-risk group, suggesting the presence of impaired diastolic function without reduced LVEF. Conclusions: Patients with high AVI and API exhibited greater central and peripheral arterial stiffness, higher systolic and pulse pressures, and impaired diastolic function compared with those with low values. These findings support the use of a cardiovascular pathophysiological model in which elevated AVI/API identify individuals at increased risk of progression to heart failure and ischemic heart disease.

Related Concept Videos
 01:15
Assessment of blood pressure in brachial artery(one-step method)
Prepare for the Procedure:
 01:23
Assessment of blood pressure in brachial artery(two-step method)
 01:21
Peripheral Arterial Disease II: Clinical Manifestations and Diagnostic Evaluation
 01:16
Pulse
The pulse serves as a clinical...
 01:10
Pre-Procedural Guidelines for Assessing Blood Pressure
 01:11
Assessing Blood pressure in the Leg
Preparation: