Related Experiment Video
Updated: Mar 10, 2026

Antimicrobial Synergy Testing by the Inkjet Printer-assisted Automated Checkerboard Array and the Manual Time-kill Method
Published on: April 18, 2019
Co-Administration Dosing of Ceftazidime-Avibactam and Aztreonam in Patients with Varying Renal Function for
Jatapat Hemapanpairoa1, Weerayuth Saelim1, Dhitiwat Changpradub2
1Division of Pharmaceutical Care, Faculty of Pharmacy, Silpakorn University, Nakhon Pathom, Thailand.

Background:
For infections caused by metallo-β-lactamase (MBL)-producing carbapenem-resistant Enterobacterales (CRE), ceftazidime-avibactam (CZA) alone is inactive because avibactam does not inhibit MBLs. Co-administration with aztreonam can restore activity but requires simultaneous delivery and harmonization of non-aligned renal dose adjustments. Pharmacodynamic (PD) targets for MBL producers may also differ from those for serine β-lactamase producers. This study aimed to define practical CZA plus aztreonam dosing regimens across renal function strata using Monte Carlo simulation.
Materials And Methods:
Pharmacokinetic (PK) parameters from infected patients receiving concomitant CZA plus aztreonam were modeled using a one-compartment structure with Chronic Kidney Disease Epidemiology Collaboration renal function as the key covariate. Monte Carlo simulations (n=5,000) evaluated concentration-time profiles during the first 24 hours and at steady state across renal strata. Both conventional and stringent PK/PD targets were assessed. Probability of target attainment (PTA) was estimated at clinically relevant minimal inhibitory concentrations (MICs) for ceftazidime and aztreonam and threshold concentrations (CT 2.5 and 4 mg/L) for avibactam. Joint PTA was defined as the probability of simultaneous attainment of aztreonam and avibactam targets. A ceftazidime Cmin >80 mg/L was applied as a neurotoxicity risk threshold.
Results:
Across simulations, aztreonam and ceftazidime achieved ≥90% PTA at MIC breakpoints under conventional targets. Avibactam achieved ≥90% PTA only at steady-state CT 2.5 mg/L and failed at 4 mg/L or under stringent targets, reflecting limited avibactam exposure relative to higher PD thresholds. In preserved renal function, q6h regimens provided higher joint PTA than q8h dosing, though neither achieved ≥90% joint PTA under stringent targets. Most regimens in reduced renal function (eGFR ≤90 mL/min) maintained ≥90% joint PTA under conventional targets, while attainment under stringent targets was limited. Neurotoxicity risk (Cmin >80 mg/L) remained low across renal strata.
Conclusion:
Co-administration of CZA and aztreonam using renal-adjusted doses provides a practical and effective strategy for MBL-CRE infections. This approach ensures high joint PTA attainment while maintaining a low neurotoxicity risk across all renal function strata.
Insights
Ceftazidime-avibactam (CZA) plus aztreonam effectively treats metallo-β-lactamase (MBL)-producing carbapenem-resistant Enterobacterales (CRE) infections. Renal-adjusted dosing ensures high target attainment and low neurotoxicity risk across all kidney function levels.
Area of Science:
- Pharmacology
- Infectious Diseases
- Clinical Pharmacy
Background:
- Metallo-β-lactamase (MBL)-producing carbapenem-resistant Enterobacterales (CRE) pose a significant treatment challenge.
- Ceftazidime-avibactam (CZA) is inactive against MBLs alone.
- Aztreonam co-administration restores CZA activity but complicates dosing due to non-aligned renal adjustments.
Purpose of the Study:
- To define practical dosing regimens for CZA plus aztreonam in patients with varying renal function.
- To optimize treatment strategies for MBL-CRE infections using Monte Carlo simulations.
- To assess pharmacokinetic/pharmacodynamic (PK/PD) targets for combination therapy.
Main Methods:
- Modeled pharmacokinetic parameters from patients receiving CZA and aztreonam.
- Utilized Monte Carlo simulations (n=5,000) to evaluate concentration-time profiles across renal strata.
- Assessed probability of target attainment (PTA) against relevant minimum inhibitory concentrations (MICs) and threshold concentrations (CT).
Main Results:
- Aztreonam and ceftazidime achieved high PTA at MIC breakpoints under conventional targets.
- Avibactam achieved high PTA only at steady-state CT 2.5 mg/L, failing at higher thresholds or stringent targets.
- Most renal-adjusted regimens maintained high joint PTA under conventional targets, with limited attainment under stringent targets; neurotoxicity risk remained low.
Conclusions:
- Renal-adjusted co-administration of CZA and aztreonam is a practical and effective strategy for MBL-CRE infections.
- This combination therapy achieves high joint PTA across all renal function strata.
- The approach maintains a low neurotoxicity risk, supporting its clinical utility.


Related Concept Videos
 01:25
Drug Dosing in Renal Diseases: Dose Adjustments Based on Drug Clearance and Elimination Rate Constant
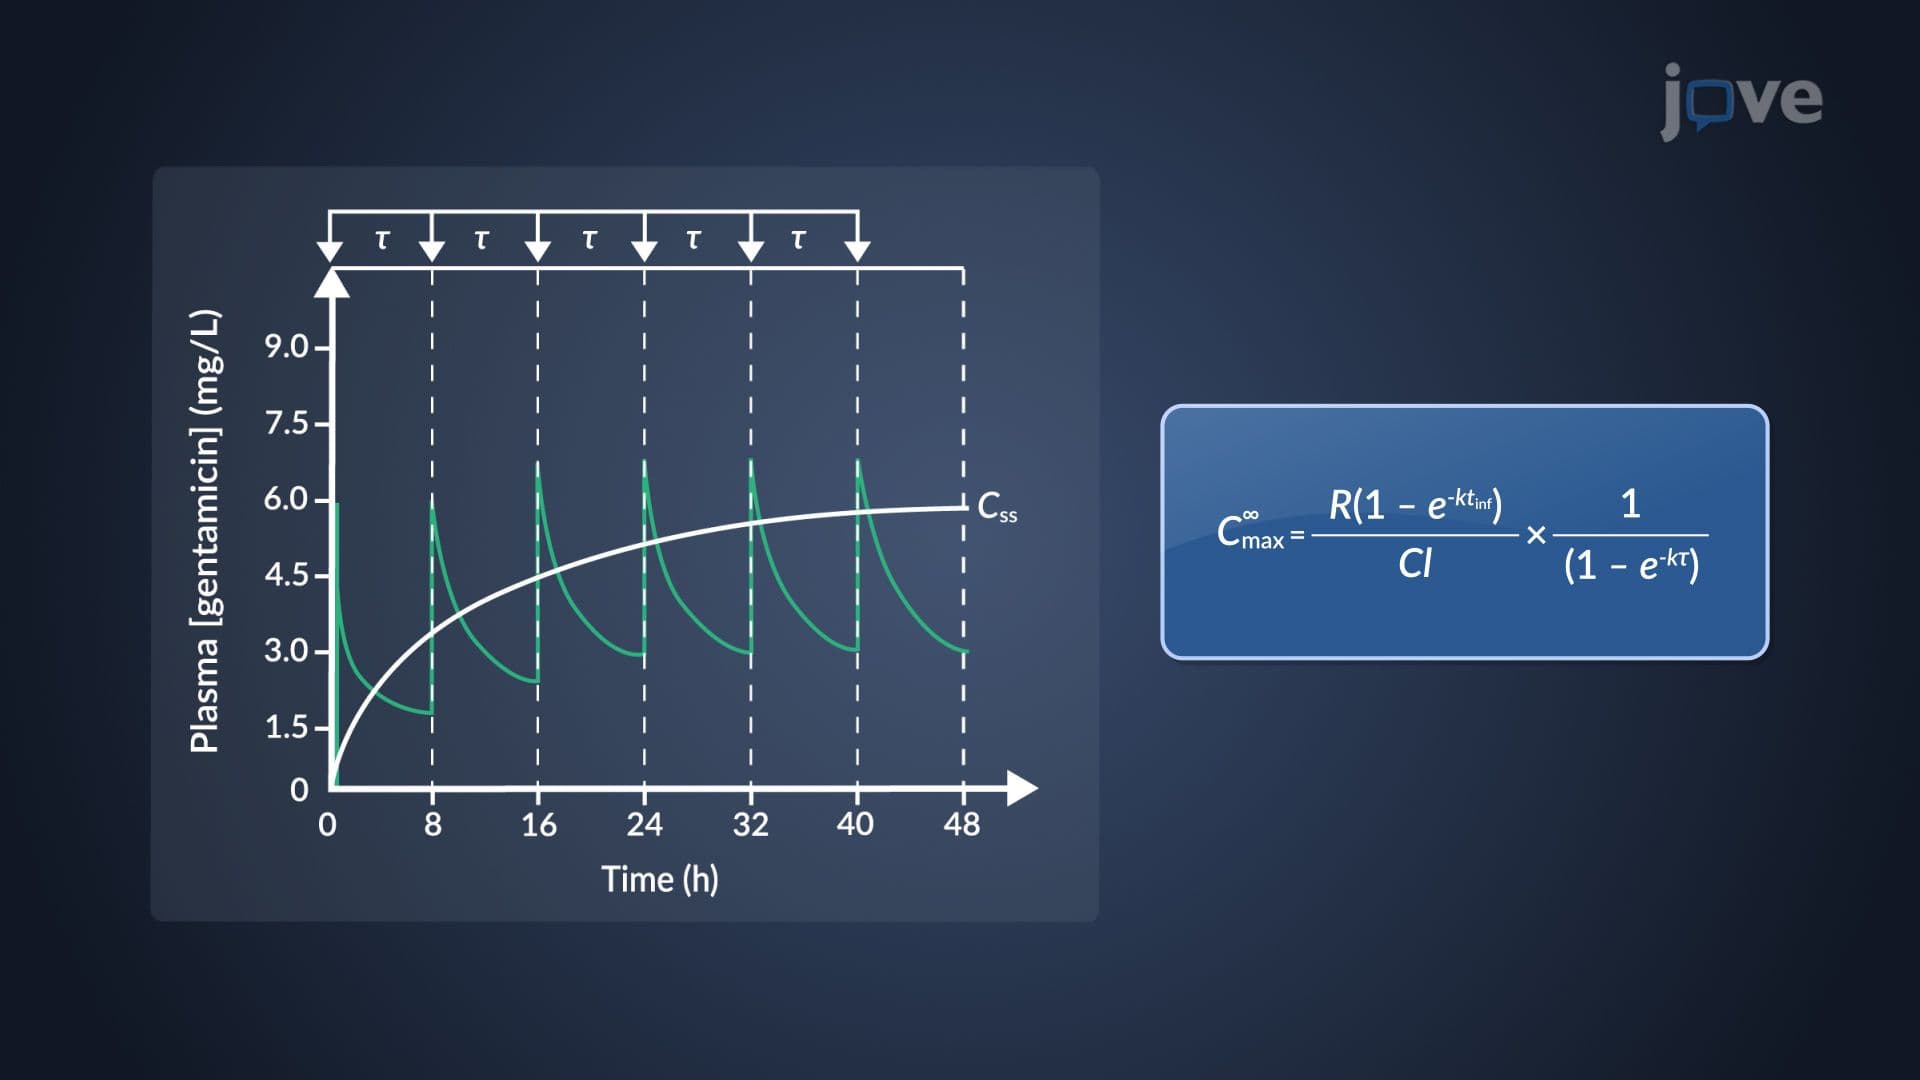 01:15
Determination of Multiple Dosing Parameters: Steady-State, Minimum and Maximum Concentrations
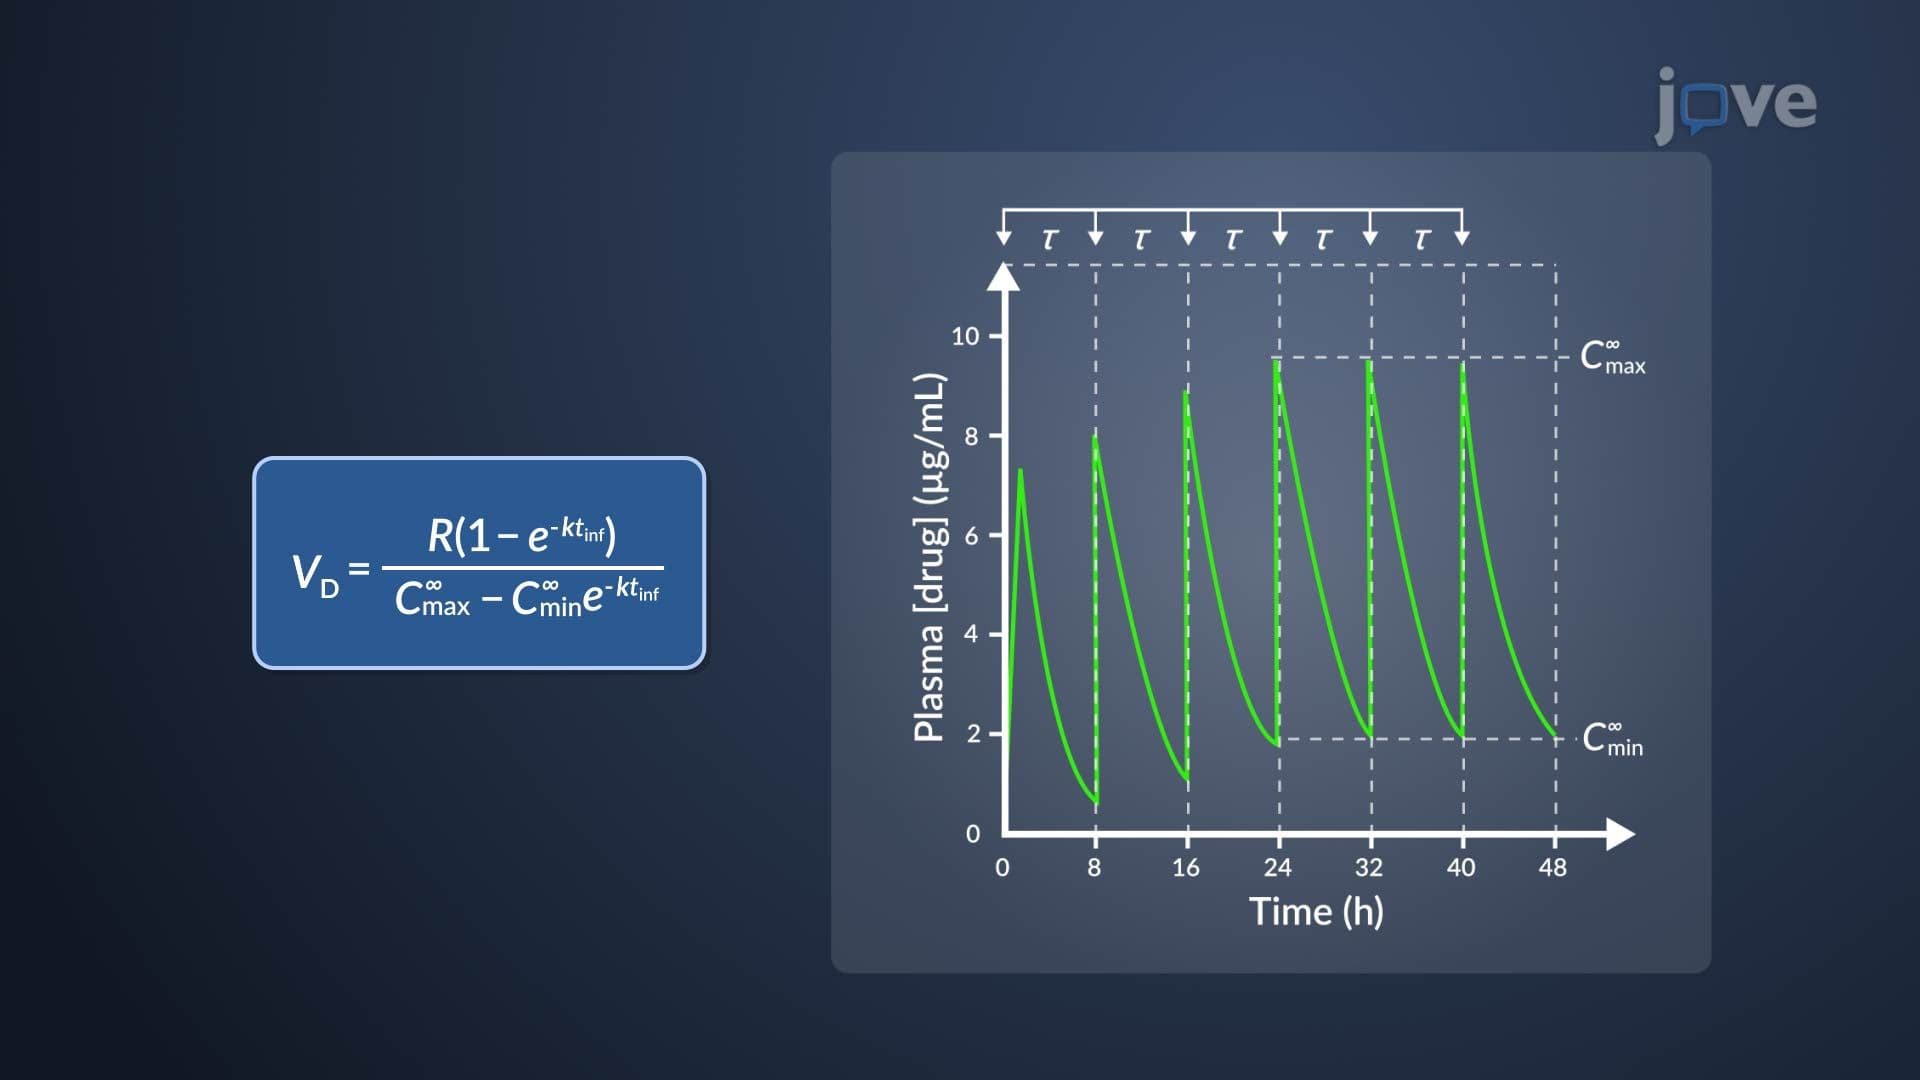 01:20
Estimation of k and VD of Aminoglycosides
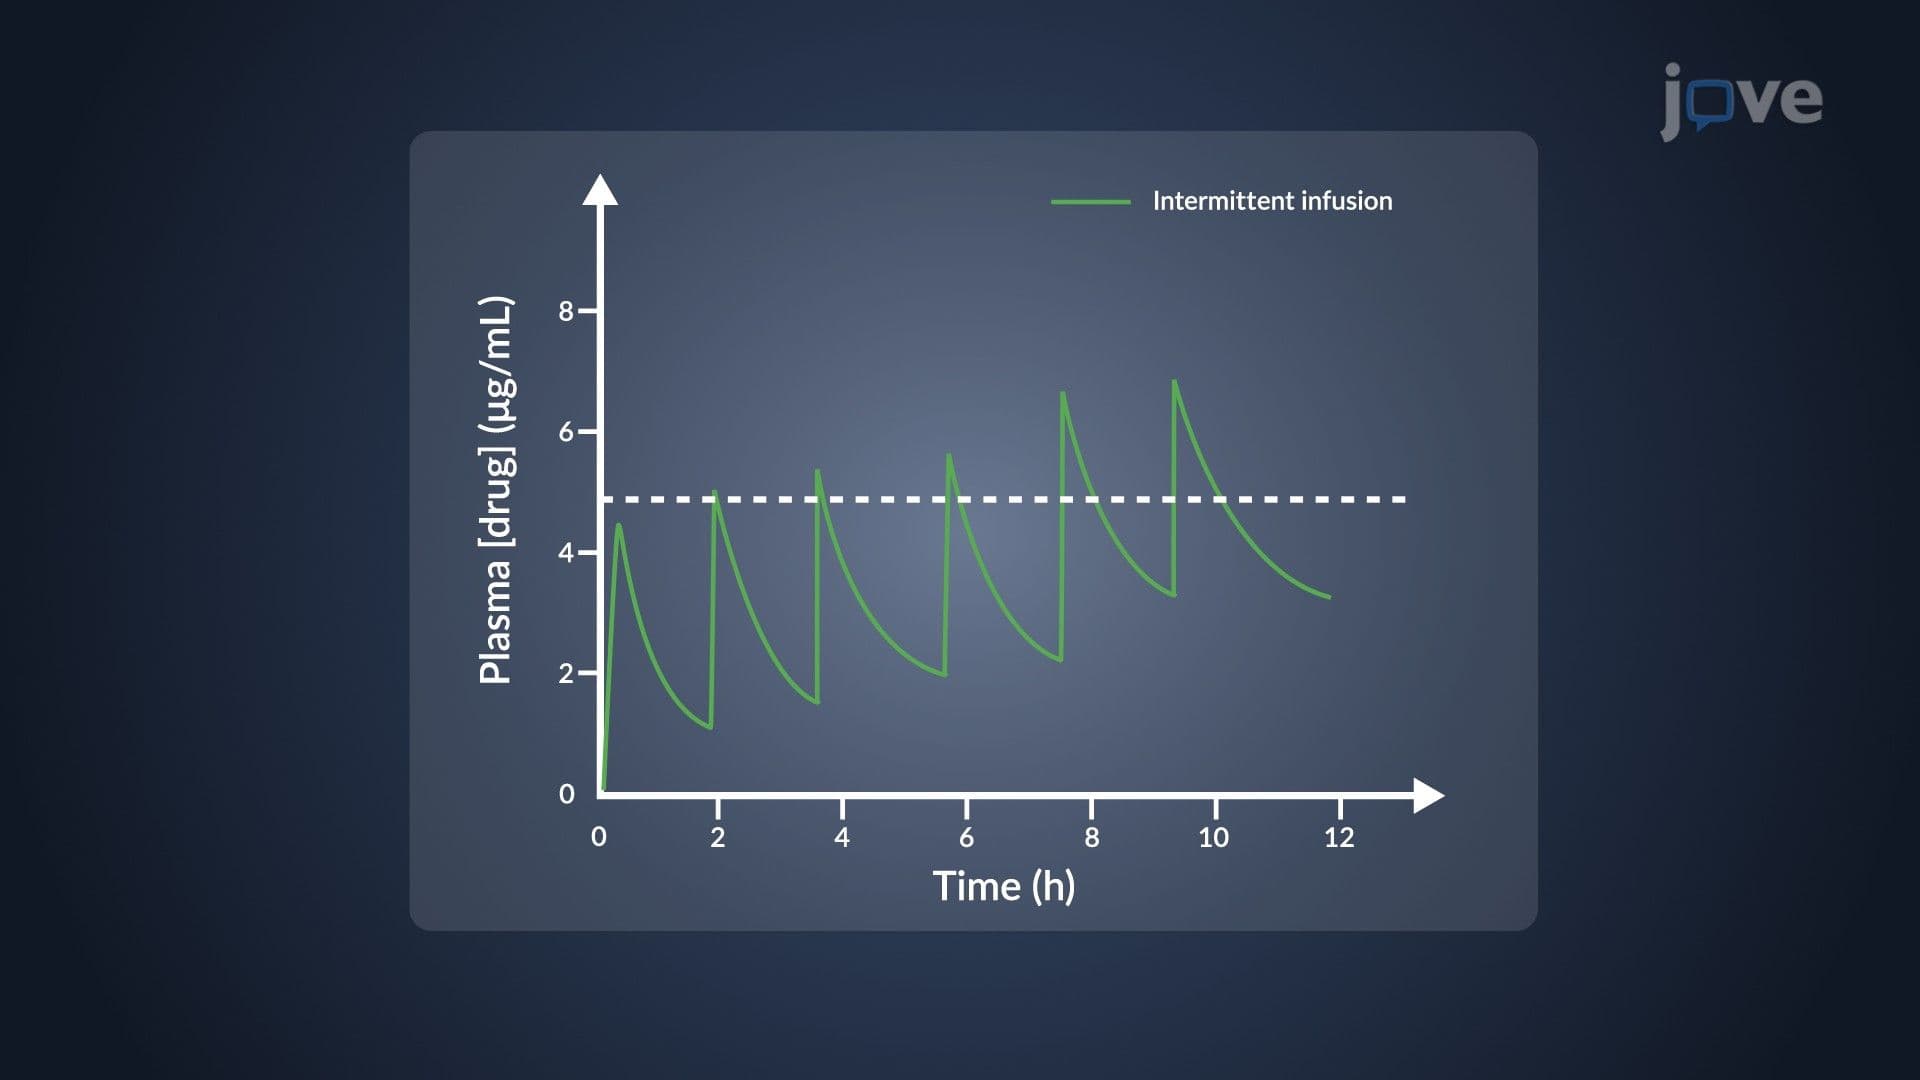 01:24
Drug Accumulation During Multiple Dosing: Intermittent IV Infusions
 01:28
Drug Dosing in Renal Diseases: Estimation of Glomerular Filtration Rate Based on Serum Creatinine Concentration
 01:11
Renal Failure: Dose Adjustments
Reduced renal clearance and elimination rate are common outcomes of renal impairment. These alterations lead to a prolonged elimination half-life and an altered apparent volume of distribution for drugs. As a result, dosage adjustments are typically necessary to maintain optimal drug levels in the body.
However, dosage adjustments...