Related Experiment Video
Updated: Mar 11, 2026

Occlusion of the Great and Small Saphenous Vein Using Copolymeric Glue Based on N-Butyl Cyanoacrylate and Methacryloxy Sulfolane
Published on: December 9, 2022
[Compression therapy in correction of impaired venous outflow from lower limbs for pelvic varicose veins]
S G Gavrilov1, A V Karalkin1, E P Moskalenko1
1Savelyev University Surgical Clinic, Pirogov Russian National Research Medical University of the Ministry of Health of the Russian Federation, 119049, Moscow, Russian Federation.

Objective:
The aim of our investigation was to study the state of venous outflow from the lower extremities in patients with pelvic varicose veins (PVV) and the possibilities of compression treatment in correction of impaired evacuation function of the calf muscle pump (CMP).
Patients And Methods:
Our single-center prospective comparative cohort study included 90 female patients with symptomatic and asymptomatic forms of pelvic varicose veins and 10 women with varicose veins of the lower extremities (VVLE). All patients underwent duplex ultrasound of pelvic veins and lower-limb veins, radionuclide venography of the lower extremities and single-photon emission computed tomography (SPECT) of the pelvic veins with in vivo-labelled red blood cells. Using radionuclide methods, the evacuation function of the CMP was assessed based on determining the average time of isotope transport (Taverage) in seconds in the tendinous (Tav.1), muscular (Tav.2) parts of the pump and the popliteal vein (Tav.3). An increase in Tav.1 more than 6-8 s, Tav.2 >10-12 s, Tav.3 >12-16 s indicated CMP dysfunction. A scintigraphic sign of pelvic venous congestion (PVC) was an increase in the coefficient of pelvic venous congestion (CPVC) >0.5. Patients with CMP dysfunction were prescribed compression treatment (below-knee stockings or stockings of class 1 or 2). Repeat clinical and radionuclide examination with the assessment of the dynamics of symptoms and signs of chronic venous disease (CVD) and performance indicators of the CMP was carried out after ten days of using compression hosiery.
Results:
CMP dysfunction was found in 78.7% of patients with symptomatic PVV and in 74.4% of those with asymptomatic PVV, which was characterized by a significant increase in Taverage (Tav.1 - 18-30 s, Tav.2 - 27-45 s, Tav.3 - 20-40 s). Similar performance indicators of the CMP were noted in 90% of patients with VVLE, thus suggesting uniformity of impairments of the evacuation function of the CMP in patients with PVV and VVLE, regardless of the presence or absence of symptoms of CVD and the need for correction of these disorders. Class 1 compression below-knee stockings were used in 79.7% of patients with PVV. All patients with PVV and CMP dysfunction were found to have relief of symptoms of CVD and restoration of the evacuation function of the CMP (Tav.1 - 6-14 s, Tav.2 - 9-16 s, Tav.3 - 7-14 s) after compression treatment.
Conclusion:
CMP dysfunction occurs in 76.7% of patients with PVV, regardless of the clinical course of the disease and the presence or absence of CVD of the lower extremities. Compression treatment using class 1 below-knee stockings is an effective method for restoring the evacuation function of the CMP in patients with PVV.

Related Concept Videos
 01:26
Varicose Veins II: Diagnostic Studies and Interprofessional Care
 01:29
Venous Thrombosis III: Interprofessional Care
 01:30
Venous Thrombosis IV: Nursing Management
 01:20
Venous Thrombosis II: Clinical Manifestations and Diagnostic Studies
 01:26
Varicose Veins I: Introduction
 01:15
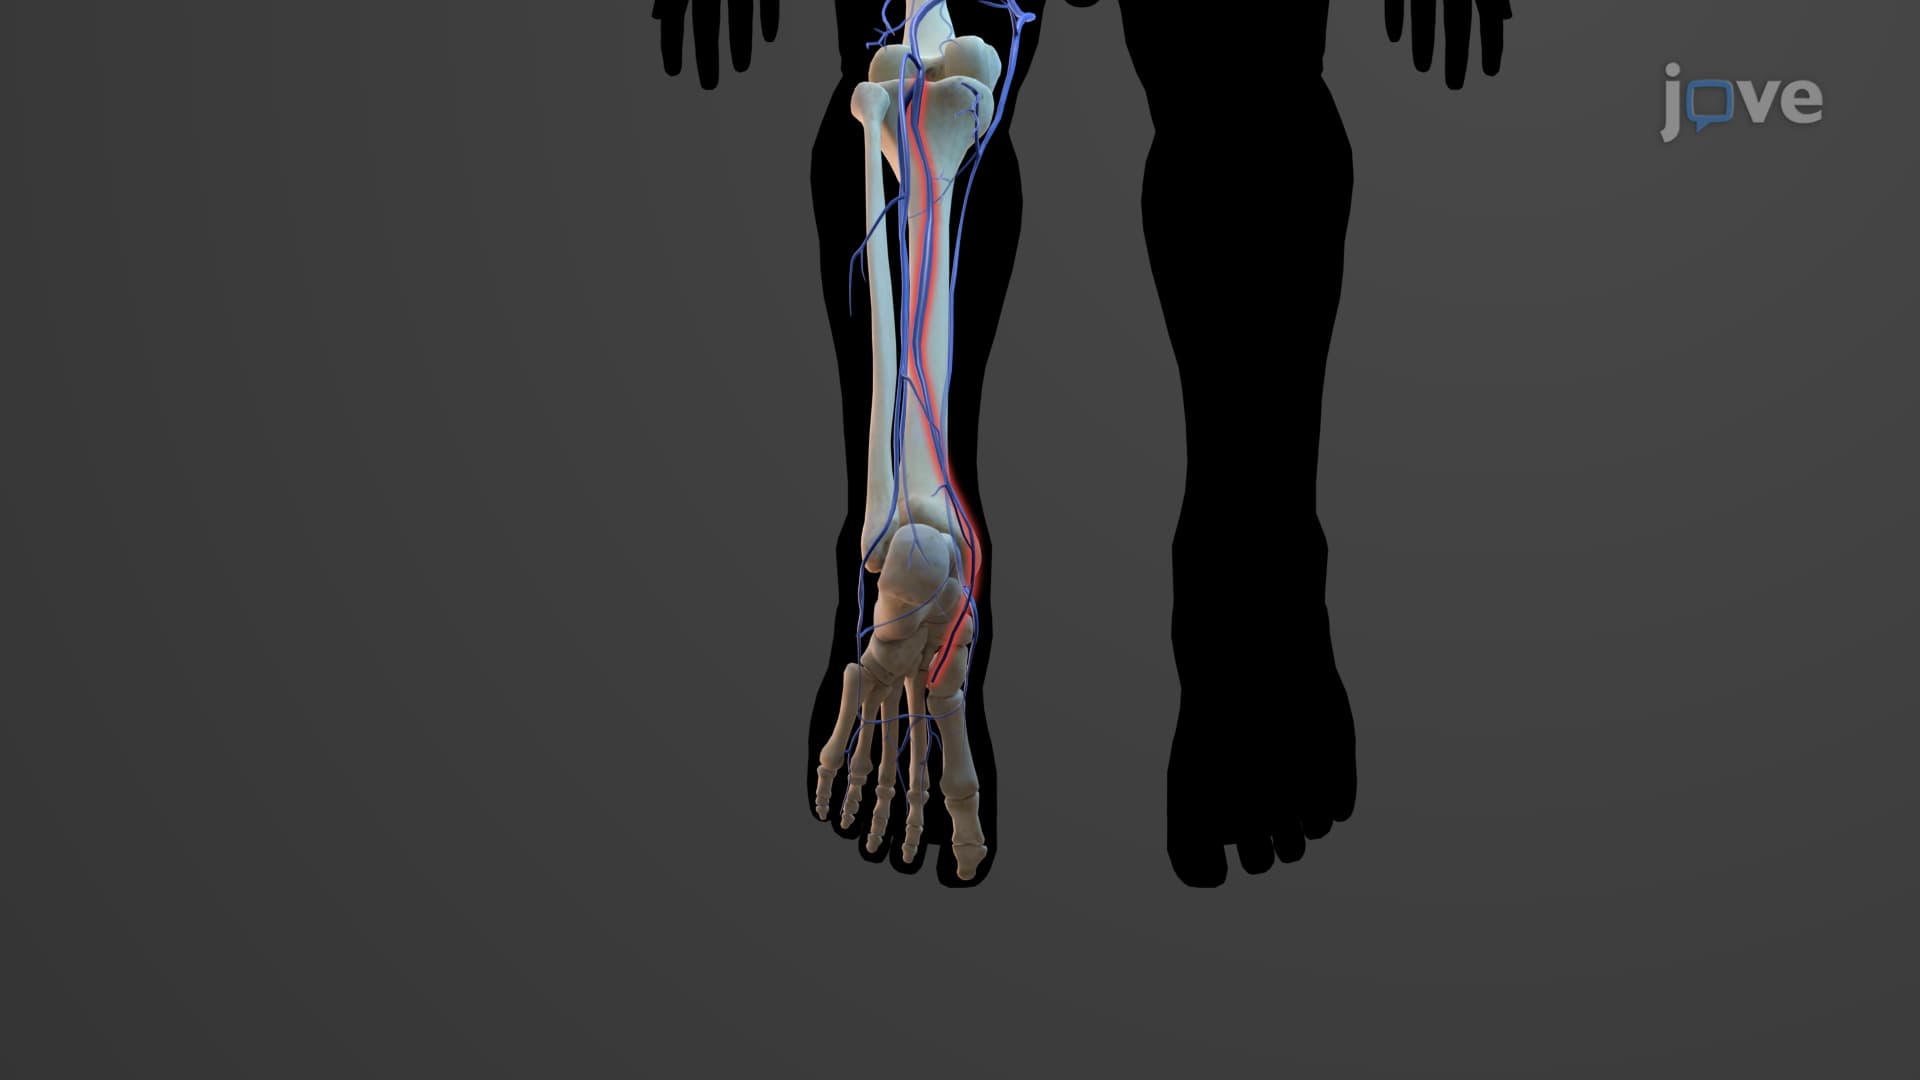
Veins of Lower Limbs
Formed by the union of the medial and lateral plantar veins, the posterior tibial vein, rising through the calf muscle, assimilates the fibular vein. The anterior tibial vein, a superior extension of the foot's dorsalis pedis vein, merges with the posterior tibial vein at the...