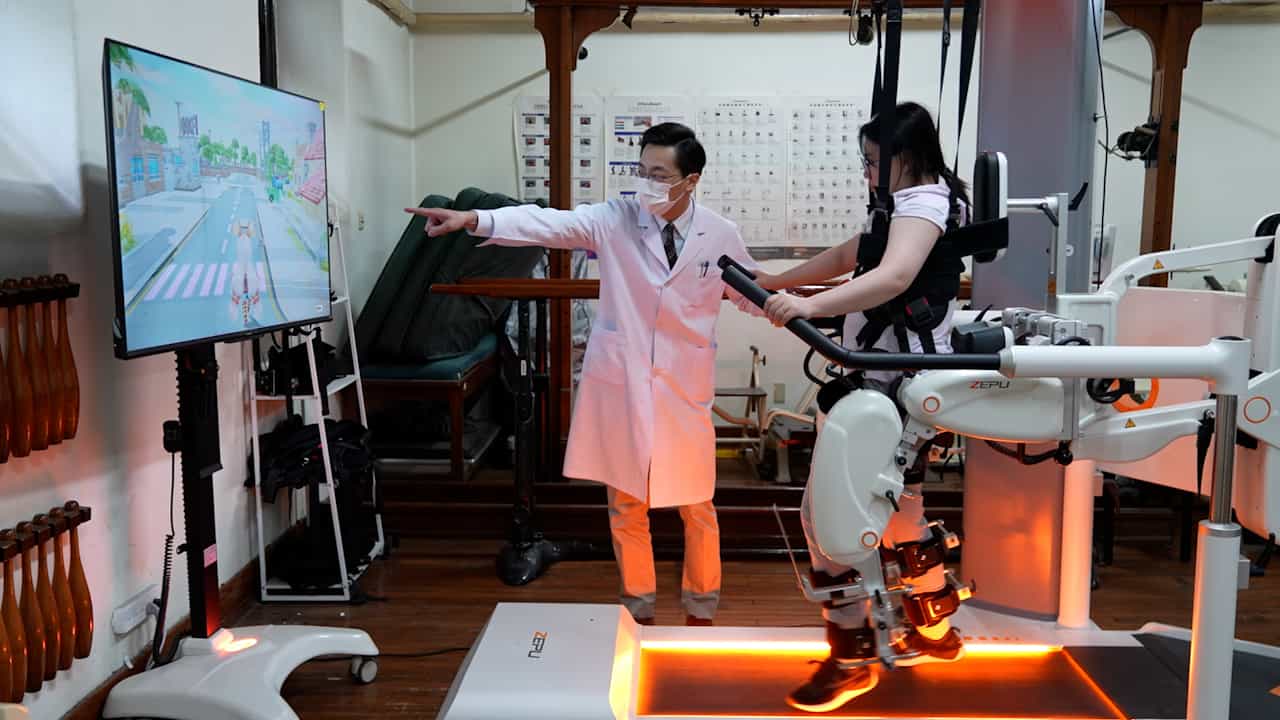
Related Experiment Video
Updated: Mar 13, 2026


Author Spotlight: Rehabilitation of Stroke Patients With a Digital Occupational Training System
Published on: December 29, 2023
Effectiveness of Virtual Reality-Based Early Rehabilitation Strategies on Pain, Sleep, Anxiety, Balance, Cognition,
Fei Wu1,2, Yunting Wu1,2, Yana Xing1,3
1Nursing Department, Beijing Tiantan Hospital, Capital Medical University, No. 119, South 4th Ring West Road, Fengtai District, Beijing, China, Beijing, Beijing, China, 86 59978336.

Background:
Early rehabilitation is vital for functional recovery in critically ill patients. Virtual reality-based early rehabilitation intervention (VR-ERI) is an emerging strategy, but evidence on its feasibility, safety, and efficacy remains inconsistent and unsynthesized.
Objective:
We synthesized evidence from randomized controlled trials (RCTs) on the feasibility and safety of VR-ERI in adult critically ill patients and evaluated its effects on functional outcomes during intensive care unit (ICU) stay and at short-term follow-up (≤3 months post ICU).
Methods:
Following PRISMA (Preferred Reporting Items for Systematic Reviews and Meta-Analyses) 2020 guidelines, we searched 10 databases (eg, PubMed, Web of Science, Cochrane Library, and Embase) from inception to October 5, 2025, for Chinese and English publications. We included RCTs comparing VR-ERI with control measures initiated early (within 72 h of ICU admission) in adults. FW and YW independently screened studies and extracted data; YW and YX independently conducted the revised Cochrane Risk of Bias tool assessment. Data were synthesized narratively or via meta-analysis in R Studio using a random-effects model (Hartung-Knapp-Sidik-Jonkman adjustment). Effects were expressed as standardized mean differences (SMD; with Hedges g correction) with 95% CIs and 95% prediction intervals (95% PIs). Subgroup and sensitivity analyses were performed to explore heterogeneity and assess robustness. The Grading of Recommendations Assessment, Development, and Evaluation framework was used to assess the quality of evidence.
Results:
Sixteen RCTs (published 2020-2025) involving 1356 patients were included. Bias assessment found 1 study at low risk, 5 with some concerns, and 10 at high risk. Meta-analysis suggested potential trends for VR-ERI in improving ICU anxiety (SMD -0.86, 95% CI -1.85 to 0.13, 95% PI -3.75 to 2.03; very low certainty) and subjective sleep quality (SMD 3.36, 95% CI 0.77-5.94; very low certainty), with a more pronounced effect in the Richards-Campbell Sleep Questionnaire-assessed subgroup (SMD 5.12, 95% CI 0.54-9.71). At follow-up, VR-ERI showed trends toward improved balance (Berg Balance Scale: SMD 0.97, 95% CI 0.74-1.20, 95% PI 0.37-1.58; moderate certainty), limb motor function (Fugl-Meyer: SMD 1.40, 95% CI -0.23 to 3.02; low certainty), and cognitive function (SMD 0.78, 95% CI 0.16-1.39; low certainty). No significant differences were found for objective sleep measures or ICU pain (low to very low certainty). No serious adverse events were reported; only a few studies mentioned mild reactions, such as dizziness, nausea, and fatigue.
Conclusions:
This review indicates VR-ERI's potential to improve anxiety, subjective sleep, balance, cognition, and motor function in early ICU rehabilitation, while its effects on pain and objective sleep remain unclear and safety protocols need refinement. Given the high risk of bias, substantial heterogeneity, and imprecision, the overall certainty of evidence is low. Thus, VR-ERI may serve as a nonpharmacological adjunct, but its clinical translation requires consideration of cost and patient suitability, and more rigorous research is needed.