Related Experiment Video
Updated: Jul 14, 2026


Vessel-sparing Excision and Primary Anastomosis
Published on: January 7, 2019
Uroflow outcomes after distal hypospadias repair: A systematic review and meta-analysis comparing TIP and Non-TIP
Ramesh Babu1, V V S Chandrasekharam2
1Department of Pediatric Urology, Sri Ramachandra Institute of Higher Education & Research, Chennai, 600116, India.

Background:
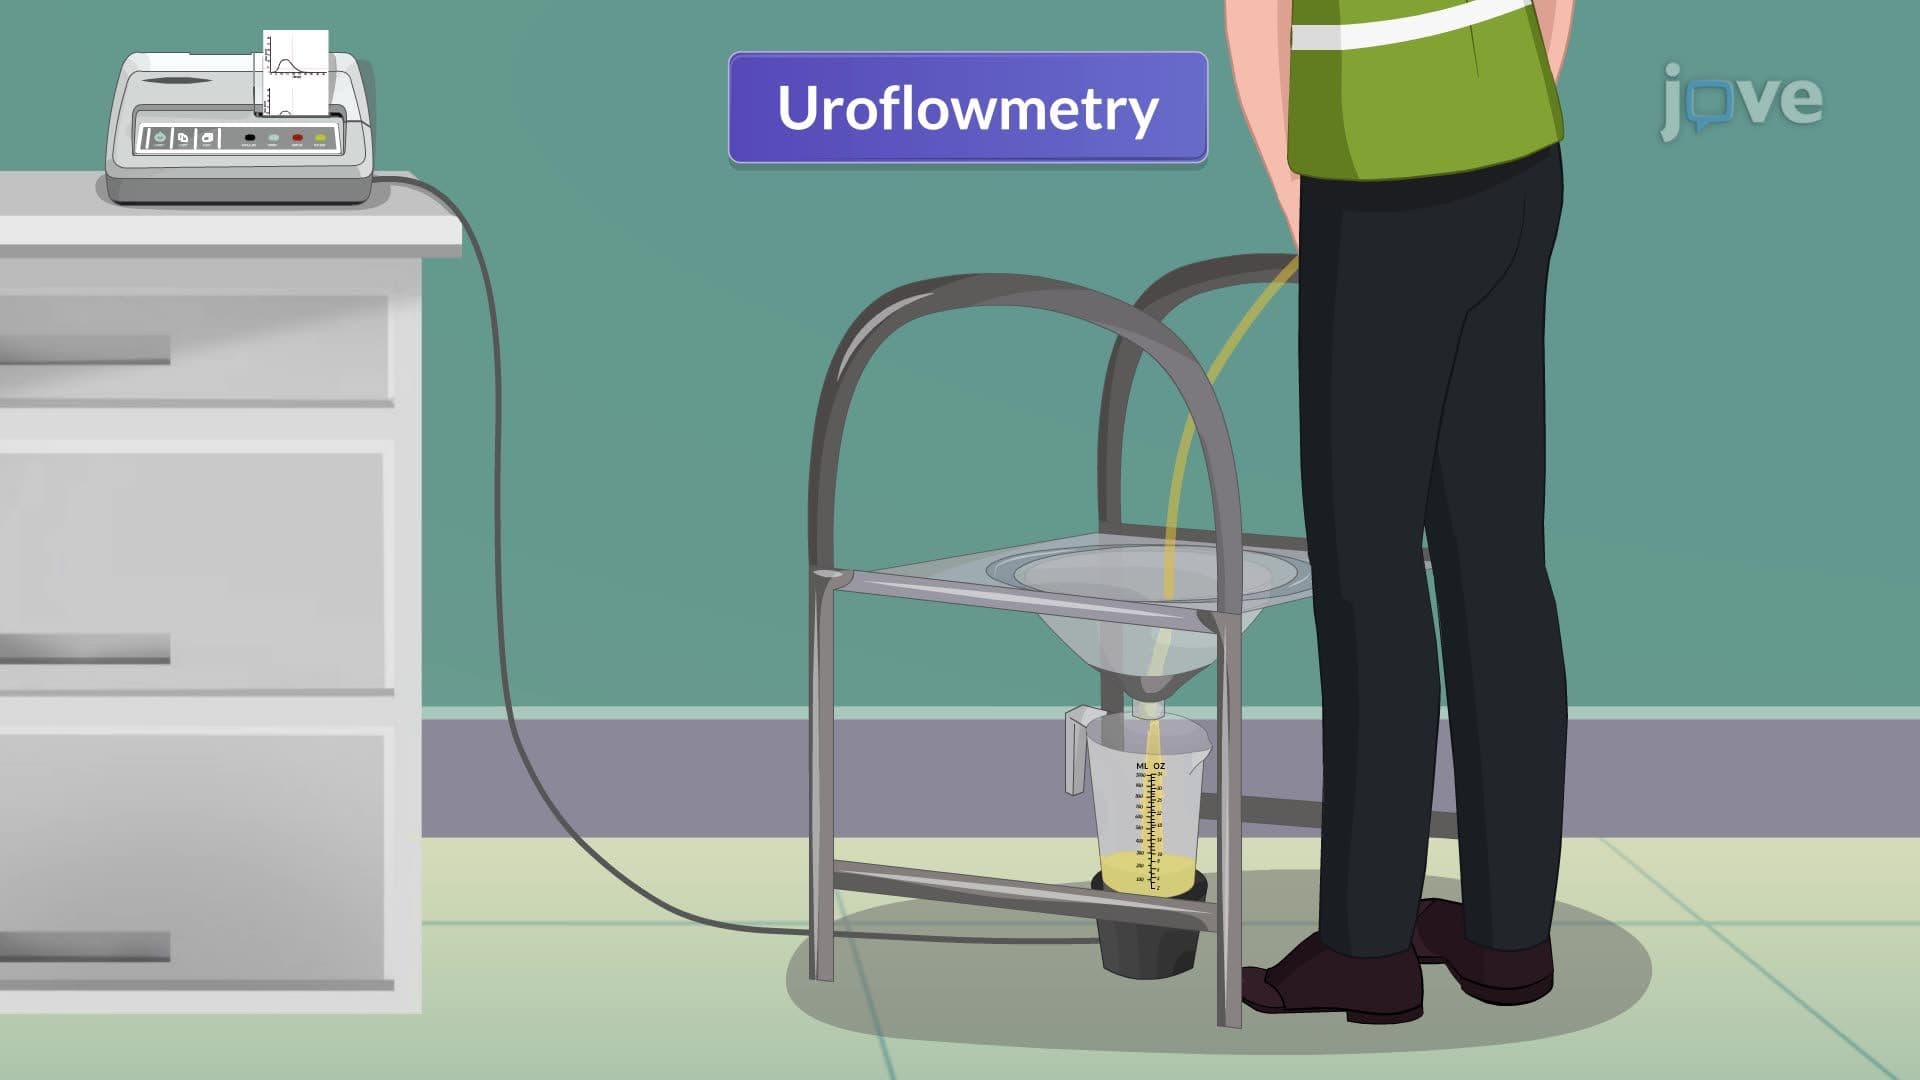
Objective evaluation of functional outcomes after hypospadias repair is essential, and uroflowmetry remains the most widely used non-invasive tool for assessing postoperative voiding. Although the Tubularised Incised Plate (TIP) repair is popular for distal hypospadias, concerns persist regarding meatal and neourethral stenosis, with limited consolidated evidence comparing uroflow outcomes between TIP and non-TIP techniques. This systematic review and meta-analysis aimed to compare uroflowmetry findings following TIP versus non-TIP repairs in children with hypospadias.
Methods:
A systematic search of PubMed, Embase, Web of Science and Cochrane Library (2010-2025) identified studies reporting uroflow outcomes after distal hypospadias repair. Eligible studies included children undergoing TIP or non-TIP urethroplasty for distal hypospadias reporting postoperative uroflowmetry findings. Non-English articles, reviews, case reports, and studies with incomplete data were excluded. Risk of bias was assessed using the Robvis tool across domains including performance, selection, attrition, reporting, sample size adequacy and intervention fidelity. Meta-analysis was performed using MetaXL 5.3 with pooled prevalence estimates and assessment of heterogeneity (I2). Odds ratios comparing abnormal uroflow between TIP and non-TIP repairs were generated using RevMan 5.4. A subgroup analysis evaluated the prevalence of patients requiring urethral or meatal dilatation.
Results:
Eight studies comprising 577 children met inclusion criteria. Seven studies reported TIP outcomes, six reported non-TIP outcomes, and five provided direct comparisons within the same cohort. Median follow-up was seven years. Risk of bias was low in six studies and unclear in three. Marked heterogeneity existed across studies (TIP I2 = 84 %; non-TIP I2 = 61 %), largely reflecting variation in thresholds used to define obstruction. The pooled prevalence of abnormal uroflow was 38 % after TIP repair versus 25 % after non-TIP repairs. In direct comparisons, TIP repair demonstrated significantly higher odds of abnormal uroflow (OR 2.29; 95 % CI 1.35-3.9; p = 0.002). Subgroup analysis showed that 18 % of TIP patients required postoperative dilatation for stenosis, compared with 7 % of non-TIP patients.
Conclusion:
TIP repairs for distal hypospadias are associated with a higher prevalence of abnormal uroflow and a greater need for postoperative dilatation compared with techniques that create a circumferentially epithelialised neourethra (e.g., G-TIP, Mathieu, on-lay repairs). Although some studies report spontaneous improvement in uroflow over time, careful long-term surveillance is essential, particularly in children with initial abnormal uroflow/in those subjected to TIP repair. Standardisation of uroflow obstruction criteria and longer-term studies are required to clarify the clinical significance of these findings.
Prospero Registration:
CRD420251237507.