Related Experiment Video
Updated: Mar 15, 2026
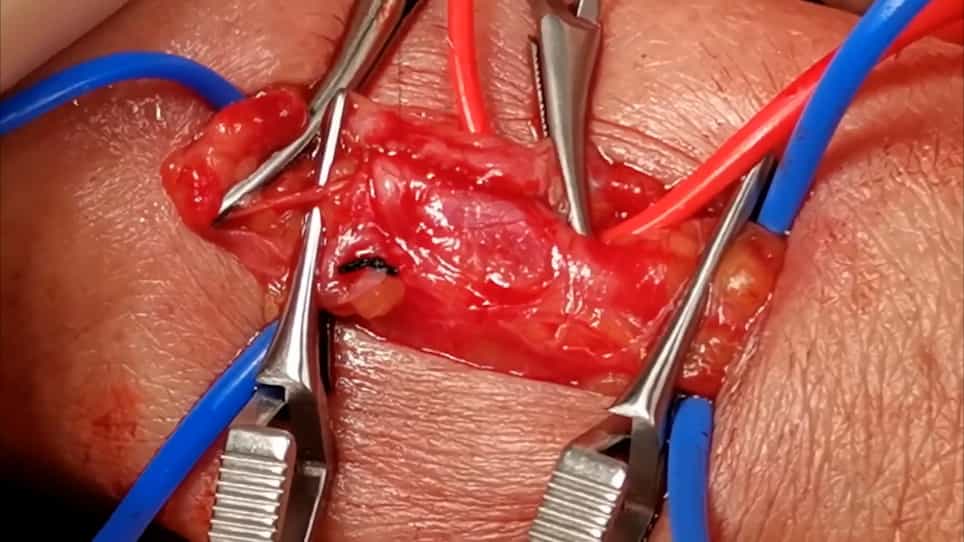
Creating Radio-cephalic Arteriovenous Fistula in the Forearm with a Modified No-Touch Technique
Published on: April 1, 2022
Endovascular Creation of Native Arteriovenous Fistulas for Hemodialysis: A Percutaneous, Vessel-Sparing Strategy for
Giulio Distefano1, Alessio Sturiale1, Concetto Sessa1
1Institute of Nephrology and Dialysis, Maggiore Hospital of Modica, ASP Ragusa, 97100 Ragusa, Italy.

Abstract:
Surgically created native arteriovenous fistulas (AVFs) remain the preferred vascular access for chronic hemodialysis, yet they are limited by substantial early failure and progressive consumption of venous capital. Endovascular arteriovenous fistulas (endoAVFs, also referred to as percutaneous AVFs) have become a catheter-based alternative to surgical AVF (sAVF). We conduct an updated narrative, practice-oriented review of the literature on endoAVF creation, and we qualitatively synthesize evidence. Two devices are currently available in contemporary clinical practice: a dual 4 Fr-catheter, fluoroscopy-guided radiofrequency system (WavelinQ) and a single 6 Fr-catheter, ultrasound-guided thermal resistance system (Ellipsys). Across prospective studies and real-world series, endoAVF creation is consistently reported to have high technical success, with low major complication and infection rates. Clinical usability can often be achieved within weeks when ultrasound-based surveillance and protocol-driven maturation assistance are implemented; however, adjunctive procedures are frequently required and should be anticipated in program planning and informed consent. Observational comparisons and pooled analyses indicate broadly comparable functional outcomes versus surgery in selected cohorts, while estimates of primary patency and maintenance burden vary substantially across studies. Overall, endoAVFs represent a feasible, minimally invasive, vessel-sparing option that can be integrated into multidisciplinary access pathways in anatomically suitable candidates and experienced centers, complementing rather than replacing surgical strategies within a distal-first plan. Recent society practice guidance further emphasizes standardized mapping, expectation setting, troubleshooting algorithms for non-maturation, and dialysis-unit cannulation training to support consistent implementation. Pragmatic comparative studies and long-term registries using standardized endpoints, paired with healthcare-system-specific economic analyses, are needed to better define durability, resource use, and patient-centered outcomes over the full-access life cycle.

Related Concept Videos
 01:25
Hemodialysis I: Introduction
 01:24
Hemodialysis II: Procedure and Complications
 01:30
Continuous Renal Replacement Therapy
 01:25
Hemodialysis III: Nursing Management