Related Experiment Video
Updated: Mar 17, 2026

Inspiratory Muscle Training as an Adjunct to the Treatment of Weaning Failure in Critically Ill Patients: A Practical Guide
Published on: January 30, 2026
Femoral Muscle Volume Change and Postextubation Respiratory Support in Infants After Cardiac Surgery
Natsuhiro Yamamoto1,2, Masanori Tani3, Takahiro Mihara4
1Dr. Yamamoto is affiliated with Department of Anesthesiology and Critical Care Medicine, Yokohama City University School of Medicine, Kanagawa, Japan.

Insights
Femoral ultrasonography did not predict respiratory support needs in infants after heart surgery. Other measures like tidal volume and breathing frequency were more effective predictors of post-extubation support.
Area of Science:
- Pediatric critical care medicine
- Cardiovascular surgery
- Respiratory physiology
Background:
- Noninvasive respiratory support aims to reduce extubation failure in infants post-cardiac surgery.
- Accurate stratification of high-risk infants is essential for effective respiratory support.
- Investigating novel predictive markers for post-extubation respiratory support is crucial.
Purpose of the Study:
- To evaluate the predictive capability of femoral ultrasonography for respiratory support requirements in infants following cardiac surgery.
- To assess the utility of the femoral muscle index and its changes in predicting the need for post-extubation respiratory support.
Main Methods:
- Prospective observational study of infants undergoing cardiac surgery requiring prolonged mechanical ventilation (>48 h).
- Femoral ultrasonography performed on pediatric intensive care unit (PICU) admission and pre-extubation.
- Receiver operating characteristic (ROC) curve analysis used to assess the predictive accuracy of femoral muscle index and its change.
Main Results:
- Femoral muscle cross-sectional area (CSA) changes were not significantly different between infants requiring and not requiring respiratory support.
- The femoral muscle index and its percent change showed limited predictive value (ROC-AUC 0.50 and 0.63, respectively).
- Body weight-adjusted tidal volume and breathing frequency were stronger predictors (ROC-AUC 0.81 and 0.72, respectively).
Conclusions:
- Femoral muscle volume and its changes during mechanical ventilation lack meaningful predictive value for post-extubation respiratory support needs in this population.
- Clinical utility of muscle loss assessment via femoral ultrasonography requires further investigation across diverse patient groups and outcomes.
Background:
Noninvasive respiratory support following extubation is expected to reduce extubation failure; however, stratifying high-risk patients is crucial. We investigated the predictive value of femoral ultrasonography for postextubation respiratory support requirements in infants following cardiac surgery.
Methods:
In this single-center, prospective observational study, infants who underwent cardiac surgery for congenital heart disease between November 2020 and September 2023 and required mechanical ventilation for >48 h were recruited. Participants were tested for extubation readiness following a standardized protocol, including a spontaneous breathing trial. Femoral ultrasonography was performed within 24 h of pediatric intensive care unit admission and 48 h before extubation. Respiratory support requirements were evaluated by a standardized protocol during the first 48 h after extubation. The prediction accuracy of the femoral muscle index (femoral muscle cross-sectional area (CSA) divided by squared height) or its change for postextubation respiratory support requirement was evaluated using receiver operating characteristic (ROC) curve analysis.
Results:
The study included 42 infants, and 26 (61.9%) subjects required respiratory support. The femoral muscle CSA exhibited a median change of -17.3% (interquartile range -24.2, -3.9) during mechanical ventilation in subjects requiring respiratory support and -9.7% (-17.6, 5.6) in those without such requirement. The area under the ROC curve (ROC-AUC) for predicting postextubation respiratory support requirement by the femoral muscle index and its percent change were 0.50 (95% CI: 0.31-0.69) and 0.63 (CI: 0.45-0.80), respectively. In contrast, body weight-adjusted tidal volume and breathing frequency before extubation demonstrated strong predictive value (ROC-AUC values of 0.81 [CI: 0.66-0.95] and 0.72 [CI: 0.56-0.89], respectively).
Conclusions:
The femoral muscle volume and its change during mechanical ventilation provided no meaningful predictive values for postextubation respiratory support requirements in infants after cardiac surgery. Further research should assess clinical importance of muscle loss across outcomes and populations.
More Related Videos


Related Concept Videos
 01:15
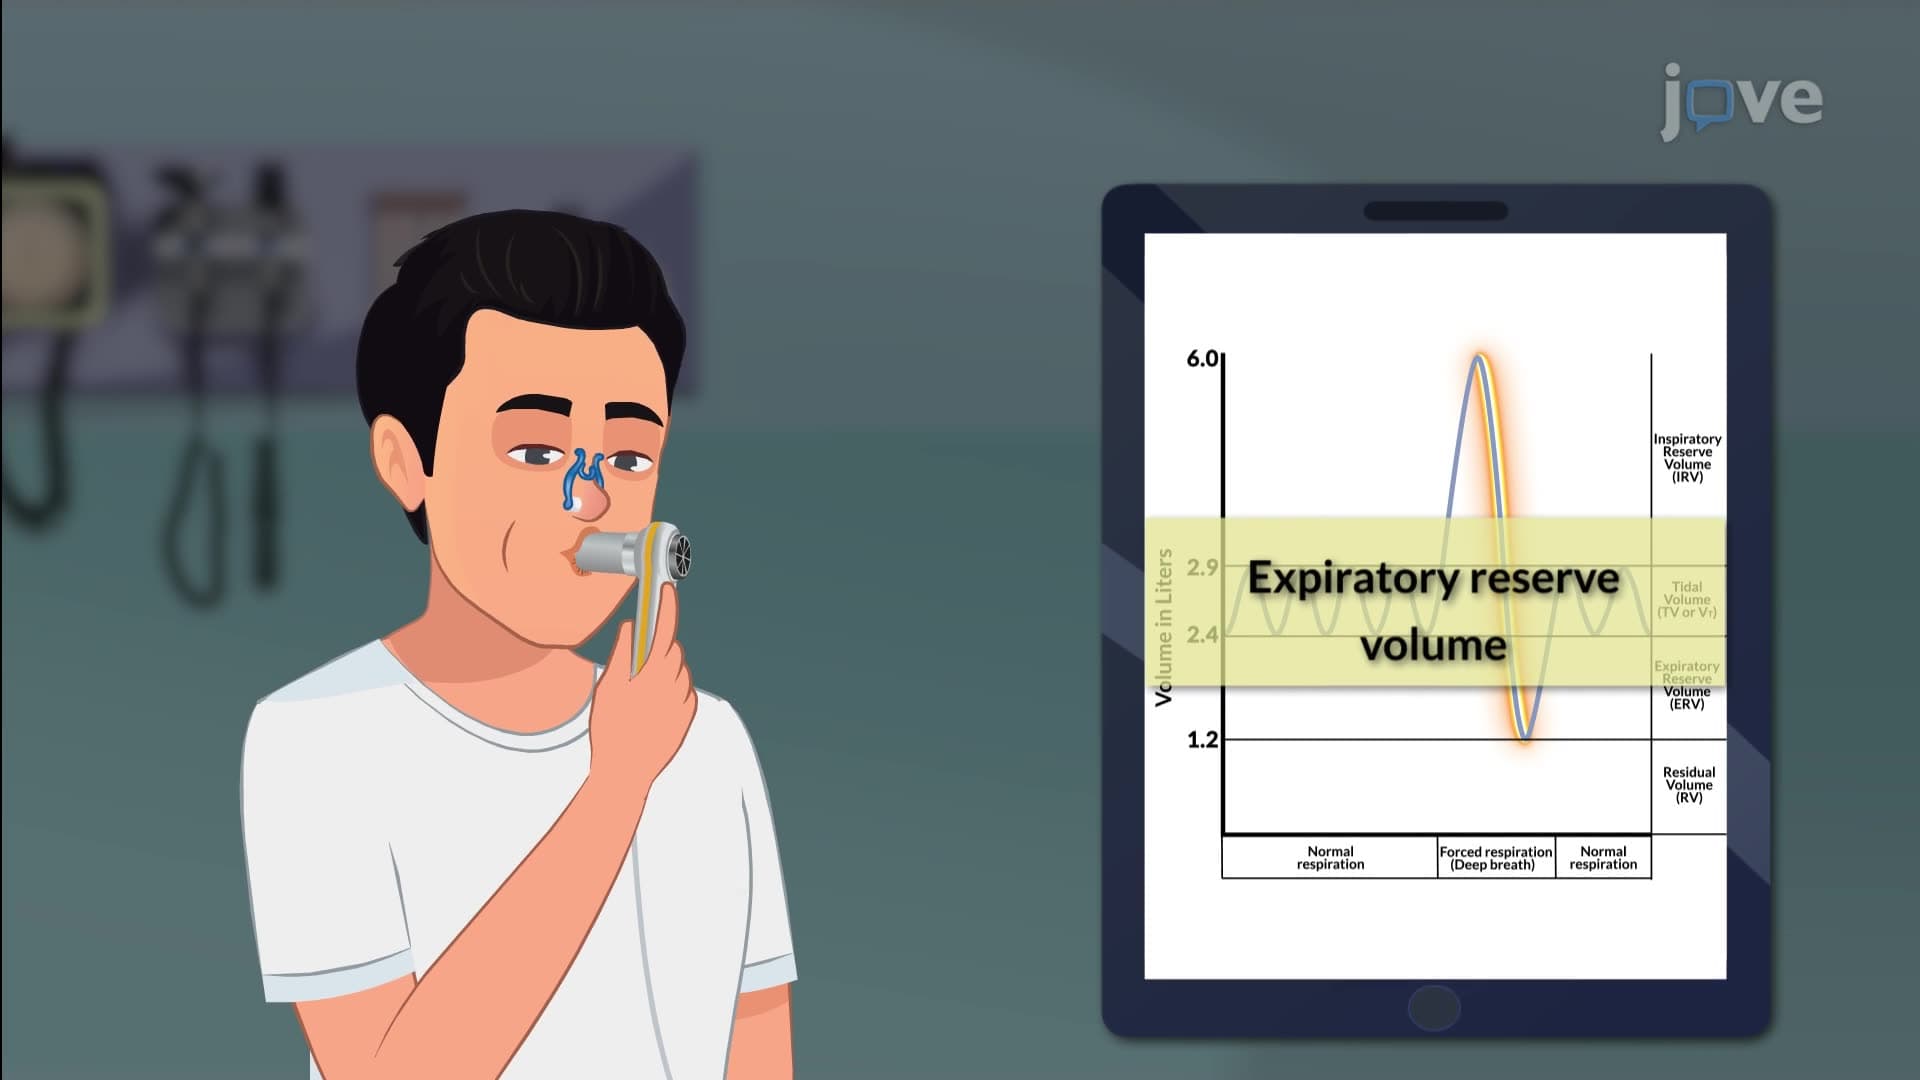
Respiratory Volumes
Tidal Volume (TV) Tidal volume (TV) is the air inhaled or exhaled in a...
 01:22
Respiratory Volumes and Capacities
 01:26
Respiratory Volumes and Capacities I
 01:22
Cardiopulmonary Resuscitation II: ACLS Airway Management
 01:24
Pulmonary Ventilation: Inhalation
Boyle's law becomes particularly pertinent when examining respiratory...
 01:28
Cardiomyopathy VII: Pre and Post Operative Nursing Management