Related Experiment Video
Updated: Mar 25, 2026

Author Spotlight: An Economic and Efficient Method for Quantitative Evaluation of Bone Microarchitecture in a Murine Osteoporosis Model
Published on: September 8, 2023
Contributions of Bone Microarchitecture to Skeletal Fragility in Adults with Longstanding Type 1 Diabetes
Lipi A Marion1, Fjola Johannesdottir2,3, Crystabella E Nevarez1
1Endocrine Unit, Massachusetts General Hospital, Boston, MA.

Abstract:
Type 1 diabetes mellitus (T1D) is associated with a marked increase in fracture risk, a phenomenon not entirely explained by lower DXA-BMD. Emerging evidence suggests T1D may adversely affect bone microarchitecture, though findings are inconsistent. We aimed to characterize bone microarchitecture and estimated bone strength in adults with longstanding T1D. We enrolled 96 individuals with T1D (median HbA1c 7.0% [IQR 6.3,7.7], mean diabetes duration 46±10 years) and 57 individuals without diabetes, all aged >50 years. Assessments included areal BMD (aBMD) at the lumbar spine, femoral neck, and total hip via DXA, trabecular bone score (TBS), and high-resolution peripheral quantitative computed tomography (HR-pQCT) to evaluate volumetric BMD (vBMD), bone microarchitecture, and estimated failure load at the distal radius and tibia. Individuals with T1D were more likely to report prior history of fracture compared to controls (26% vs 4%, p<0.001). After adjusting for age, sex, height, and weight, aBMD and TBS did not differ between groups. HR-pQCT revealed modest cortical deficits in the T1D group, with largely preserved trabecular microarchitecture and no significant difference in estimated failure load compared to control participants. Within the T1D group, those who reported a prior fracture had lower spine aBMD and lower estimated strength at the tibia. Notably, individuals diagnosed with T1D at or before age 12 years had worse trabecular parameters at the radius than those diagnosed later, with no corresponding differences at the tibia and no differences seen on DXA. Retinopathy was associated with lower aBMD at the hip and femoral neck and with reductions in trabecular thickness, area, failure load, and stiffness at the tibia. The minor differences in bone microarchitecture observed in this study may partly contribute to the increased fracture risk among patients with T1D, though more research examining mediating factors both intrinsic and extrinsic to bone is needed.

Related Concept Videos
 01:29
Bone Disorders
Bone deposition is also affected by the levels of sex hormones like estrogen and testosterone that promote osteoblast activity and bone matrix synthesis. When the level of these hormones decreases due to aging, it causes a reduction in bone deposition. As a result, bone resorption by osteoclasts...
 01:09
Changes in the Appendicular Skeleton with Age
Initially, the limb buds consist of a core of mesenchyme covered by a layer of ectoderm. The ectoderm at the end of the limb bud thickens to form a narrow crest called the apical ectodermal ridge. This ridge stimulates the underlying...
 01:31
Essential Minerals for Bone Health
Calcium and Phosphorus
Calcium is a critical component of bones, especially in the form of calcium phosphate and calcium carbonate. Since the body cannot make calcium, it must be obtained from the diet. However, calcium cannot be absorbed from the small intestine without...
 01:40
Bone Remodeling
 01:02
What is the Skeletal System?
 01:27
Compact Bone
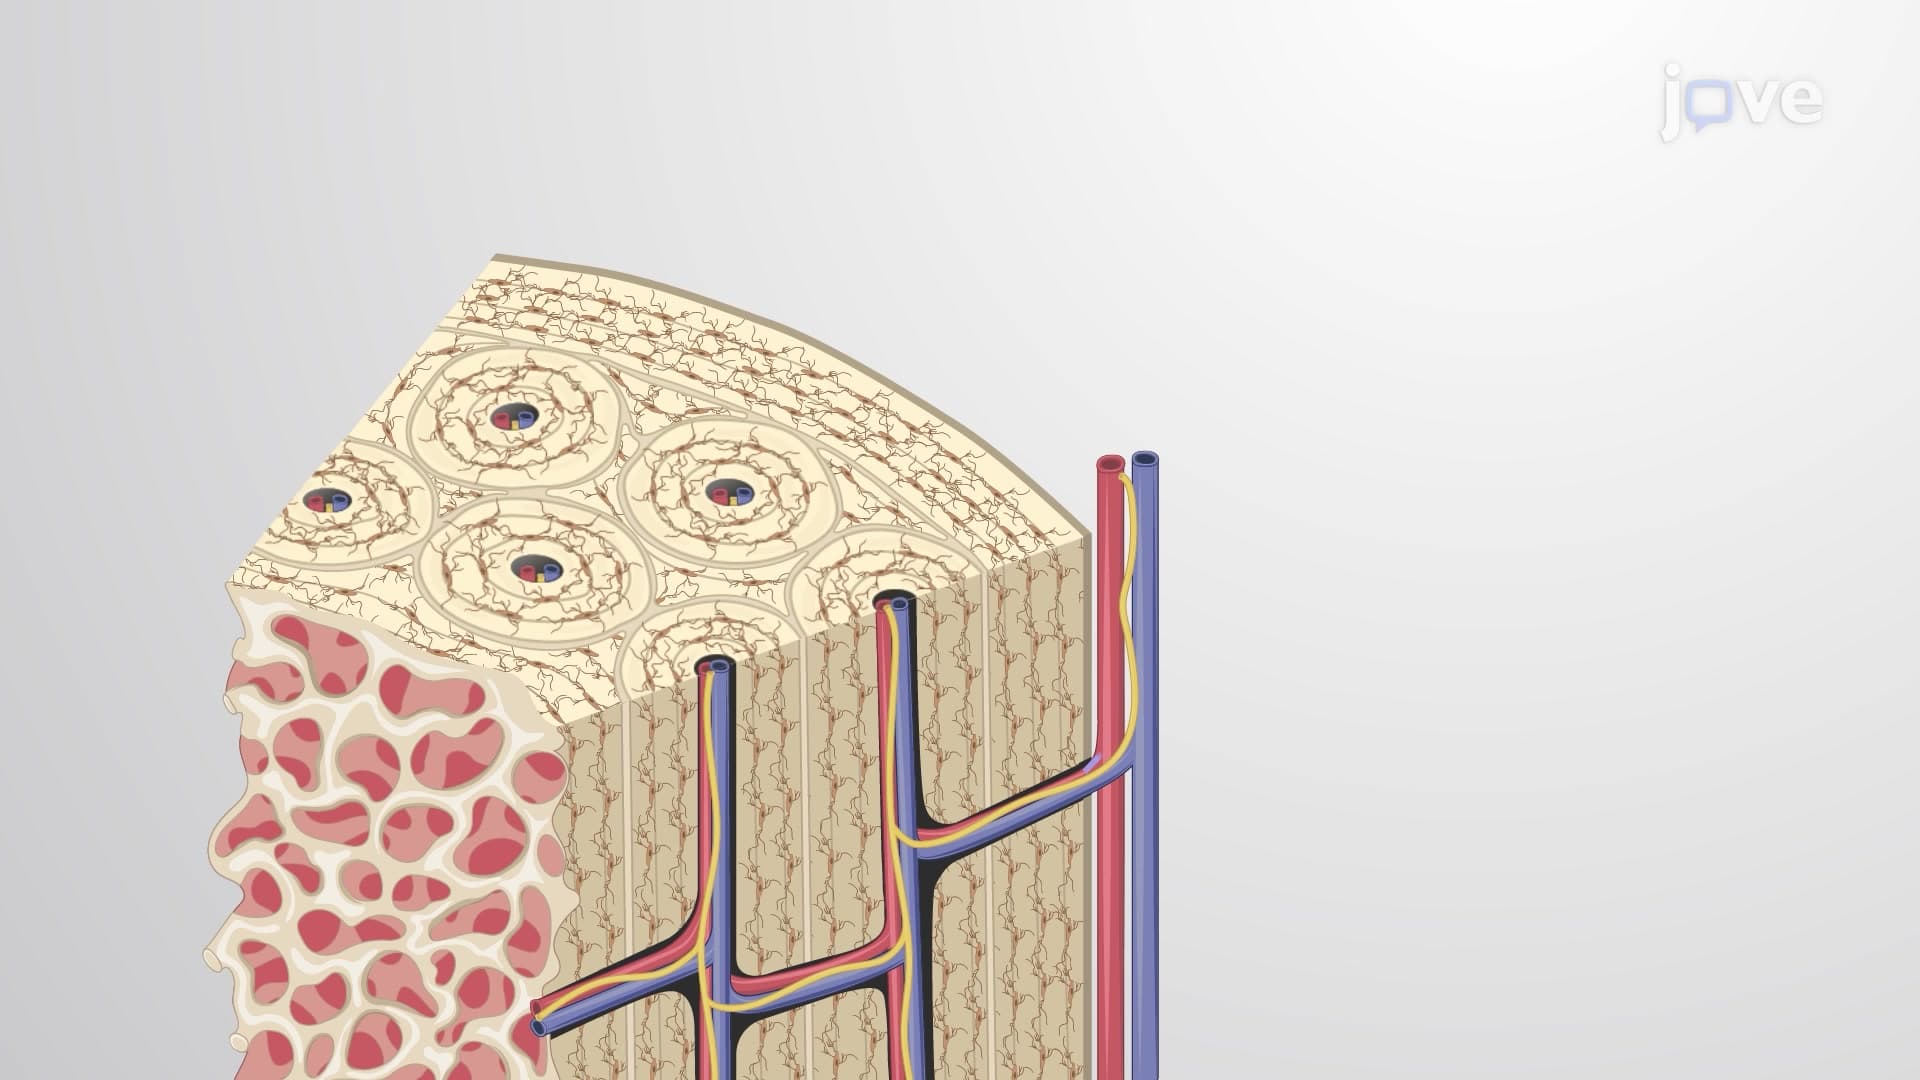
Compact bone, also called cortical bone, is the denser, stronger of the two types of bone tissue. It is found under the periosteum and in the diaphyses of long bones, where it provides support and protection. The microscopic structural unit of compact bone is called an osteon, or haversian system. Each osteon is composed of concentric rings of calcified...