Related Experiment Video
Updated: Apr 10, 2026

Anterior Capsular Reconstruction with Human Dermal Allograft for Irreparable Subscapularis Tears
Published on: May 9, 2025
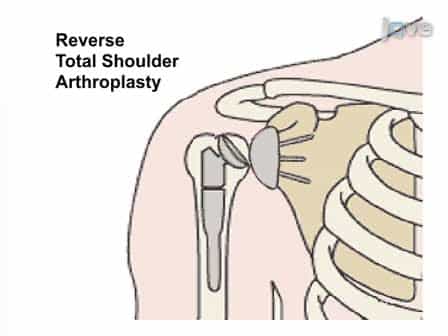
Glenoid defects in revision shoulder arthroplasty may be treated with coracoid autograft with reliable short-term
James Satalich1, Kevin Wall1, Nicholas Wiley1
1Department of Orthopaedic Surgery, Harvard Medical School, Massachusetts General Hospital, MGH Scapula Program, Boston, MA, USA.

Background:
Glenoid bone defects are common after failed arthroplasty or fracture fixation. Allograft or autograft reconstruction may be used to fill defects, however, may have increased failure rates or add to patient morbidity, respectively. We hypothesize that coracoid autograft can effectively fill contained glenoid defects and secondarily hypothesize that coracoid autograft has a low failure rate in early post-operative follow-up.
Methods:
A retrospective chart review was performed of all patients receiving coracoid autograft for glenoid bone defects during revision shoulder arthroplasty at a single institution, performed by 2 surgeons between 2020 and 2024. Pre-operative radiographs and computed tomography scans were analyzed to describe coracoid morphology and glenoid bone defects. Post-operative radiographs were analyzed for distalization shoulder angle, lateralization shoulder angle, and lateral humeral offset. Patient demographics and pre-operative and post-operative patient-reported outcome measures were collected.
Results:
Twenty-seven patients met criteria and were included for analysis. The average patient age was 67.2 ± 9.7 years (range 39-83 years). Average follow-up was 5.0 ± 4.6 months (range 1-17 months). Revisions were performed for the following indications: 9 (33.3%) patients with a failed hemiarthroplasty or hemiarthroplasty antibiotic spacer, 8 (29.6%) failed anatomic total shoulder arthroplasties, 8 (29.6%) reverse shoulder arthroplasties with baseplate failure, and 2 (7.4%) patients with post-traumatic glenoid injury from failed open reduction internal fixation.The average coracoid volume was significantly greater than the average defect volume (P < .001), and the average coracoid length was significantly greater than the average defect maximum depth (P < .001). The average coracoid diameter was smaller than the average defect height or width (P = .09) but not to a significant degree. There were no baseplate failures at last follow-up, though an overall revision rate of 11.1% (n = 3/27) attributed to hematoma (n = 1/3; 33.3%), intentionally staged procedure (n = 1/3; 33.3%), and tendon transfer reconstruction for lack of external rotation (n = 1/3; 33.3%) was observed. Visual analog scale (7.6 ± 1.8 vs. 1.8 ± 3.0; P = .001) and subjective shoulder value (23.4 ± 13.8% vs. 69.7 ± 16.6%; P < .001) improved following surgery.
Conclusion:
The coracoid is a viable autograft option for contained glenoid defects, showing similar dimensions to glenoid vault bone loss and no appreciable failures in early post-operative follow-up. The use of this specific autograft avoids morbidity and complications from iliac crest harvest, though longer follow-up is required to evaluate longitudinal risk of baseplate failure.