Related Experiment Video
Updated: Apr 11, 2026


Design of Cecal Ligation and Puncture and Intranasal Infection Dual Model of Sepsis-Induced Immunosuppression
Published on: June 15, 2019
[Risk factors for critical illness-related corticosteroid insufficiency in sepsis and construction of nomogram
Enfang Zhao1, Chunhua Hu, Tingyuan Zhang
1Department of Critical Care Medicine, Henan Provincial People's Hospital, Henan Key Laboratory for Critical Care Medicine, Zhengzhou University People's Hospital, Zhengzhou 450003, China. Corresponding author: Shao Huanzhang,

Objective:
To identify the risk factors of critical illness-related corticosteroid insufficiency (CIRCI) in patients with sepsis and to construct a nomogram model for predicting the occurrence of CIRCI in septic patients.
Methods:
A case-control study was conducted. A total of 50 patients with sepsis complicated by CIRCI who were admitted to Henan Provincial People's Hospital from January 2018 to December 2023 were enrolled as the CIRCI group. Meanwhile, 150 patients with sepsis but without CIRCI admitted during the same period were randomly selected as the control group. Baseline characteristics, etiologies of sepsis, vital signs, adrenal function indicators, serological parameters, intervention measures, disease severity scores, and prognosis-related outcomes were collected and compared between the two groups. Multivariate Logistic regression and inverse probability of treatment weighting (IPTW) regression analyses were performed to evaluate the correlation between various factors and the occurrence of CIRCI, screen out the influencing factors of CIRCI in septic patients, and construct a nomogram prediction model. The receiver operator characteristic curve (ROC curve) and calibration curve were used to assess the discrimination of the model. The Bootstrap method (with 1 000 repeated samplings) was adopted for internal validation, and the calibration curve was plotted to evaluate the calibration of the model. Decision curve analysis (DCA) was performed to assess the clinical validity of the model.
Results:
After adjusting for confounding factors, univariate Logistic regression analysis showed that older age, history of type 2 diabetes mellitus, higher white blood cell count (WBC), higher procalcitonin (PCT) level, higher serum K+ level, higher Acute Physiology and Chronic Health Evaluation II (APACHE II), and higher Sequential Organ Failure Assessment (SOFA) were associated with an increased risk of CIRCI, whereas higher serum sodium (Na+) level was associated with a decreased risk of CIRCI (all P<0.05). In addition, CIRCI was associated with longer ICU length of stay, longer duration of mechanical ventilation, as well as higher rates of 28-day mortality and ICU mortality (all P<0.05). Multivariate Logistic regression and IPTW regression analyses revealed that history of type 2 diabetes mellitus [odds ratio (OR)=1.574, 95% confidence interval (95%CI) was 0.558-4.437, P=0.022], elevated PCT level (OR=4.271, 95%CI was 1.637-11.139, P=0.003), elevated serum K+ level (OR=2.115, 95%CI was 0.909-4.921, P=0.044), elevated APACHE II score (OR=1.258, 95%CI was 1.071-1.478, P=0.006), and elevated SOFA score (OR=1.236, 95%CI was 1.049-1.456, P=0.012) were independent risk factors for CIRCI. A nomogram prediction model was constructed based on the above 5 indicators. The ROC curve demonstrated that the model achieved an area under the curve (AUC) of 0.965 (95%CI was 0.942-0.989) for predicting the occurrence of CIRCI. The optimal cut-off value was 0.201, yielding a sensitivity of 92.0% and a specificity of 87.3%, indicating excellent discriminative performance. The calibration curve revealed a C-index of 0.966 and a Dxy statistic of 0.933 in the training cohort, reflecting very high predictive accuracy and strong discriminative ability. The standard error of the C-index was 0.028, supporting the reliability of this estimate. Furthermore, the calibration curve showed excellent agreement with the ideal reference line. DCA curve indicated that the model provided positive net benefit across a predefined threshold probability range of 0.05-0.50 (with the 95%CI based on 1 000 Bootstrap resamples not crossing zero). Notably, at threshold probabilities exceeding the event rate (approximately 0.25), the model outperformed both the treat-all and treat-none strategies.
Conclusions:
History of type 2 diabetes mellitus, elevated PCT, elevated K+, elevated APACHE II score and elevated SOFA score may be independent risk factors for CIRCI in septic patients. The constructed nomogram prediction model has high accuracy and effectiveness, which can be used for early identification and intervention of CIRCI, and is conducive to improving the prognosis of sepsis patients.

Related Concept Videos
 01:23
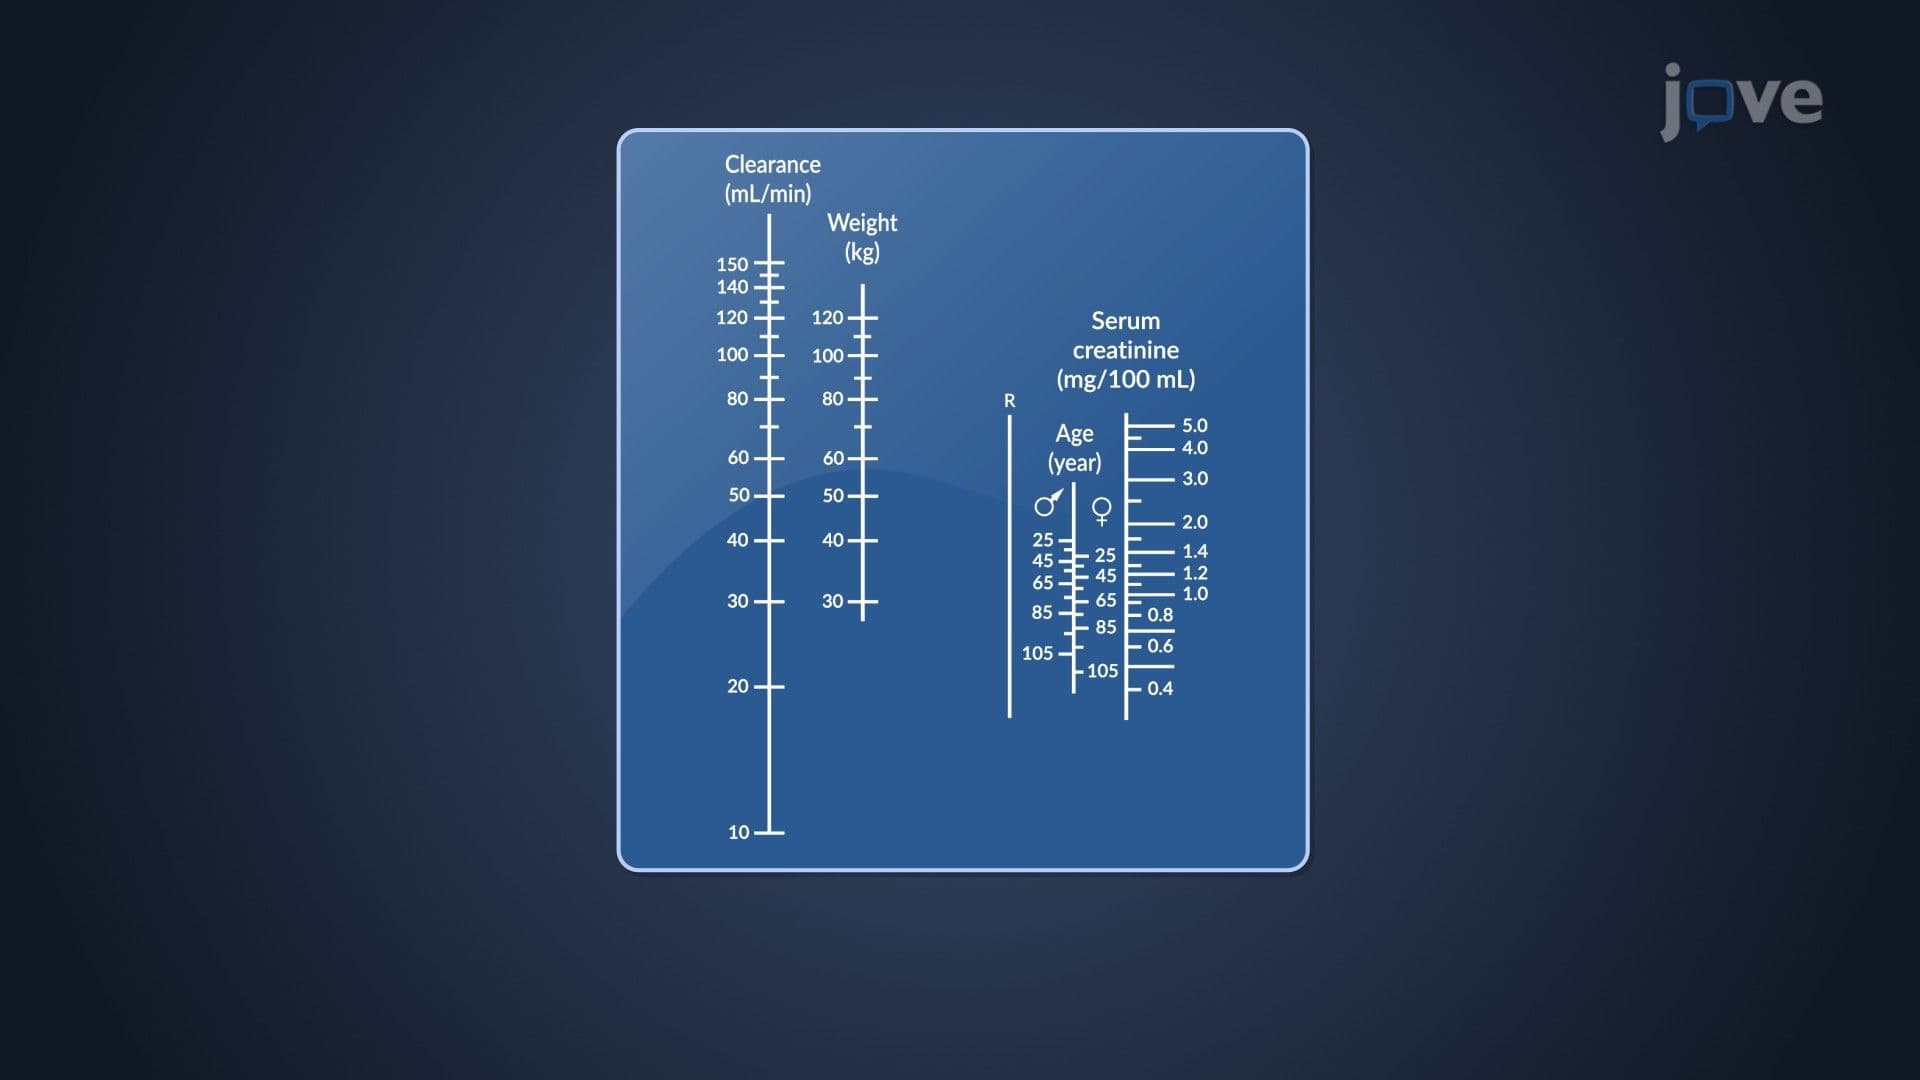
Dosage Regimen Designs: Nomograms and Tabulations
 01:24
Nephrotic Syndrome III : Nursing Management
 01:29
Pulmonary Tuberculosis I
Causative Organism
The primary infectious agent causing tuberculosis is Mycobacterium tuberculosis, a slow-growing, acid-fast, aerobic rod that exhibits sensitivity to heat and ultraviolet light. Instances of Mycobacterium bovis and Mycobacterium avium contributing to the development of TB infection are rare.
Mode of...
 01:30
Pneumonia III: Complications and Assessment