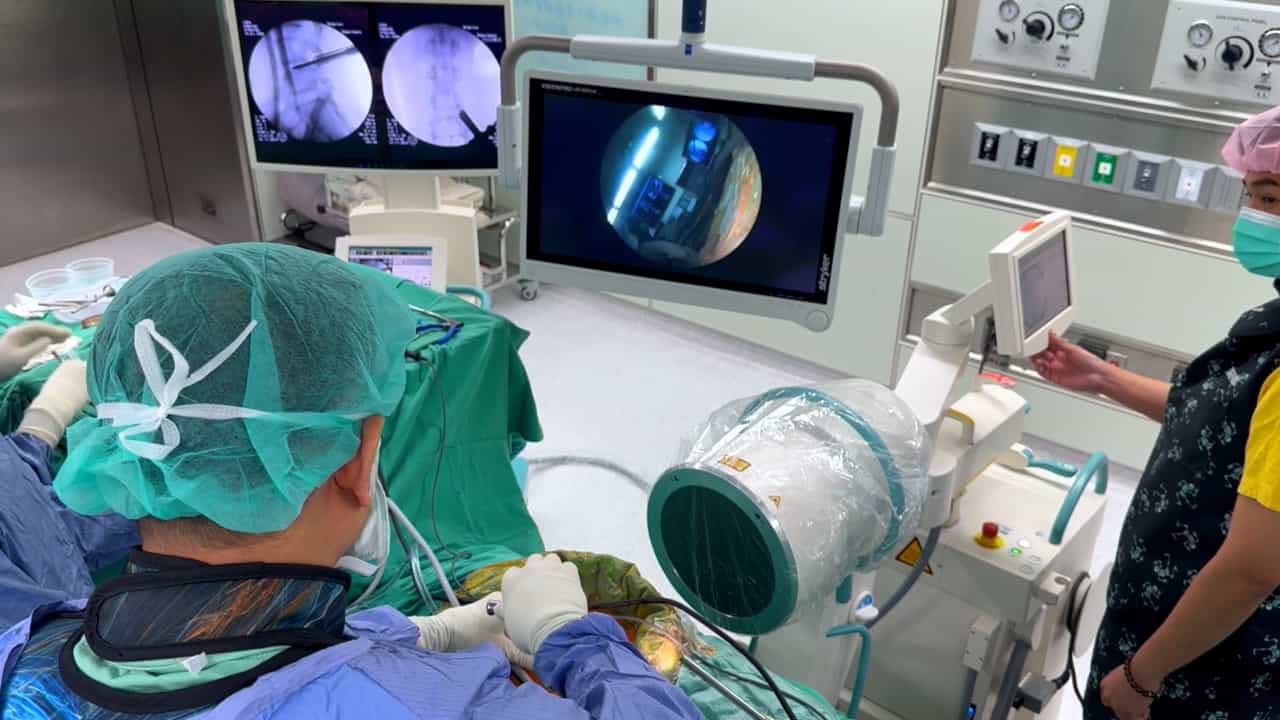
Related Experiment Video
Updated: Apr 13, 2026


Minimally Invasive Treatment for Thoracolumbar Burst Fracture Using Sagittal Alignment Screws and A Trauma Reduction Device
Published on: November 8, 2024
Thoracolumbar burst fractures: robot-assisted mono-segment fixation with vertebral body grafting versus short-segment
Junjie Qiao1, Yuyu Fan1, Ruizhao Zhao1
1Department of spine surgery, Beijing Shijitan Hospital, Capital Medical University, Beijing, China.

Purpose:
To compare robot-assisted mono-segment pedicle fixation with vertebral body grafting (RMF-VBG) versus conventional short-segment fixation with grafting (SF-VBG) for neurologically intact thoracolumbar burst fractures, focusing on radiographic maintenance of correction and perioperative efficiency.
Methods:
We performed a single-center retrospective cohort study (2018-2022) including adults with single-level AO-A3 fractures (T11-L2), ASIA E, treated within 14 days. One-to-one propensity score matching balanced baseline factors. The primary endpoint was loss of sagittal Cobb angle (SCA) at 12 months. Secondary outcomes included operative time, blood loss, postoperative length of stay (postop LOS), pain (VAS), Oswestry Disability Index (ODI), anterior vertebral body height ratio (AVBHr), pedicle screw accuracy (Gertzbein-Robbins), facet joint violation (FJV), perioperative morbidity and adjacent segment degeneration (ASD).
Results:
A total of 152 patients were matched (76 per group). RMF-VBG achieved significantly shorter operative time (62.38 ± 14.26 vs 89.56 ± 20.36 min), reduced blood loss (82.54 ± 19.69 vs 126.38 ± 28.26 mL), and shorter postop LOS (5.23 ± 1.72 vs 7.16 ± 1.39 days; all p<0.001). SCA and AVBHr trajectories were comparable; SCA loss at 12 months did not differ (mean difference -0.07°, 95% CI -0.30 to 0.16; p = 0.551). The 95% CI for the between-group difference in 12-month SCA loss remained within the ±2.0° MCID, indicating no clinically important difference. Screw placement accuracy (Grade A) was higher with RMF-VBG (98.35% vs 90.13%), and FJV Grade 2 was less frequent (0% vs 3.95%). Overall morbidity and ASD were uncommon and similar between groups.
Conclusion:
For selected thoracolumbar burst fractures, RMF-VBG maintained sagittal correction within the prespecified MCID compared with SF-VBG, while improving perioperative efficiency and screw-related precision.